Category: Gut Health

  • Can Chest Pain Be Digestive? What to Rule Out First

    Can Chest Pain Be Digestive? What to Rule Out First

    New, severe, unexplained, or pressure-like chest pain needs urgent medical evaluation before assuming digestion is the cause. Digestive issues such as acid reflux can create burning chest discomfort, but heart, lung, muscle, anxiety, and esophageal causes can overlap. Emergency symptoms include shortness of breath, sweating, nausea, faintness, or pain spreading to the jaw, back, shoulder, or arm.

    How did we evaluate chest pain and digestive causes?

    We evaluated chest pain by separating emergency triage from digestive pattern recognition. We prioritized medical sources that explain heart attack warning signs, acid reflux symptoms, noncardiac chest pain, and GERD evaluation, including Mayo Clinic, the American Heart Association, NIDDK, and the American College of Gastroenterology. We treated new, severe, exertional, spreading, or unexplained chest pressure as a medical red flag because online symptom-matching cannot rule out cardiac or lung causes. We excluded unsupported home-diagnosis shortcuts, including the idea that burning always means reflux or that antacids prove a digestive cause. We also separated symptom patterns from causes, because the same sensation can come from different organs with different risks and timelines. This article explains what patterns can suggest digestion after urgent causes are considered; it does not diagnose chest pain or replace emergency care.

    When is chest pain an emergency?

    Chest pain is an emergency when it is new, severe, unexplained, pressure-like, lasts more than a few moments, occurs with exertion, or comes with symptoms outside the chest. Mayo Clinic advises calling emergency services for severe chest pain or new unexplained chest pain or pressure that lasts more than a few moments. The American Heart Association lists chest discomfort, shortness of breath, jaw pain, neck pain, back pain, arm pain, nausea, and lightheadedness among heart attack warning signs. Digestive pain can feel similar because the esophagus, stomach, chest wall, lungs, and heart share nearby nerve pathways. If a symptom feels different from your usual reflux, appears during activity, wakes you suddenly, or spreads beyond the breastbone, treat it as urgent until a clinician says otherwise. Delay is the wrong gamble when chest symptoms are unfamiliar.

    Can acid reflux cause chest pain?

    Acid reflux can cause chest pain, especially burning discomfort behind the breastbone after meals, when lying down, or when bending over. The NIDDK explains that gastroesophageal reflux and GERD commonly cause heartburn and regurgitation when stomach contents move back into the esophagus. Mayo Clinic also describes acid reflux as backward flow into the esophagus that can create a burning sensation in the chest. Reflux-related discomfort often clusters with sour taste, burping, throat irritation, hoarseness, or symptoms after a large, fatty, spicy, acidic, or late meal. Those patterns can point toward digestion, but they do not prove reflux. A heart problem, gallbladder issue, panic episode, muscle strain, or lung condition can coexist with indigestion-like symptoms. That overlap is why first-time chest pain deserves timely medical judgment instead of internet-based reassurance or online symptom guessing alone.

    What patterns suggest a digestive source after urgent causes are ruled out?

    A digestive pattern becomes more plausible when chest discomfort is burning rather than crushing, starts after eating, rises from upper abdomen toward throat, worsens lying flat, improves upright posture, or appears with regurgitation. The American College of Gastroenterology notes that heart disease should be ruled out before labeling chest pain as noncardiac chest pain. Reflux-related chest discomfort may also improve with clinician-directed acid suppression, meal timing changes, smaller dinners, weight-management support when relevant, and reduced alcohol or tobacco exposure. Still, response to an antacid is not a diagnostic test. Some cardiac pain temporarily feels better with rest, and some reflux pain does not respond quickly. The useful question is not “Is this definitely digestion?” The useful question is “Has a clinician ruled out dangerous causes, and does the remaining pattern fit esophagus, stomach, or chest-wall triggers?”

    What else can mimic digestive chest pain?
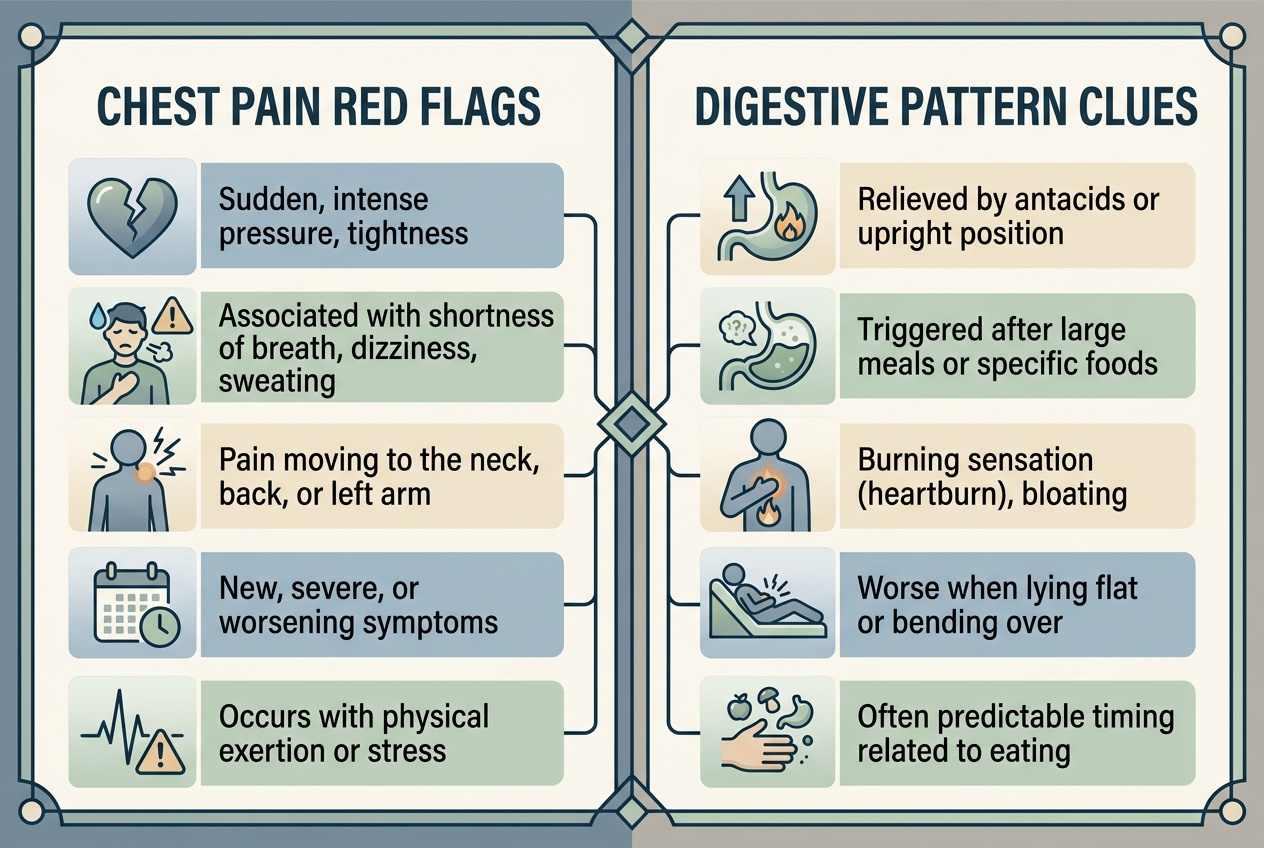
    Chest pain checklist comparing urgent red flags with digestive symptom patterns
    Chest pain checklist comparing urgent red flags with digestive symptom patterns

    Several non-digestive conditions can mimic reflux or indigestion. Heart-related pain can feel like pressure, squeezing, fullness, burning, or upper abdominal discomfort, according to Mayo Clinic’s chest pain overview. Lung causes can create sharp pain with breathing, coughing, shortness of breath, or sudden onset. Chest-wall strain and costochondritis can cause localized tenderness that changes with movement or pressure. Panic attacks can create chest tightness, fast heartbeat, sweating, nausea, and shortness of breath, which can resemble both reflux and heart symptoms. Esophageal spasm can cause intense squeezing pain and swallowing discomfort. Gallbladder pain can sit in the upper abdomen and travel toward the chest or shoulder after fatty meals. Because these patterns overlap, duration, triggers, associated symptoms, medical history, vital signs, exam findings, risk factors, and testing context matter more than a single symptom word alone.

    What should you track before talking with a clinician?

    Track timing, trigger, location, duration, severity, spread, and associated symptoms. Note whether the pain starts during exercise, stress, sleep, bending, swallowing, coughing, or after specific meals. Write down whether it feels burning, squeezing, stabbing, pressure-like, tight, or tender to touch. Record related symptoms such as shortness of breath, nausea, sweating, dizziness, palpitations, regurgitation, sour taste, trouble swallowing, black stools, vomiting, fever, or unexplained weight loss. Bring medication details, including NSAIDs, aspirin, iron, potassium, bisphosphonates, antibiotics, and acid reducers, because several medicines can irritate the esophagus or stomach. Also list cardiac risk factors such as diabetes, smoking, high blood pressure, high cholesterol, pregnancy or postpartum status, prior clots, and family history. A concise symptom log helps a clinician decide whether testing should focus on heart, lung, esophagus, stomach, gallbladder, muscle, or anxiety-related pathways first safely.

    What questions do people ask about chest pain and digestion?

    Can GERD feel like a heart attack?

    Yes, GERD can create chest burning. Heart attack symptoms can include indigestion-like discomfort, so new or severe chest pain needs evaluation first.

    Is chest pain after eating always reflux?

    No. Meals can trigger reflux, gallbladder pain, or esophageal spasm. A repeated after-meal pattern is useful evidence, not proof.

    Can burping come with heart-related chest pain?

    Yes, burping can happen during digestive discomfort and anxiety around chest symptoms. Burping does not safely rule out heart-related pain.

    Should I try antacids before seeking help?

    Do not use antacids to delay urgent care for new, spreading, or pressure-like pain. For familiar mild heartburn, ask a pharmacist.

    Why does reflux hurt in the chest?

    Reflux irritates the esophageal lining behind the breastbone. The brain may perceive esophageal irritation as chest burning, pressure, or upper abdominal discomfort.

    What is the safest next step?

    For new or concerning chest pain, seek urgent advice. For recurring symptoms after danger is ruled out, track triggers with a clinician.

    What is the practical takeaway?

    Chest pain should be treated as a safety question first and a digestion question second. Acid reflux can cause burning chest discomfort, especially after meals or when lying down, but similar sensations can come from the heart, lungs, chest wall, gallbladder, esophagus, or panic physiology. The practical order is clear: get urgent care for red flags, rule out dangerous causes, then track digestive patterns with a clinician. If the remaining pattern fits reflux, the most useful next steps are meal timing, trigger tracking, medication review, and evidence-based GERD evaluation rather than guessing from one symptom. A careful log also helps prevent two common mistakes: dismissing serious symptoms as reflux, or treating every familiar sensation as an emergency after a clinician has already ruled out dangerous causes and explained the likely pattern clearly enough safely.

  • Endoscopy Results: What the Report Means and What to Ask Next

    Endoscopy Results: What the Report Means and What to Ask Next

    Endoscopy results usually describe what the camera saw, what tissue samples were taken, and whether follow-up testing is needed. Common findings include a normal exam, irritation, reflux-related changes, gastritis, ulcers, hiatal hernia, polyps, or biopsy results still pending. Ask the clinician what was seen, biopsied, and recommended next.

    How did we evaluate endoscopy results?

    We evaluated endoscopy results by separating the procedure note, visual findings, pathology report, medication plan, and follow-up instructions. Gastroenterology society guidance, government patient resources, and hospital-based explanations received more weight than forum anecdotes because endoscopy words can sound alarming without context. We prioritized terms people commonly see after upper endoscopy, including normal mucosa, esophagitis, gastritis, hiatal hernia, Barrett’s esophagus, ulcer, polyp, biopsy, and H. pylori. We excluded product recommendations because a cold-stage results article should help readers understand the report and prepare questions, not push a supplement or brand. The limitation is important: an online article cannot interpret an individual pathology result, photo, or medication history. The safest reading combines the written report, pathology addendum, symptom pattern, age, risk factors, medication exposure, and the clinician’s actual follow-up plan. Unclear phrases deserve clinician translation before a reader changes habits.

    What does an endoscopy report usually include?

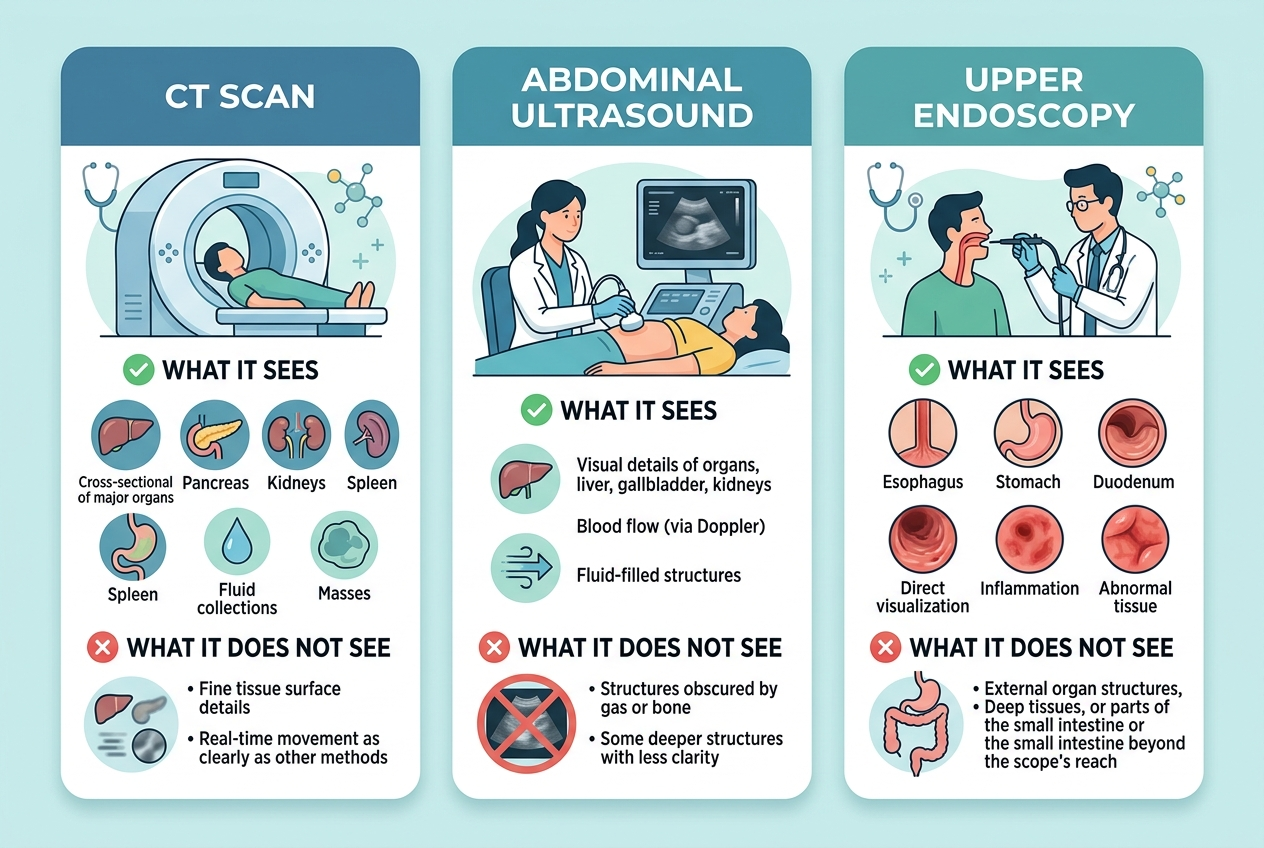
    An upper endoscopy report usually includes the indication, sedation details, areas examined, visual findings, biopsy locations, immediate impression, and follow-up plan. The NIDDK upper GI endoscopy guide explains that the test lets a doctor view the esophagus, stomach, and duodenum and may include biopsy or treatment during the same procedure. The indication tells why the test happened, such as trouble swallowing, reflux symptoms, anemia, bleeding signs, nausea, abdominal pain, or follow-up of a prior finding. The findings section describes what the endoscopist saw with the camera. The pathology report describes what a lab saw under a microscope if tissue samples were taken. Those two parts can differ. A camera can show redness, but pathology can identify inflammation type, infection clues, metaplasia, or normal tissue. People should wait for both parts before treating the first result message as the full answer.

    What does a normal endoscopy result mean?

    A normal upper endoscopy means the endoscopist did not see obvious structural damage in the inspected esophagus, stomach, or duodenum. It does not mean symptoms are imaginary, and it does not rule out every digestive explanation. Functional dyspepsia, reflux without visible erosions, motility problems, food intolerance patterns, medication irritation, constipation pressure, gallbladder disease, and gut-brain interaction can still create real symptoms after a normal exam. The American College of Gastroenterology patient page on functional dyspepsia describes persistent upper-abdominal symptoms that can occur without an ulcer or visible explanation on endoscopy. A normal result can still be useful because it reduces concern for some structural problems and guides next-step testing. The key question is what the clinician thinks fits the whole case now. Ask whether biopsy results are pending, whether H. pylori was checked, and what symptom pattern should trigger follow-up.

    What do gastritis, esophagitis, and irritation mean?

    Gastritis means the stomach lining shows inflammation or irritation, while esophagitis means the esophagus shows inflammation or injury. These terms describe tissue appearance; they do not automatically explain the cause. Possible contributors include reflux exposure, H. pylori infection, NSAID use, bile irritation, alcohol exposure, autoimmune patterns, or other medical contexts. The Mayo Clinic gastritis overview notes that gastritis can be sudden or gradual and can have different causes. Endoscopy language such as “mild,” “erosive,” “non-erosive,” “erythema,” or “friability” helps classify appearance, but biopsy and history often decide the meaning. Ask whether the finding was mild, moderate, or severe; whether ulcers were present; whether biopsies were taken; and whether medications, infection testing, or follow-up endoscopy were recommended. A short report phrase should not be read as the whole diagnosis.

    What does a biopsy after endoscopy mean?

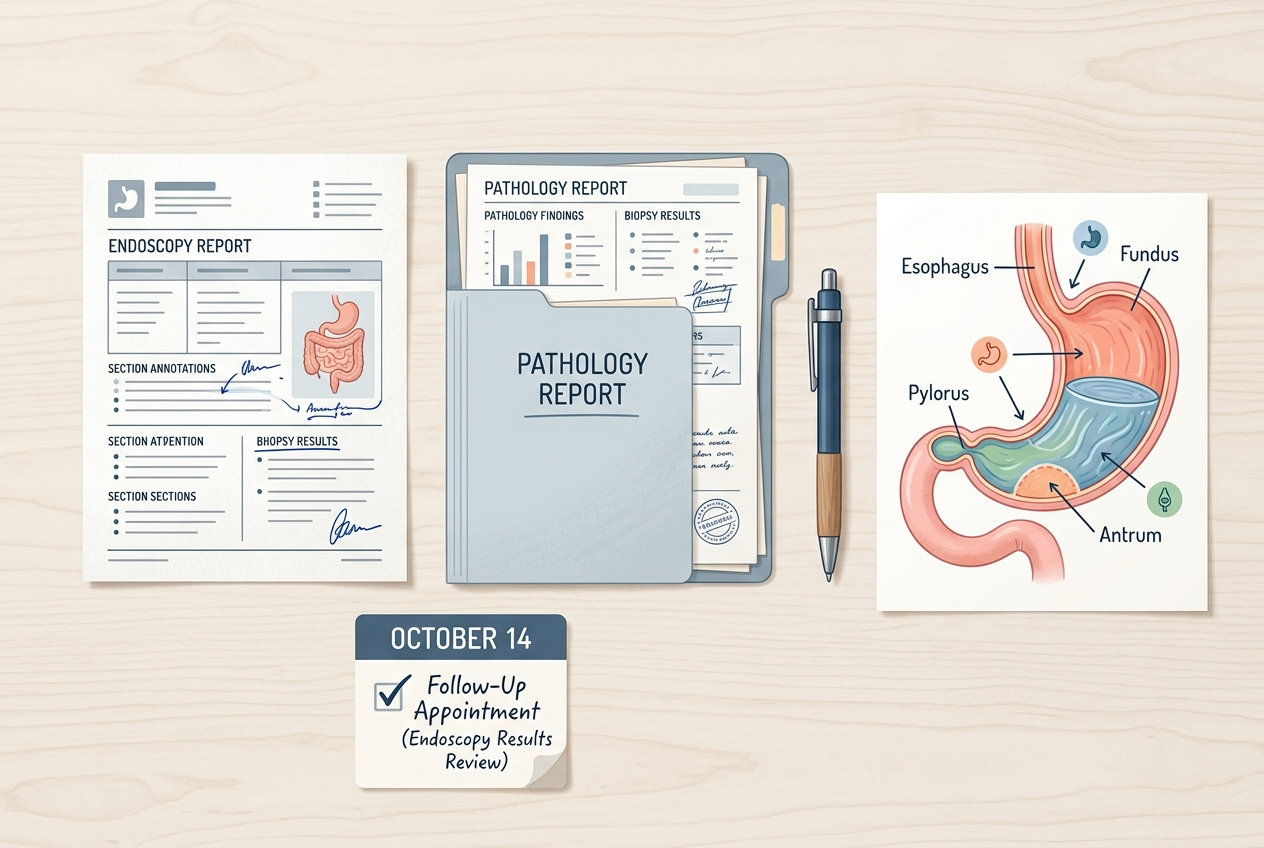
    Endoscopy report and pathology folder arranged with a calendar and notes for follow-up.
    Endoscopy report and pathology folder arranged with a calendar and notes for follow-up.

    A biopsy after endoscopy means the clinician removed tiny tissue samples for lab review. Biopsy does not automatically mean cancer, and it is common during upper endoscopy when clinicians need to check inflammation, H. pylori, celiac-related changes, Barrett’s esophagus, eosinophilic esophagitis, ulcers, polyps, or tissue that looked different from expected. The pathology report may arrive days after the procedure note, so the first portal message can be incomplete. A useful question is, “Were biopsies routine, targeted, or both?” Routine biopsies sample normal-looking tissue for microscopic clues. Targeted biopsies sample a visible area such as an ulcer edge, polyp, patch, ring, or abnormal lining. The final meaning depends on the microscopic diagnosis, margin comments if relevant, and clinician interpretation. People should save the pathology report, not only the endoscopy photo page, because future clinicians often need the exact wording later.

    What does a hiatal hernia on endoscopy mean?

    A hiatal hernia means part of the stomach sits higher through the diaphragm opening than usual. Small sliding hiatal hernias are common findings, and their importance depends on size, reflux pattern, symptoms, esophagitis, swallowing issues, anemia clues, and the clinician’s exam. Cleveland Clinic explains that hiatal hernia can be associated with reflux symptoms, but the finding can also be mild or incidental in some people (Cleveland Clinic). The report may describe the hernia in centimeters or by landmarks such as the gastroesophageal junction and diaphragmatic pinch. Ask whether the hernia was small, sliding, paraesophageal, or clinically significant. Also ask whether it changes the reflux plan, eating pattern advice, medication timing, or need for additional testing. The word “hernia” sounds dramatic, but the management question depends on anatomy plus symptoms, not the word alone.

    What questions should you ask after getting results?

    The best follow-up questions turn report language into next steps. Ask: “What was seen visually, what was biopsied, and what is still pending?” Then ask whether the finding explains the symptoms, whether H. pylori or celiac testing was done, whether medication timing should change, and what warning symptoms should trigger urgent care. If the report mentions esophagitis, ask for the grade. If it mentions Barrett’s esophagus, ask whether intestinal metaplasia was confirmed by pathology and what surveillance interval applies. If it mentions ulcers, ask about NSAIDs, H. pylori, bleeding risk, and follow-up. If it says normal, ask what non-structural explanations remain. Bring a medication list, supplement list, symptom timeline, stool changes, weight changes, and family history to the visit. The goal is not to memorize medical vocabulary; the goal is to know the next decision.

    What questions do people ask about endoscopy results?

    Can an endoscopy be normal even if symptoms are severe?

    Yes. Severe symptoms can occur with a normal-looking endoscopy when the cause is functional dyspepsia, reflux without erosions, visceral sensitivity, motility issues, constipation pressure, or a non-upper-GI source. A normal result should lead to a next-step plan, not dismissal.

    Does a biopsy mean the doctor found something bad?

    No. Biopsies are common and often routine during endoscopy. The lab may check for inflammation, H. pylori, celiac-type changes, eosinophils, Barrett’s-related changes, or other microscopic findings that the camera cannot confirm alone.

    How long do pathology results take?

    Timing varies by lab and health system, but pathology commonly takes several business days. Ask the endoscopy office when to expect the final report and whether the clinician will call or post results in the patient portal.

    What does mild gastritis mean?

    Mild gastritis means the stomach lining looked mildly inflamed or irritated, but the cause and importance depend on biopsy, medications, alcohol exposure, H. pylori testing, and symptoms. Ask whether the finding changes treatment or simply explains part of the pattern.

    Can endoscopy diagnose reflux?

    Endoscopy can identify reflux complications such as erosive esophagitis, strictures, or Barrett’s changes, but reflux can exist without visible erosions. Some people need symptom review, medication response, pH testing, or other evaluation depending on the case.

    What should I do if I do not understand the report?

    Write down the exact phrases that confuse you and ask the clinician to translate each one into significance, cause, and next step. Portal summaries can be brief; a follow-up conversation often explains what the wording means for your situation.

    What is the bottom line?

    Endoscopy results are most useful when read in layers: visual findings first, pathology second, clinician interpretation third, and follow-up plan last. A normal report can still leave real symptoms to solve. An abnormal phrase can be mild, routine, urgent, or simply incomplete until pathology returns. The practical next step is to ask what was seen, what was sampled, what is pending, and what should happen next. Save both the endoscopy note and the pathology report because future clinicians may need exact wording. If symptoms worsen, swallowing becomes difficult, bleeding signs appear, or weight loss is unexplained, contact the care team instead of waiting for the next routine appointment. The report is a map for follow-up, not a final self-diagnosis. Good interpretation turns medical vocabulary into actions: monitor, test, adjust, return, or escalate appropriately afterward.

  • Wicked Upper Indigestion: What It Can Mean and When to Get Checked

    Wicked Upper Indigestion: What It Can Mean and When to Get Checked

    Wicked upper indigestion usually means discomfort, pressure, burning, nausea, or early fullness in the upper abdomen. Common explanations include functional dyspepsia, reflux, gastritis, medication irritation, eating pattern changes, or less common urgent problems. Severe chest pain, black stools, vomiting blood, trouble swallowing, unexplained weight loss, or persistent vomiting needs medical care.

    How did we evaluate upper indigestion causes?

    We evaluated upper indigestion by separating symptom patterns from diagnoses, because the same upper-abdominal discomfort can come from the esophagus, stomach, duodenum, gallbladder, pancreas, heart, or medication exposure. Government and gastroenterology sources received more weight than forum anecdotes, supplement claims, or single-person trigger lists. We prioritized red-flag triage, symptom timing, H. pylori relevance, medication review, meal-pattern clues, and the distinction between reflux-dominant symptoms and dyspepsia-dominant symptoms. We excluded product recommendations because a cold-stage indigestion article should help readers decide what kind of problem they may be tracking, not push them toward a supplement. The main limitation is that symptom location is imprecise; upper abdominal pain, chest pressure, nausea, and burning can overlap across harmless, chronic, and urgent conditions. We also treated sudden intensity changes as more important than familiar mild symptoms over time clinically.

    What does upper indigestion feel like?

    Upper indigestion, also called dyspepsia, usually sits between the lower breastbone and the belly button. The NIDDK indigestion guide describes symptoms such as upper-abdominal pain, burning, fullness during a meal, uncomfortable fullness after a meal, bloating, nausea, burping, and sometimes heartburn. Mayo Clinic uses a similar symptom cluster and notes that upper-abdominal pain can range from mild to severe. The word “wicked” matters because intensity changes the decision tree. Mild fullness after a heavy meal often behaves differently from sharp pain, repeated vomiting, black stool, chest pressure, faintness, or pain that wakes someone from sleep. A useful first step is to write down the exact sensation, location, meal timing, medication timing, stool changes, and whether exertion, lying down, alcohol, NSAIDs, caffeine, carbonation, or stress changes the pattern. Location alone should not decide urgency or reassurance either.

    Which causes are common but not always obvious?

    Functional dyspepsia is one common explanation when upper-abdominal symptoms persist and testing does not show a clear structural cause. The NIDDK lists functional dyspepsia, medicines, infections, and digestive tract conditions as possible contributors to indigestion symptoms. H. pylori infection can contribute to ulcer-related symptoms in some people, but a positive or negative test changes next steps more reliably than guessing from symptoms alone. NSAIDs such as ibuprofen and naproxen can irritate the stomach lining, especially with frequent use, alcohol, or prior ulcer history. Reflux can feel like burning, chest discomfort, sour regurgitation, cough, or throat symptoms, while gallbladder pain may feel more right-sided or meal-triggered. Constipation, swallowed air, high-fat meals, large meals, rapid eating, tight waist pressure, delayed gastric emptying, and anxiety-related gut-brain signaling can also amplify upper pressure without being the root cause. Several causes can coexist.

    When should upper indigestion be checked urgently?

    Upper indigestion tracking tools including meal timing, medication timing, and symptom notes.
    Upper indigestion tracking tools including meal timing, medication timing, and symptom notes.

    Upper indigestion should be checked urgently when symptoms could represent bleeding, obstruction, infection, heart-related pain, or another serious condition. The NIDDK GERD symptom guide tells readers to seek medical care for chest pain, loss of appetite, persistent vomiting, painful swallowing, trouble swallowing, signs of digestive bleeding, or unexplained weight loss. Mayo Clinic similarly flags chest, neck, or shoulder pain with abdominal pain as a reason for emergency evaluation. Red flags do not mean the worst outcome is likely; they mean symptom-only sorting is unsafe. People should be especially cautious when upper discomfort is new after age 60, follows an injury, appears with shortness of breath, causes fainting, includes fever, radiates to the back or shoulder, or feels different from prior reflux or indigestion. Persistent symptoms also deserve routine care even without emergency signs. New symptoms during pregnancy also deserve clinician guidance.

    What should someone track before an appointment?

    A short symptom log can make an appointment more useful than a vague memory of “bad indigestion.” Track meal time, meal size, fat content, alcohol, caffeine, carbonated drinks, spicy foods, acidic foods, NSAIDs, iron pills, antibiotics, magnesium, cannabis, nicotine, stress, sleep, bowel movements, and menstrual-cycle timing if relevant. Record whether symptoms appear during meals, within 30 minutes, several hours later, when lying down, after exertion, or overnight. Note whether antacids, H2 blockers, proton pump inhibitors, smaller meals, walking, bowel movements, or avoiding NSAIDs changes the pattern. Bring a medication and supplement list with doses, because upper indigestion can follow dose changes or interactions. The goal is not to name the condition yourself; the goal is to give a clinician enough pattern data to choose between watchful waiting, H. pylori testing, blood work, imaging, endoscopy, reflux care, or another pathway.

    How do clinicians usually sort dyspepsia?

    Clinicians usually start with age, alarm features, medical history, medication use, physical exam, and symptom duration. The ACG and CAG dyspepsia guideline recommends H. pylori testing for many younger adults without alarm features, then acid suppression or other options depending on the result and persistence of symptoms. Older adults or people with red flags may need earlier endoscopy or targeted testing. Functional dyspepsia becomes more likely when recurring symptoms remain after structural causes are not found, but that label should come after appropriate evaluation, not before. A careful workup also separates dyspepsia from reflux-dominant symptoms, gallbladder patterns, pancreatic warning signs, medication injury, constipation-related pressure, pregnancy-related changes, or cardiac symptoms that can masquerade as upper-abdominal discomfort. The safest approach is pattern recognition plus medical triage, not internet certainty. Follow-up matters when symptoms continue despite first-step care or recur repeatedly.

    What questions do people ask about upper indigestion?

    Can indigestion feel high in the stomach?

    Yes. Indigestion commonly affects the upper abdomen between the breastbone and belly button. Some people describe pressure, burning, fullness, nausea, or a stuck sensation rather than sharp pain.

    Can reflux and indigestion happen together?

    Yes. NIDDK notes that heartburn can occur with indigestion even though reflux and dyspepsia are different concepts. Burning behind the breastbone, sour regurgitation, cough, or symptoms worse when lying down may point more toward reflux.

    Can stress make upper indigestion worse?

    Stress can amplify gut-brain signaling and symptom awareness, but stress should not be used to dismiss severe, new, or progressive symptoms. A symptom log can show whether stress timing overlaps with meals, sleep loss, caffeine, or bowel changes.

    Should someone test for H. pylori?

    H. pylori testing is a clinician-guided decision, especially when symptoms persist or ulcer risk is possible. The ACG/CAG guideline supports H. pylori testing in selected dyspepsia pathways, but the right test depends on medications, age, and risk factors.

    Can NSAIDs cause upper indigestion?

    NSAIDs such as ibuprofen and naproxen can irritate the stomach lining and may contribute to burning, pain, or ulcer risk. People with frequent NSAID use should tell a clinician, especially if symptoms include black stools, anemia, vomiting, or severe pain.

    What is the bottom line?

    Upper indigestion is a symptom pattern, not a diagnosis. Mild meal-related discomfort may improve with tracking and basic habit changes, but severe, persistent, new, or red-flag symptoms deserve medical evaluation instead of guesswork.

  • Does Your Gut Control More Than Digestion? What the Evidence Actually Says

    Does Your Gut Control More Than Digestion? What the Evidence Actually Says

    Your gut does not literally control everything, but it influences more than digestion. The gastrointestinal tract communicates with the brain, immune system, metabolism, hormones, and daily energy through nerves, microbes, immune signals, and fermentation byproducts. Strong claims need caution: gut signals shape body patterns, but they do not replace medical evaluation.

    How did we evaluate what the gut can influence?

    We evaluated gut influence by separating established physiology from overstated wellness claims. Human studies, NIH digestive-health resources, PubMed-indexed reviews, and gastroenterology guidance carried more weight than social posts about the microbiome controlling personality, weight, mood, or cravings. We prioritized mechanisms with named pathways: the vagus nerve, enteric nervous system, short-chain fatty acids, immune cytokines, intestinal barrier function, bile acids, and gut hormones such as GLP-1 and peptide YY. We excluded claims that framed the gut as a single master switch, because digestion, sleep, stress, medication use, genetics, and diet all interact. We also treated symptom stories as useful real-world hypothesis generators, not clinical proof. The practical question is not whether the gut controls the body. The practical question is which signals can be observed, supported, and discussed with a clinician when patterns change.

    How does the gut communicate with the brain?

    The gut communicates with the brain through the gut-brain axis, a two-way network involving the vagus nerve, spinal nerves, immune molecules, microbial metabolites, and stress hormones. The enteric nervous system contains millions of neurons that regulate motility, secretion, and sensation inside the gastrointestinal tract. A PubMed-indexed review on the microbiota-gut-brain axis describes this network as bidirectional, meaning brain stress can change gut function and gut signals can change brain signaling. That does not mean bloating, reflux, diarrhea, or constipation are “all in your head.” It means the nervous system and digestive tract share information constantly. Stress can slow or speed motility, pain sensitivity can rise, and gut discomfort can increase vigilance. The most useful takeaway is modest: gut sensations can reflect nerve signaling, meal timing, microbial fermentation, inflammation, or stress physiology at the same time.

    How can gut microbes affect daily body signals?

    Gut microbes affect body signals by fermenting carbohydrates, transforming bile acids, interacting with immune cells, and producing metabolites such as acetate, propionate, and butyrate. These short-chain fatty acids help colon cells use energy and interact with immune and metabolic pathways. A review in Gut Microbes describes short-chain fatty acids as signaling molecules, not just fermentation waste. The effect depends on diet, fiber type, transit time, microbial composition, and baseline health. More gas after beans, oats, onions, or inulin does not automatically mean the food is “bad”; it may mean colonic bacteria are fermenting carbohydrates faster than the gut can comfortably handle. The same mechanism can feel supportive at one dose and uncomfortable at another. Gut microbes therefore influence daily signals, but the response is dose-specific, person-specific, meal-specific, and timing-specific, and tolerance-specific rather than magical.

    What does the gut have to do with immunity?

    The gut has a major immune role because the intestinal lining separates food, microbes, bile, stomach acid residues, and digestive enzymes from the bloodstream. Gut-associated lymphoid tissue helps immune cells sample intestinal contents and respond to pathogens while tolerating normal food and resident microbes. The NIDDK explains that the digestive tract contains immune cells that help protect the body from harmful organisms. The intestinal barrier also uses mucus, tight junction proteins, secretory IgA, antimicrobial peptides, and microbial competition to manage exposure. This does not mean every immune symptom begins in the gut, and it does not mean a supplement can “fix immunity.” It means digestion and immune signaling are structurally connected. Diet quality, fiber tolerance, sleep, medication use, infection history, and stress can all influence how that system feels day to day and week to week.

    Can the gut influence appetite, energy, and cravings?

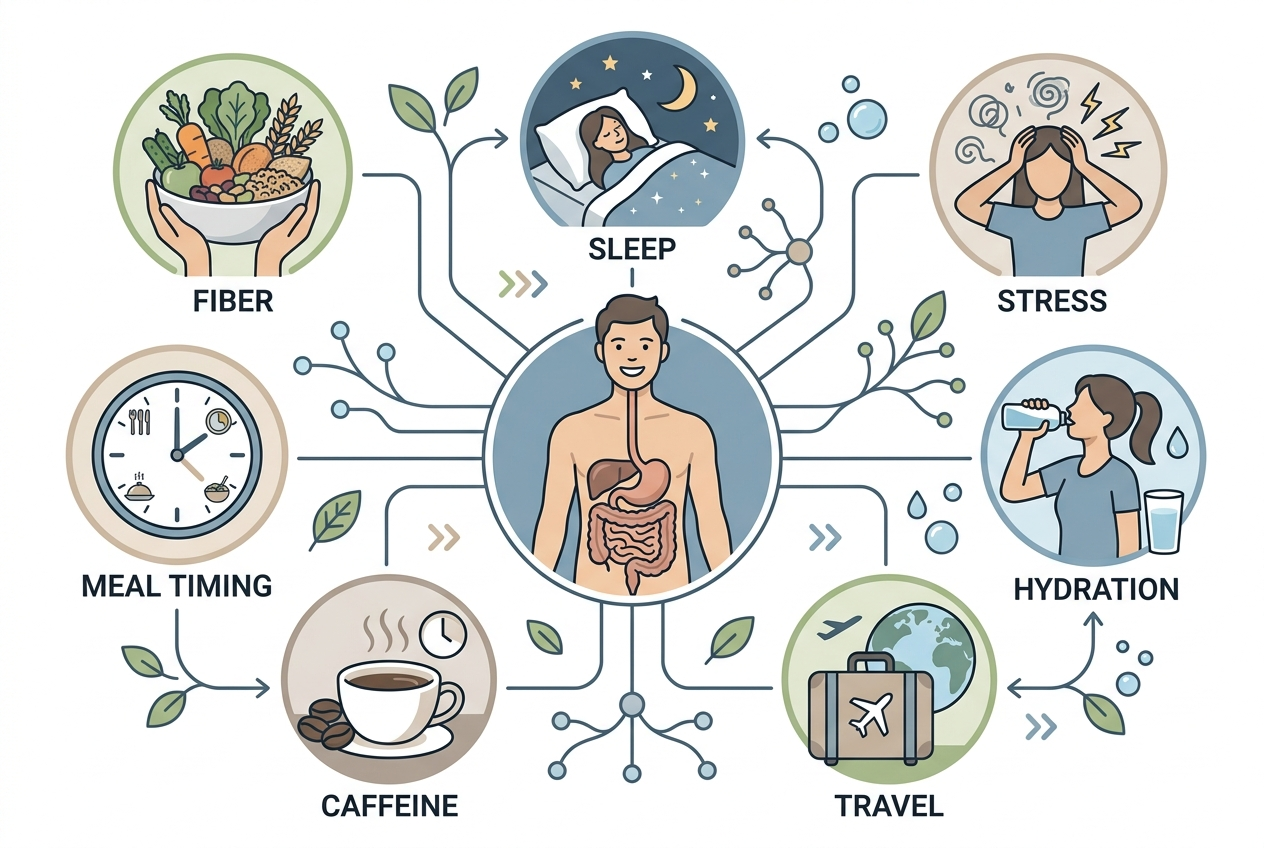
    Gut-support habits including fiber foods, water, movement, sleep, and symptom tracking.
    Gut-support habits including fiber foods, water, movement, sleep, and symptom tracking.

    The gut can influence appetite, energy, and cravings through stretch receptors, blood glucose patterns, bile acid signaling, gut hormones, and microbial fermentation products. After a meal, the stomach and small intestine send fullness information through neural and hormonal routes. GLP-1, cholecystokinin, peptide YY, ghrelin, insulin, and bile acids all participate in hunger and satiety signaling. A review in Nutrients describes gut hormones as central regulators of appetite and metabolism, although individual responses vary widely. This is why meal composition matters: protein, fiber, fat, fluid, and eating speed can change fullness more predictably than a single “gut hack.” Cravings can also reflect sleep debt, restriction, stress, habit loops, or low energy intake. The gut participates in appetite regulation, but it does not independently dictate daily food choices like a hidden remote control in the background.

    What do people get wrong about gut control?

    People often turn gut science into an all-or-nothing story. One mistake is treating the microbiome as a personality controller, when most human microbiome evidence is associative, preliminary, or context-specific. Another mistake is assuming every symptom proves dysbiosis. The NIDDK notes that gas can come from swallowed air and carbohydrate digestion, which means ordinary physiology can look dramatic. A third mistake is making ten changes at once: probiotics, fasting, elimination diets, fiber powders, fermented foods, enzymes, and caffeine changes can blur the signal. A fourth mistake is ignoring red flags because “it is probably gut health.” New bleeding, unexplained weight loss, persistent vomiting, trouble swallowing, fever, severe pain, or major bowel-habit changes deserves medical care. Gut health is a useful lens, not a license to oversimplify the body, blame every symptom, or postpone needed care.

    How can you support gut signals without overreacting?

    Support gut signals by changing one boring variable at a time. A practical sequence starts with meal timing, hydration, sleep, fiber consistency, movement, caffeine, alcohol, and stress load before extreme elimination diets. If fiber intake is low, increase beans, oats, berries, vegetables, lentils, chia, or psyllium gradually while watching gas and stool changes. If bloating rises after a change, reduce the dose rather than declaring the whole category harmful. If reflux, diarrhea, constipation, or pain persists, track meals, timing, stool form, medications, menstrual cycle, travel, and stress for two weeks before guessing. That record gives a clinician or dietitian better evidence than memory. The gut often responds to small repeated inputs, but the body also needs escalation when patterns are severe, sudden, or progressive. Calm observation beats panic and internet overcorrection almost every time.

    What questions come up about gut influence?

    Does the gut control your mood?

    The gut can influence mood-related signaling through nerves, immune activity, microbial metabolites, and inflammation pathways. It does not single-handedly control mood, and mental health symptoms deserve appropriate care.

    Can gut health affect energy?

    Gut patterns can affect perceived energy through meal tolerance, blood glucose swings, sleep disruption, nutrient absorption, and inflammation. Fatigue also has many non-gut causes, including anemia, thyroid issues, infection, medication effects, and sleep disorders.

    Does bloating mean the microbiome is unhealthy?

    Bloating does not automatically mean the microbiome is unhealthy. Gas, swallowed air, constipation, rapid fiber increases, high-FODMAP foods, stress, and gut sensitivity can all contribute.

    Are cravings caused by gut bacteria?

    Gut bacteria may participate in appetite signaling, but cravings also reflect sleep, restriction, stress, habits, food availability, and energy needs. Treat microbiome-only craving claims as speculative unless the source explains evidence quality.

    Should you change your diet if your gut feels off?

    A small, trackable diet change is usually more useful than a dramatic reset. Increase or reduce one variable at a time, such as fiber dose, caffeine timing, meal size, or fermented-food frequency.

    When should gut symptoms get medical attention?

    Medical attention matters when symptoms are severe, persistent, new, or paired with bleeding, black stools, fever, vomiting, unexplained weight loss, difficulty swallowing, or progressive pain. Gut-health content should not delay care.

    What is the bottom line on gut control?

    The gut influences more than digestion through nerve pathways, immune activity, microbial metabolites, gut hormones, bile acids, and barrier function. That influence is real, but the internet often exaggerates it into a master-control story. A better model is feedback: meals, microbes, stress, sleep, medications, and movement all send signals through the digestive system, and the body responds with comfort, gas, appetite, stool changes, or energy shifts. Use gut health as a pattern-recognition tool, not as a diagnosis. Start with steady habits, track changes carefully, and bring persistent or alarming symptoms to a qualified clinician. The gut is important enough to respect and complicated enough not to reduce to one cause, one food, one microbe, one supplement, or one viral explanation. Better gut decisions usually come from boring tracking, gradual changes, and proportionate clinical care.

    Image prompts:

    • Hero image: Educational editorial image of a calm human silhouette with subtle connecting lines from the abdomen to the brain, immune cells, and energy icons, neutral medical-wellness style, no products, no logos. Alt text: Illustration of gut signals connecting digestion with the brain, immune system, and energy.
    • In-article image: Clean diagram-style flat lay showing fiber foods, water, sleep tracker, walking shoes, and a symptom journal arranged around a simple gut icon, natural light, no branded products. Alt text: Gut-support habits including fiber foods, water, movement, sleep, and symptom tracking.

  • Why Your Digestion Feels Different Every Week

    Why Your Digestion Feels Different Every Week

    Digestion can feel different every week because gut motility, stool water, gas production, stress hormones, sleep timing, menstrual hormones, medications, alcohol, fiber intake, and meal composition change from week to week. The pattern usually is not random; it often reflects repeated inputs that are hard to notice without tracking them.

    How did we evaluate weekly digestion changes?

    We evaluated weekly digestion changes by separating normal digestive variability from patterns that deserve medical attention. Human physiology references from the National Institute of Diabetes and Digestive and Kidney Diseases, peer-reviewed gut microbiome research, and clinical diet literature received more weight than anecdotal explanations. We prioritized inputs people can observe directly, including meal timing, fiber amount, fluid intake, sleep, stress, alcohol, menstrual-cycle timing, and medication changes. We excluded product-specific advice because this cold-stage guide is educational, not a buying guide. The limitation is important: a symptom diary can clarify patterns, but it cannot rule out conditions that require evaluation. We also treated single bad days as weaker evidence than repeated clusters over time. Persistent pain, bleeding, unexplained weight loss, fever, nighttime diarrhea, repeated vomiting, or sudden severe change should be discussed with a clinician.

    Why can digestion change from one week to the next?

    Digestion changes weekly because the gastrointestinal tract responds to recent inputs rather than a fixed personal setting. The NIDDK explains that digestion moves food through the GI tract while nerves, hormones, muscles, enzymes, and gut bacteria coordinate breakdown and absorption. A week with later dinners, less sleep, more alcohol, less water, higher fat meals, or different fiber intake can change transit time and stool water. A week with more beans, onions, wheat, apples, protein bars, or sugar alcohols can change fermentation and gas. Stress can alter gut-brain signaling, and travel can shift meal timing, bathroom timing, and hydration. Menstrual-cycle changes can alter bowel patterns in some people. These drivers can overlap, which makes the result feel random. A seven-day view usually reveals more than a single bad day because patterns need repetition, not just memory.

    What role does fiber play in week-to-week digestion?

    Fiber changes digestion because different fibers hold water, add stool bulk, and feed colonic microbes at different rates. A review in Nutrients describes dietary fiber as a broad category that includes soluble, insoluble, viscous, and fermentable fibers, not one single substance. Soluble fibers such as psyllium can hold water and support stool form, while highly fermentable fibers such as inulin can increase gas when intake rises quickly. Insoluble fibers from wheat bran or vegetable skins can increase stool bulk, but tolerance varies by person and meal pattern. A low-fiber weekday followed by a high-fiber weekend can create a visible swing in stool form. The useful question is not “Is fiber good?” The useful question is “Which fiber changed, how much changed, how quickly did it change, and what else changed that day or weekend?”

    How do sleep and stress affect digestion?

    Sleep and stress affect digestion through the gut-brain axis, autonomic nervous system, and daily circadian timing. A review in Frontiers in Psychiatry describes bidirectional communication between the gut microbiota and central nervous system, although human responses vary and causality is not always simple. Short sleep can change meal timing, caffeine intake, appetite, and physical activity the next day. Psychological stress can change gut motility, visceral sensitivity, and bathroom routines for some people. Circadian disruption from late meals or shift work can make the same food feel different at a different time. These effects do not mean symptoms are imaginary. They mean the nervous system and digestive system share control loops. Tracking bedtime, wake time, caffeine, and stress alongside meals often explains swings that food lists miss, especially during busy weeks or travel periods.

    Why can the same meal feel fine once and uncomfortable later?

    Lifestyle factors connected to weekly digestion changes.
    Lifestyle factors connected to weekly digestion changes.

    The same meal can feel different because context changes the digestive load. A burrito eaten after a high-fiber breakfast, two coffees, poor sleep, and a stressful commute is not the same digestive event as the same burrito eaten after a normal night and a light lunch. Fat slows gastric emptying, fiber changes stool water and fermentation, and large portions stretch the stomach more than smaller portions. FODMAP-rich ingredients such as onion, garlic, wheat, beans, milk, apples, and certain sweeteners can ferment differently depending on dose and recent intake. Monash University researchers who developed the low-FODMAP approach emphasize that FODMAP tolerance is dose-dependent rather than all-or-nothing. The lesson is practical: repeated discomfort after the same food matters, but one uncomfortable meal rarely identifies the full trigger. Dose, timing, and the previous 24 hours matter more.

    What should you track before assuming the problem is random?

    Track timing, stool pattern, meal composition, hydration, sleep, stress, medications, alcohol, caffeine, exercise, and menstrual-cycle timing before assuming digestion is random. The Bristol Stool Form Scale gives a simple shared language for stool form, and a clinical review in Journal of Neurogastroenterology and Motility describes stool form as a useful proxy for intestinal transit time. A useful diary does not need calorie math. It needs consistent fields: wake time, first meal, fiber-heavy foods, dairy, high-fat meals, unusual sweeteners, bowel movements, pain, bloating, and stress level. Record the data for 10 to 14 days, then look for clusters across meals, sleep, and bowel timing. One clue rarely explains everything. Repeated combinations usually explain more than isolated foods, especially when weekends, travel, or stressful workdays differ from weekdays.

    When should changing digestion be checked by a clinician?

    Changing digestion should be checked when the pattern is severe, persistent, sudden, or paired with red-flag symptoms. Educational tracking is reasonable for mild, short-term swings, but it should not delay care for blood in stool, black stool, unexplained weight loss, fever, dehydration, persistent vomiting, nighttime diarrhea, anemia, new symptoms after age 50, or severe localized pain. The NIDDK notes that many digestive symptoms can have multiple causes, which is why context and duration matter. Medication changes, recent antibiotics, pregnancy, immune suppression, recent travel illness, and family history of gastrointestinal disease also change the risk calculation. A clinician can decide whether labs, stool tests, imaging, endoscopy, dietitian referral, or medication review is appropriate. A diary helps that visit because it turns vague timing into usable information and reduces guesswork during care decisions.

    What questions do people ask about changing digestion?

    Can normal digestion vary every week?

    Yes. Normal digestion can vary with fiber amount, fluid intake, sleep timing, travel, stress, menstrual-cycle timing, alcohol, caffeine, and meal size. The key distinction is whether the variation is mild and explainable or severe, persistent, and worsening.

    Does bloating always mean a specific food is bad for me?

    No. Bloating can reflect portion size, fermentation, swallowed air, constipation, stress, menstrual-cycle timing, or a high-FODMAP load. A repeated pattern after the same food is more useful than one uncomfortable meal.

    How long should I track digestion?

    Track for 10 to 14 days if symptoms are mild and stable. That window usually covers weekdays, weekends, sleep differences, social meals, and stress changes. Seek care sooner for red-flag symptoms.

    Can stress really change stool pattern?

    Yes. Stress can affect gut motility, visceral sensitivity, appetite, caffeine intake, and bathroom timing. That does not make symptoms imaginary; it means the gut and nervous system communicate continuously.

    Why does travel change digestion?

    Travel changes meal timing, hydration, movement, sleep, bathroom access, alcohol intake, and food choices. Those changes can alter transit time and stool water even when no single travel food is the cause.

    Should I cut out foods immediately?

    Avoid cutting out many foods at once unless a clinician or dietitian recommends it. Broad restriction can obscure patterns and make eating harder. A better first step is tracking repeated dose-and-timing relationships.

    For a detailed comparison of specific products and strains, see Why Digestive Relief Feels Temporary and What to Compare Next.

    What is the bottom line?

    Weekly digestion changes usually have a pattern, even when the pattern is not obvious. Meal timing, fiber type, fluid intake, sleep, stress, alcohol, caffeine, menstrual-cycle timing, travel, and medications can all change motility, stool water, and gas production. Start with a simple two-week diary before blaming one food or one supplement. Compare weekdays with weekends, early dinners with late dinners, high-fiber days with low-fiber days, and rested mornings with short-sleep mornings. If symptoms are severe, persistent, sudden, or paired with red flags, skip the self-experiment and get medical guidance. If the pattern points toward supplement comparison later, a separate buying guide can help compare options without mixing education and product decisions. The main goal is to replace “random” with a clearer set of repeatable clues that someone can actually act on confidently.

  • Chest Pain After Eating: When It Might Be Reflux and When to Get Help

    Chest Pain After Eating: When It Might Be Reflux and When to Get Help

    Chest pain after eating can come from reflux, esophageal spasm, trapped gas, gallbladder pain, muscle strain, anxiety, or heart-related causes. Because heart pain and digestive pain can overlap, new, severe, persistent, crushing, unexplained, or spreading chest pain deserves urgent medical evaluation before assuming it is indigestion.

    How did we evaluate chest pain that comes after eating?

    We evaluated post-meal chest pain by separating emergency-risk patterns from common digestive patterns. Medical references from Mayo Clinic, NIDDK, MedlinePlus, Cleveland Clinic, and the American College of Gastroenterology carried more weight than anecdotal symptom descriptions. We prioritized signs that help a person decide whether to seek care, track meal-related patterns, or discuss reflux and esophageal causes with a clinician. We excluded product recommendations because a cold educational article should explain the symptom pattern without pushing antacids, remedies, or any brand.

    When is chest pain after eating an emergency?

    Chest pain after eating is an emergency when the pain is new, severe, unexplained, persistent, pressure-like, or paired with shortness of breath, sweating, faintness, nausea, jaw pain, back pain, shoulder pain, or arm pain. Mayo Clinic says severe chest pain or new unexplained chest pain or pressure lasting more than a few moments should prompt emergency medical care. MedlinePlus warns that chest pain with shortness of breath or pain in the jaw or arm can signal a heart problem. A meal trigger does not rule out the heart because heart symptoms can appear during rest, stress, exertion, or digestion. The safest rule is simple: evaluate the dangerous possibilities first. After a clinician has considered heart-related causes, digestive explanations such as reflux, esophageal irritation, or gas become more reasonable to explore.

    Why can reflux cause chest pain after meals?

    Reflux can cause post-meal chest pain when stomach contents move upward into the esophagus and irritate tissue behind the breastbone. The NIDDK reflux overview describes heartburn and regurgitation as common GER and GERD symptoms, and those symptoms often cluster after larger meals, trigger foods, lying down, or bending. Cleveland Clinic explains that acid reflux can feel like burning chest pain near the sternum, which is why people often confuse reflux pain with heart pain. Reflux pain may feel burning, sour, bitter, or pressure-like, but symptom feel alone cannot prove the cause. A clinician may ask about timing, regurgitation, swallowing symptoms, medication use, pregnancy, smoking, alcohol, and meal size. Reflux becomes more likely when episodes repeatedly follow meals and improve with upright posture, but it is still not a self-diagnosis.

    What non-heart digestive causes can mimic post-meal chest pain?

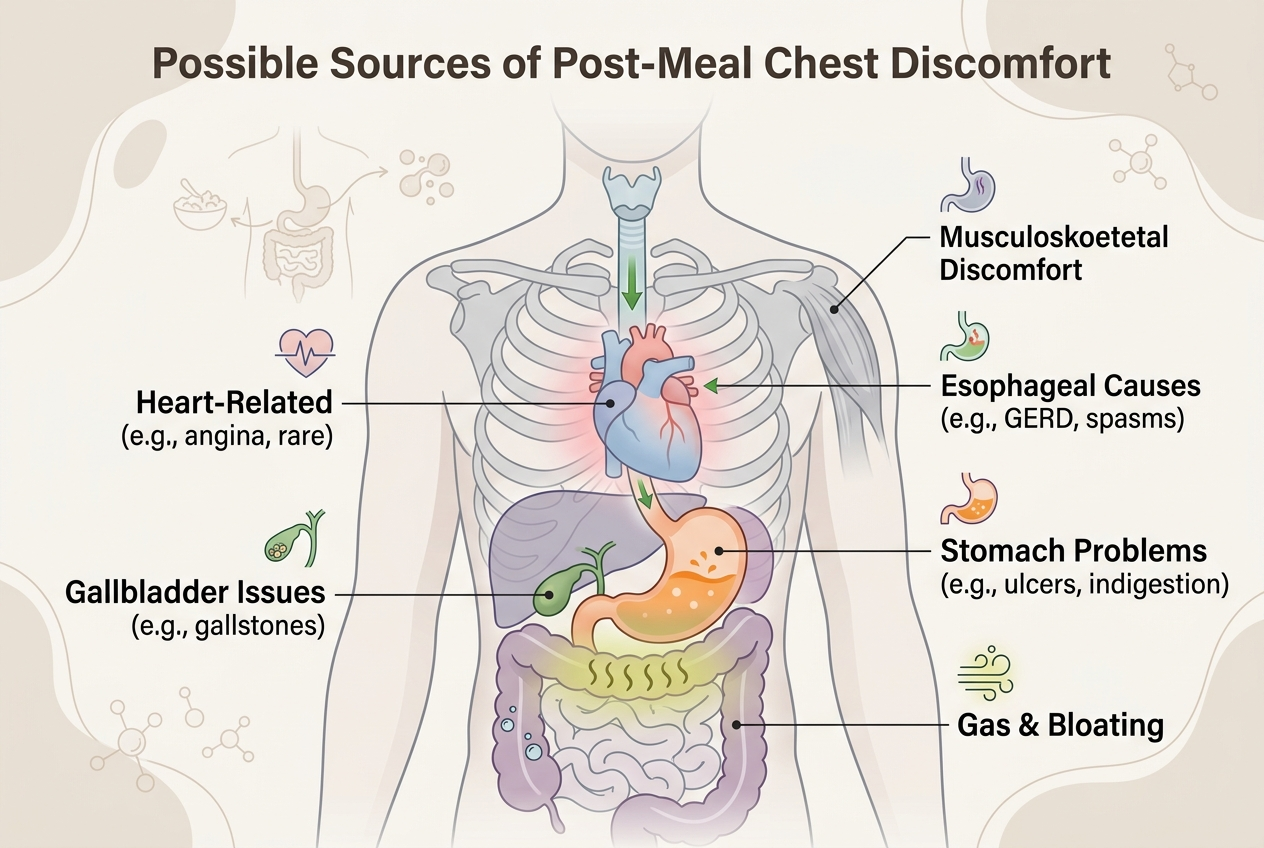
    Several digestive and nearby causes can mimic chest pain after eating. Esophageal spasm can create squeezing pain because the esophagus runs through the chest. Swallowing problems, pill irritation, or food sticking can create pain that feels centered behind the breastbone. Gas distension can push discomfort upward, especially after carbonated drinks, fast eating, large meals, or constipation. Gallbladder pain can follow fatty meals and may sit in the upper abdomen or right upper side while radiating toward the back or shoulder. Muscular chest-wall strain can feel worse with movement or pressure on the ribs. Anxiety can amplify normal digestive sensations and chest tightness, but anxiety should not be used to dismiss new chest pain. The American College of Gastroenterology notes that GERD-related chest pain can resemble angina, so cardiac evaluation comes before assuming the esophagus is responsible.

    What patterns are useful to track before a medical visit?

    Diagram of possible causes of chest pain that comes after eating.
    Diagram of possible causes of chest pain that comes after eating.

    A post-meal chest-pain diary should track time of onset, meal size, trigger foods, alcohol, caffeine, carbonated drinks, posture, exertion, stress, bowel pattern, medications, and how long the pain lasts. The diary should also record whether symptoms include sour regurgitation, trouble swallowing, nausea, sweating, shortness of breath, dizziness, or pain spreading beyond the chest. This pattern helps a clinician separate reflux-like episodes from exertional, cardiac, biliary, muscular, medication-related, or anxiety-linked patterns. A practical diary uses one line per episode: meal, time, pain location, intensity from 0 to 10, associated symptoms, and what changed it. Avoid testing multiple fixes at once because that makes the pattern harder to read. If chest pain is severe, new, or unexplained, tracking should wait until urgent causes have been evaluated.

    What should you avoid doing when chest pain follows food?

    Do not assume chest pain is harmless because it starts after food. Do not drive yourself to urgent care during severe chest pressure, shortness of breath, faintness, or spreading pain. Do not use repeated antacids, baking soda, alcohol, or extreme fasting as a substitute for evaluation. Do not keep exercising through chest pain to “test” whether it is digestive. Do not ignore swallowing trouble, vomiting blood, black stools, unintentional weight loss, persistent vomiting, or pain that wakes you from sleep. The American College of Gastroenterology reflux resource says people should not assume chest pain is esophageal until a physician has evaluated potential heart causes. The safest next step depends on severity: emergency help for red flags, medical follow-up for recurrent unexplained episodes, and tracking for mild repeat patterns after danger signs are absent.

    What questions do people ask about chest pain after eating?

    Can heartburn feel like chest pain?

    Yes. Heartburn can feel like burning pain behind the breastbone, especially after meals or lying down. The problem is that heart-related pain can overlap, so new or unexplained chest pain should not be labeled heartburn without appropriate evaluation.

    Can gas cause chest discomfort after eating?

    Gas can cause pressure, bloating, belching, and upper abdominal discomfort that may feel close to the chest. Gas should not be blamed for crushing, spreading, severe, or unexplained chest pain.

    Why does chest pain happen after a large meal?

    A large meal can increase stomach pressure, reflux risk, belching, and upper abdominal distension. Fatty meals can also slow stomach emptying for some people, which may make reflux-like symptoms more noticeable.

    Is chest pain after eating always GERD?

    No. GERD is one possible explanation, but heart conditions, esophageal spasm, gallbladder issues, muscle strain, anxiety, medication irritation, and swallowing disorders can also fit parts of the pattern.

    Should I lie down if my chest burns after food?

    Lying down can worsen reflux-like symptoms because gravity no longer helps keep stomach contents down. If the pain is new, severe, pressure-like, or paired with emergency symptoms, position changes are not enough; seek urgent help.

    When should I call a doctor instead of waiting?

    Call a clinician for recurrent post-meal chest pain, unexplained episodes that resolve, swallowing trouble, persistent reflux symptoms, vomiting, weight loss, black stools, or pain that keeps returning. Call emergency services for severe, new, persistent, spreading, or breathing-related chest pain.

    What is the bottom line on chest pain after eating?

    Chest pain after eating can be digestive, but it is not automatically digestive. Reflux, gas, esophageal spasm, gallbladder pain, muscle strain, and anxiety can all follow meals, while heart-related pain can overlap with indigestion. Treat red flags as urgent, then use pattern tracking and medical follow-up to sort out repeat meal-related episodes.

    Image prompts:

    • Hero image: Calm educational scene with a dinner plate, water glass, upright chair, and a simple symptom diary on a kitchen table; neutral health editorial style, no products, no logos, no emergency imagery. Alt text: Meal and symptom diary used to track chest pain after eating.
    • Inline image: Clear medical-style infographic showing possible sources of post-meal chest discomfort: heart, esophagus, stomach, gas, gallbladder, and chest wall; neutral colors, no frightening imagery. Alt text: Diagram of possible causes of chest pain that comes after eating.

  • Why Your Digestion Feels Different Every Week

    Why Your Digestion Feels Different Every Week

    Digestion can feel different every week because gut motility, meal timing, fiber intake, hydration, stress, sleep, hormones, medications, and recent infections all shift how fast food and gas move through the gastrointestinal tract. A weekly change is not automatically random. It is often a pattern created by repeatable inputs.

    How did we evaluate weekly digestion changes?

    We evaluated weekly digestion changes by separating normal digestive variability from warning signs that need medical attention. We prioritized NIDDK anatomy and physiology references, peer-reviewed reviews on circadian rhythm and gut motility, and clinical references on the gastrocolic reflex because those sources explain mechanisms rather than anecdotes. We excluded detox language, microbiome-reset promises, and single-cause explanations because this cold-stage guide is educational only. The limitation is personal context: bowel rhythm can change from harmless routine shifts, but persistent pain, bleeding, fever, unexplained weight loss, or major new bowel changes require a clinician. This article focuses on pattern recognition, not diagnosis, and uses plain categories that help people compare one week with the next. It also treats normal variation as data, not as proof that something is wrong right now today in daily life patterns.

    Why does digestion change even when meals look similar?

    Digestion changes because the gastrointestinal tract responds to more than food ingredients. The NIDDK digestive-system guide explains that nerves and hormones help control digestion while organs move food, break it down, absorb nutrients, and form stool. Two salads can behave differently if one is eaten after poor sleep, low water intake, travel, extra coffee, a stressful workday, or a skipped breakfast. Fiber type also matters: beans, onions, wheat, apples, oats, and leafy greens can affect stool form and gas differently because they contain different fermentable carbohydrates and textures. Fat slows gastric emptying for some meals, while large meals stretch the stomach more than small meals. Weekly digestion therefore reflects meal composition, nervous-system state, hydration, and timing together, not one isolated food. The same food can feel different when the body context changes slightly.

    How does the gastrocolic reflex affect weekly bowel patterns?

    The gastrocolic reflex can make bowel urgency feel unpredictable, even when it follows a clear meal pattern. The NCBI Bookshelf review on the gastrocolic reflex describes it as a physiological reflex that increases lower gastrointestinal motility after food stretches the stomach. A bigger breakfast, a high-fat brunch, or a fast meal can create a stronger colon response than a small snack. Coffee can add a separate stimulation cue for some people. If weekday breakfasts are rushed and weekend meals are larger, bowel timing may shift every week without a new disease process. The practical pattern is timing: symptoms that appear soon after meals often track stomach stretch, meal size, fat content, caffeine, and routine. A simple log should record when eating starts, when urgency appears, and what changed that day, including portion size and pace.

    Why do sleep, travel, and schedule changes affect the gut?

    Sleep, travel, and schedule changes affect the gut because digestive organs follow circadian timing. A review in Cellular and Molecular Gastroenterology and Hepatology reports that circadian rhythms regulate gastrointestinal physiology, including motility, digestion, absorption, and electrolyte balance. Late dinners, shift work, jet lag, irregular wake times, and weekend sleep-ins can shift when the bowel is ready to move. Travel adds dehydration, different foods, long sitting, and bathroom avoidance, which can slow stool movement. A person may then swing from constipation during travel to looser stools after returning to normal meals and coffee. This is not proof that the gut is fragile. It shows that the gut acts like a timed system. Regular meals, morning light, fluid intake, and movement often reveal whether schedule disruption is the main driver behind the weekly change pattern.

    Can hormones or the menstrual cycle change digestion week to week?

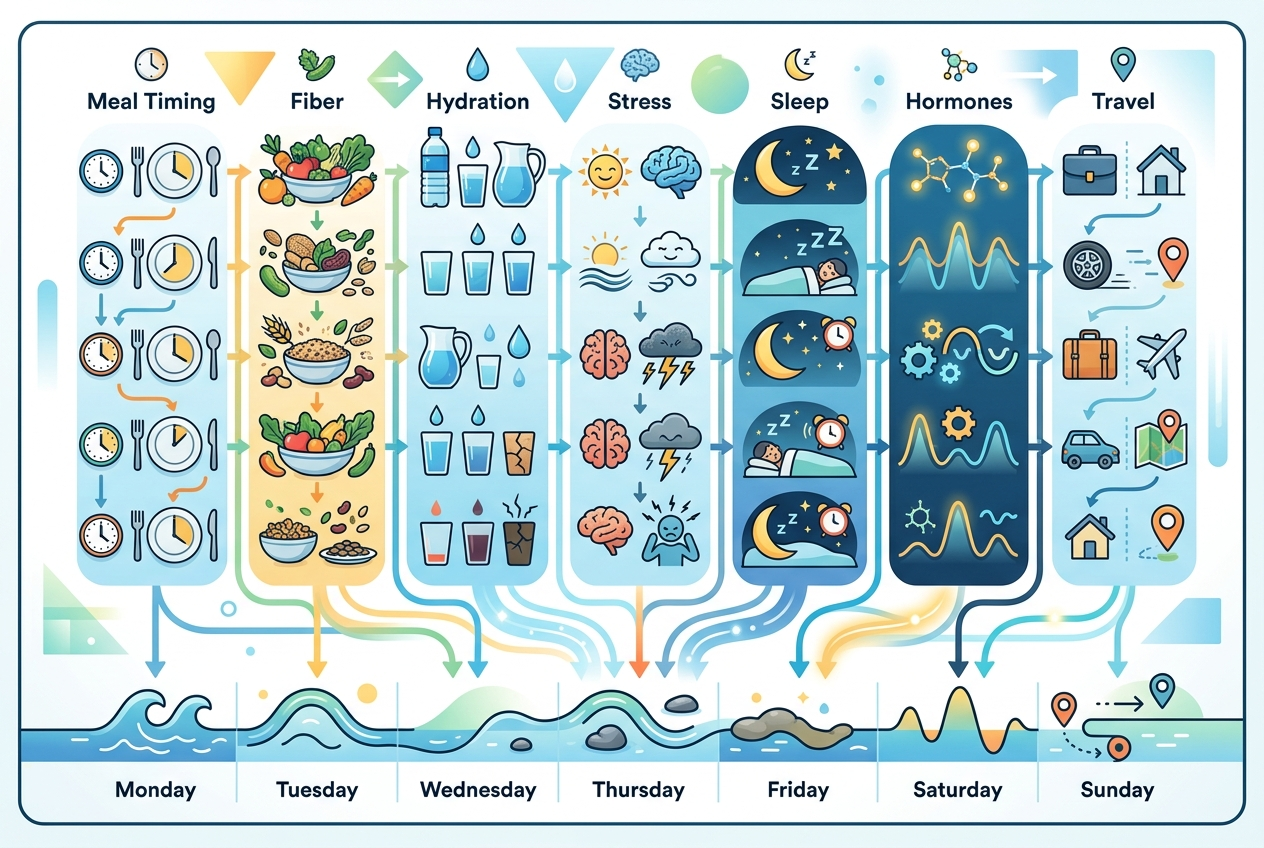
    Diagram of weekly factors that can change digestion patterns.
    Diagram of weekly factors that can change digestion patterns.

    Hormones can change digestion week to week, especially across the menstrual cycle. A review on irritable bowel syndrome and the menstrual cycle reports that menstrual-cycle phase can affect bowel habits and may increase diarrhea, bloating, and abdominal pain in some people, with stronger effects in people who already have gut sensitivity. Prostaglandins, progesterone, estrogen shifts, pain, sleep disruption, and food-craving changes can all alter bowel rhythm around the same calendar window each month. The pattern can look weekly if symptoms begin before bleeding, peak during the first days, and settle afterward. A cycle-aware log is useful because it separates food blame from timing. The goal is not to label every symptom hormonal; it is to notice whether predictable dates change stool form, gas, urgency, or constipation in a repeatable way across months and cycles.

    What is the safest way to find the pattern?

    The safest way to find the pattern is to track a small set of variables for two weeks without changing everything at once. Record meal timing, fiber-heavy foods, dairy, alcohol, caffeine, water intake, sleep duration, stress level, bowel timing, stool form, and any new medication or routine change. Avoid starting a strict elimination diet from one bad week because removing many foods can hide the real signal and create nutrition gaps. The better test changes one variable for three to four days while the rest of the routine stays stable. Red flags change the plan: blood in stool, black stool, persistent vomiting, fever, severe dehydration, unintended weight loss, nighttime diarrhea, or new symptoms after age 45 deserve medical guidance. Pattern tracking works best for mild, recurring variability; it is not a substitute for care when symptoms are severe or escalating.

    What questions do people ask about digestion changing every week?

    Is it normal for bowel movements to vary by week?

    Some variation is normal because sleep, stress, hydration, meal timing, and fiber intake change from week to week. A stable person can still have different stool timing after travel, large meals, or a disrupted schedule.

    Why do weekends change my digestion?

    Weekends often change wake time, coffee timing, alcohol intake, restaurant meals, movement, and bathroom routine. Those inputs can shift the gastrocolic reflex, stool water content, and gas production.

    Can stress really change digestion that fast?

    Stress can change gut sensation, motility, appetite, and bathroom timing through nervous-system signaling. The effect can appear quickly, especially when stress also changes coffee, sleep, and meal choices.

    Should I blame one food when symptoms appear?

    One food is possible, but a single meal is not enough evidence. Repeated timing, portion size, preparation, and co-factors matter more than one isolated bad day.

    How long should I track symptoms?

    Two weeks is usually enough to spot obvious timing patterns, and one full menstrual cycle is better for cycle-linked symptoms. Track lightly, because obsessive logging can make normal variation feel threatening.

    When should I stop self-tracking and call a clinician?

    Stop self-tracking if symptoms are severe, persistent, new, or paired with blood, fever, dehydration, vomiting, unexplained weight loss, or nighttime diarrhea. Those signs need medical judgment rather than spreadsheet detective work.

    For a detailed comparison of specific products and strains, see Why Digestive Relief Feels Temporary and What to Compare Next.

    What is the bottom line on weekly digestion changes?

    Weekly digestion changes usually come from repeatable shifts in motility, timing, hydration, fiber, stress, sleep, travel, hormones, or recent illness. The pattern becomes clearer when meals, bowel timing, stool form, and schedule changes are logged together. If red flags appear, medical evaluation matters more than trying to force a pattern from incomplete notes alone at home.

    Image prompts:

    • Hero image: Calm editorial image of a weekly calendar beside simple meals, a water glass, walking shoes, and a sleep tracker, bright neutral health-education style, no brand logos. Alt text: Weekly digestion pattern calendar with meals, hydration, sleep, and movement cues.
    • Inline image: Clean infographic showing digestion inputs across a week: meal timing, fiber, hydration, stress, sleep, hormones, and travel, connected to bowel rhythm. Alt text: Diagram of weekly factors that can change digestion patterns.

  • Does the Food You Cook Affect Your Gut Microbiome If You Don’t Eat It?

    Does the Food You Cook Affect Your Gut Microbiome If You Don’t Eat It?

    Food you cook or prepare can affect your gut microbiome indirectly, but the effect is usually small unless you also ingest microbes or residues. Kitchen exposure can move food-associated bacteria to your hands, mouth, surfaces, and household environment. Eating pattern, fiber intake, fermented foods, antibiotics, and sanitation habits shape the gut microbiome far more strongly.

    How did we evaluate whether cooking without eating changes the gut microbiome?

    We evaluated this question by separating direct gut exposure from indirect environmental exposure. Human diet studies received the most weight because stool microbiome changes require food components, live microbes, or metabolites to reach the gastrointestinal tract. We treated one-time kitchen contact as a weaker signal than repeated swallowed exposure across days or weeks. Household microbiome studies, food safety guidance, and hand-transfer research received secondary weight because they explain how microbes move through kitchens but do not prove durable gut colonization. We also separated viable organisms from nonliving microbial fragments, because DNA detected on a surface does not always equal a living microbe. Claims about cooking aromas, steam, or touching food “rebalancing” gut bacteria were excluded because current human evidence does not show a reliable microbiome effect without ingestion. The final answer treats food preparation as a plausible exposure source and diet as the stronger, better-supported driver.

    How could preparing food affect your gut microbiome without eating it?

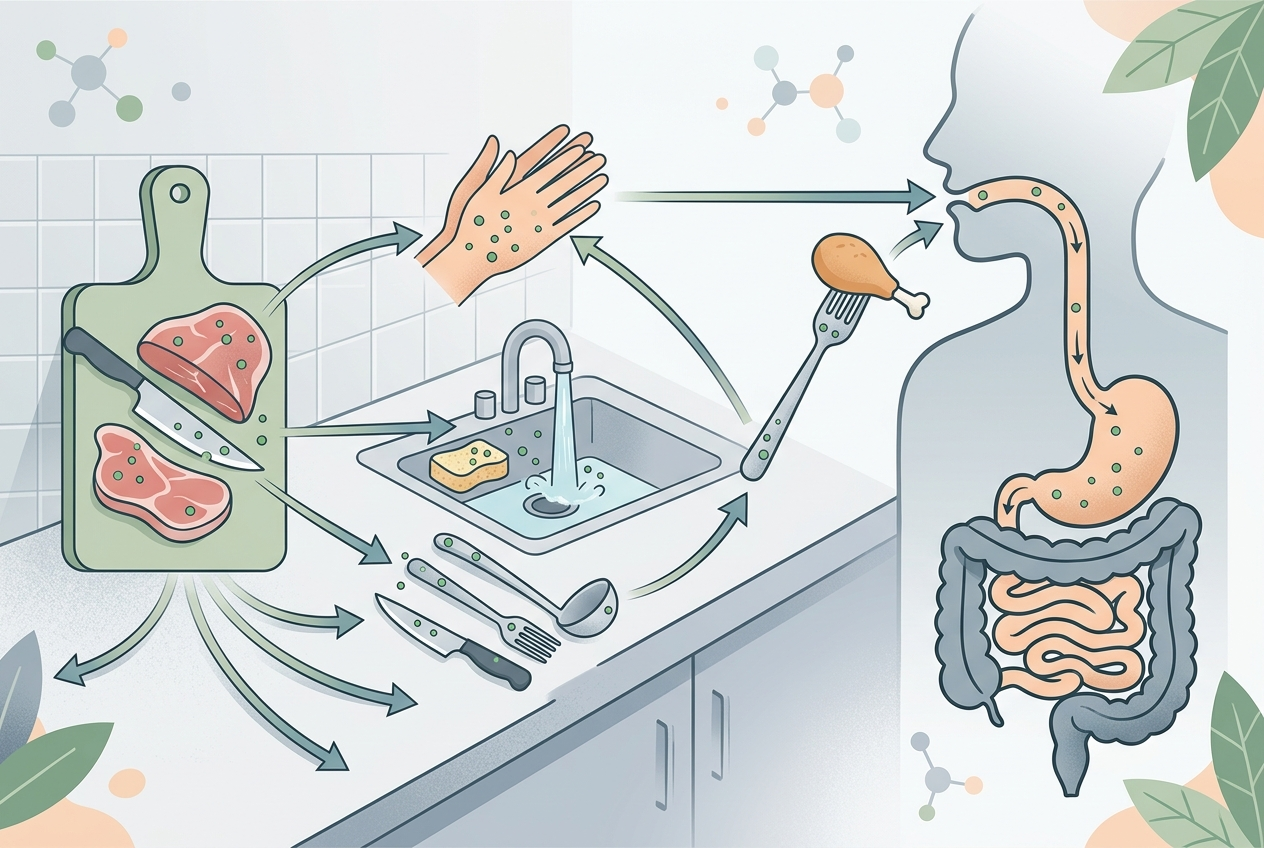
    Food preparation can affect the gut microbiome only through transfer routes that eventually reach the digestive tract. Raw vegetables, herbs, fermented dough, yogurt, meat juices, cutting-board residues, and sink splash can move microbes to fingers, utensils, counters, and phones. The hands can then move small amounts of those microbes to the lips, mouth, or swallowed saliva. The household microbiome can also shift because kitchens collect food particles, moisture, skin cells, and cleaning chemicals. A Science study from the Home Microbiome Project found that people and their homes share microbial signatures over time, which supports environmental transfer as a real pathway. This evidence is directional, not proof that chopping one onion changes stool bacteria. The likely effect is modest, transient, and heavily diluted by stomach acid, bile acids, meal composition, bowel transit time, and the existing gut microbiota. Skin microbiome changes may occur faster than stool microbiome changes, but they are not the same outcome.

    What evidence shows diet matters more than kitchen exposure?

    Controlled diet research gives the clearest answer: what you eat matters much more than what you merely handle. In a controlled feeding study published in Nature, David et al. found that animal-based and plant-based diets shifted human gut microbial communities within days, including changes in bile-tolerant bacteria and fiber-fermenting taxa. That study measured ingestion, not kitchen contact, so it supports a strong diet-gut link rather than a strong cooking-exposure link. Dietary fiber, resistant starch, polyphenols, and fermented foods provide substrates or organisms that reach the colon. Food aromas and skin contact do not provide the same colon-level input. Human gut sequencing studies generally measure stool, not airborne or skin exposure, so their strongest inference remains dietary. The gut microbiome functions like an ecosystem with repeated nutrient pressure: regular meals change available fuel, pH, fermentation products, and short-chain fatty acid production. Occasional environmental exposure can seed microbes, but repeated ingestion selects which microbes persist.

    Can food microbes survive cooking, handling, or kitchen surfaces?

    Diagram-style illustration of how food preparation can move microbes from food to hands, surfaces, and the mouth.
    Diagram-style illustration of how food preparation can move microbes from food to hands, surfaces, and the mouth.

    Food microbes can survive preparation when temperature, moisture, salt, acidity, and cleaning practices allow survival. Raw produce can carry soil-associated bacteria, fermented foods can carry lactic acid bacteria such as Lactobacillus and Leuconostoc, and raw meat can carry food-safety organisms that belong on food-safety checklists rather than wellness routines. Cooking reduces many viable microbes when foods reach appropriate internal temperatures, while knives, sponges, boards, and sink areas can retain residues. The FDA’s safe-food-handling guidance emphasizes clean hands, separated raw foods, correct cooking temperatures, and prompt chilling because kitchen transfer is a real exposure route. This does not mean a counter microbe automatically colonizes the colon. Colonization requires survival through saliva, gastric acid, bile, immune defenses, and competition from resident gut taxa such as Bacteroides, Prevotella, Faecalibacterium, and Bifidobacterium. Preparation affects exposure; ingestion and ecological fit determine persistence.

    When could indirect exposure matter more?

    Indirect exposure matters more when contact is frequent, microbial load is high, or the person repeatedly transfers hands to the mouth during preparation. Bakers, cheesemakers, gardeners, parents preparing infant food, and people handling fermented vegetables may experience more repeated environmental contact than someone reheating a cooked meal. Shared households also create microbial overlap through hands, surfaces, pets, bathrooms, and kitchens, so food preparation is one piece of a larger exposure web. The Home Microbiome Project found rapid microbial exchange after families moved homes, which makes household environment relevant but not diet-equivalent. Infant microbiomes may be more responsive because early gut ecosystems are still developing; adult microbiomes tend to resist short-lived exposures. The practical takeaway is simple: repeated swallowed exposure can matter, but touching, smelling, or cooking food without ingestion is unlikely to create a durable gut microbiome shift by itself.

    What practical habits support your gut microbiome while cooking?

    Microbiome-friendly cooking habits focus on two goals: reduce unwanted transfer and increase beneficial intake when you choose to eat. Wash hands before and after handling raw meat, seafood, eggs, unwashed produce, trash, and pets; the CDC recommends scrubbing with soap and water for at least 20 seconds. Use separate boards for raw animal foods and ready-to-eat foods. Clean sponges, cloths, and sink areas because wet kitchen materials can accumulate microbial biofilms. Replace worn tools when odors, staining, or persistent dampness make cleaning less reliable. For gut-supportive meals, emphasize plant diversity, legumes, whole grains, nuts, seeds, vegetables, fruit, and fermented foods that you actually consume. These foods provide fermentable carbohydrates, polyphenols, and live cultures that interact directly with gut microbes. Food preparation can shape your exposure environment, but dietary pattern supplies the strongest daily signal. Safe handling and diverse plant intake can coexist; sterile cooking is neither realistic nor necessary for a resilient household microbiome.

    What questions do people ask about cooking and the gut microbiome?

    Can smelling cooked food change gut bacteria?

    Smelling cooked food can trigger appetite, saliva, and digestive readiness, but smell alone does not deliver meaningful microbes or fiber to the colon. The gut microbiome needs swallowed material, repeated nutrient inputs, or direct microbial exposure to change in a measurable way.

    Can touching fermented foods expose you to beneficial bacteria?

    Touching fermented foods can transfer lactic acid bacteria to the hands, especially from yogurt, kimchi, sauerkraut, sourdough, kefir, or miso. That contact becomes gut-relevant only if organisms reach the mouth and survive digestion; eating fermented foods is the stronger exposure route.

    Does cooking kill all microbes in food?

    Cooking reduces many viable microbes, but it does not make every food or kitchen surface microbe-free. Internal temperature, heating time, food thickness, moisture, post-cooking handling, and storage conditions all influence what survives or returns after cooking.

    Could preparing raw meat affect the gut microbiome?

    Preparing raw meat can expose hands, boards, knives, sinks, and ready-to-eat foods to food-safety organisms. That exposure is not a microbiome wellness strategy; safe separation, cleaning, cooking, and chilling reduce unwanted transfer.

    Is steam from cooking a microbiome exposure?

    Cooking steam may carry volatile compounds and tiny droplets, but it is unlikely to deliver enough viable food microbes to reshape the gut microbiome. Swallowed food, household contact, and hand-to-mouth transfer are more plausible exposure pathways.

    What matters most for the gut microbiome day to day?

    Regular intake matters most because the gut ecosystem responds to repeated substrates. Fiber-rich plants, resistant starch, fermented foods, overall dietary pattern, medications such as antibiotics, sleep, stress, and bowel transit usually matter more than one cooking session.

  • How to Sleep Properly When Acidity from Indigestion Flares at Night

    How to Sleep Properly When Acidity from Indigestion Flares at Night

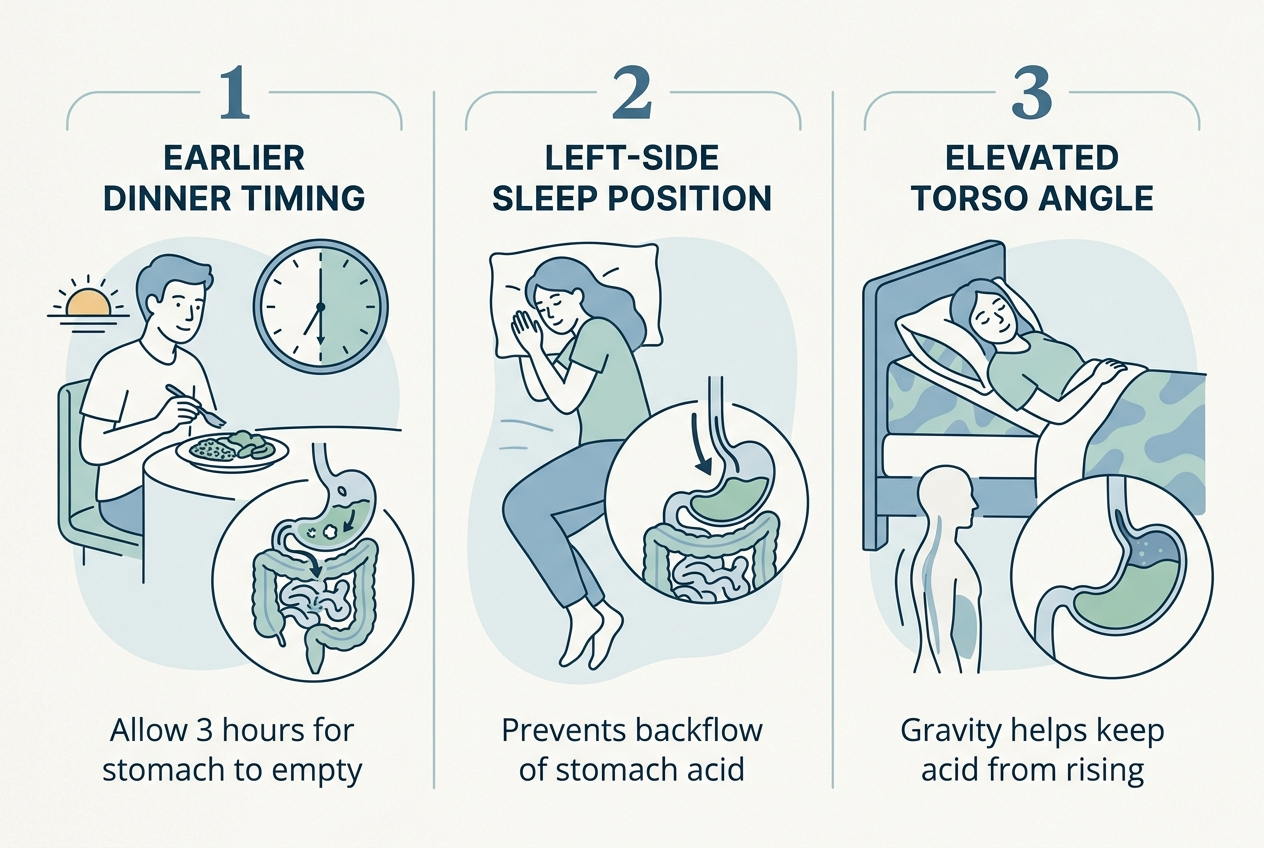
    Sleep with acidity from indigestion by keeping your upper body elevated, lying on your left side, and leaving a 2- to 3-hour gap after your last meal. Smaller evening meals, loose waistbands, and avoiding personal triggers reduce nighttime pressure. Severe chest pain, black stool, vomiting, or trouble swallowing needs prompt medical care.

    How did we evaluate safe sleep positioning for acidity from indigestion?

    We evaluated nighttime acidity by prioritizing gastroenterology guidance, human sleep-position research, and practical risk triage over anecdotal forum fixes. The American College of Gastroenterology, NIDDK, Mayo Clinic, and PubMed-indexed posture studies received more weight than single-person routines because acidity, heartburn, and indigestion can overlap without sharing one cause. We excluded supplement claims, commercial comparisons, and aggressive medication advice because this cold-stage guide answers an educational sleep question, not a buying decision. Evidence is strongest for meal timing, head-of-bed elevation, and left-side positioning; evidence is more directional for individual trigger foods, because caffeine, chocolate, mint, alcohol, and fatty meals vary by person. We treated alarm signs separately because chest symptoms, bleeding signs, swallowing trouble, and unexplained weight change require professional judgment rather than a sleep-position experiment. Practical advice was included only when it matched published clinical guidance.

    Why does acidity from indigestion feel worse after lying down?

    Lying flat reduces gravity’s help, so stomach contents can move upward more easily when the lower esophageal sphincter relaxes. The NIDDK explains that reflux occurs when stomach contents flow back into the esophagus, and common signs include heartburn and regurgitation (NIDDK). A full stomach increases pressure under the diaphragm, and a tight waistband adds mechanical compression during sleep. Indigestion also delays comfort because large meals, high-fat foods, carbonated drinks, and alcohol can keep the stomach stretched longer. Nighttime acidity therefore has a simple physics layer: stomach volume, body angle, and sphincter relaxation combine during the first hours after dinner. Symptom pattern matters more than one bad night. Repeated nighttime burning, sour taste, coughing, hoarseness, or sleep disruption deserves tracking in a seven-night log, especially when the pattern follows late meals or lying fully flat.

    Which sleep position helps most when acidity shows up at night?

    Left-side sleeping helps many nighttime acidity patterns because stomach anatomy places the gastric pocket below the esophagus more favorably in that position. A PubMed-indexed study on recumbent postprandial reflux found that right-side positioning increased acid exposure and slowed acid clearance compared with left-side positioning (PubMed). Head elevation adds a second mechanical advantage. The American College of Gastroenterology guideline lists avoiding meals within 2 to 3 hours of bedtime and elevating the head of the bed for nighttime symptoms as lifestyle measures supported by clinical guidance (ACG guideline). A wedge pillow or bed risers work better than stacking soft pillows because the torso, not only the neck, needs elevation. The practical setup is specific: left side, upper body angled upward, waist loose, and dinner fully settled before lying down. Back sleeping with elevation is a reasonable second choice when left-side sleep is uncomfortable.

    What should you do in the 3 hours before bed?

    Diagram of earlier meal timing, left-side sleep, and upper-body elevation for nighttime acidity.
    Diagram of earlier meal timing, left-side sleep, and upper-body elevation for nighttime acidity.

    The 3 hours before bed should reduce stomach volume, abdominal pressure, and stimulation. Dinner should be smaller than lunch when nighttime acidity repeats, and the last substantial meal should end at least 2 to 3 hours before lying down. Water is usually gentler than carbonation because bubbles can increase gastric distension. A short upright walk after dinner can support normal gastric movement, while intense exercise immediately after eating can add pressure for some people. Clothing matters because tight waistbands compress the abdomen during sitting and sleep. A symptom log should record meal size, meal time, alcohol, caffeine, mint, chocolate, spicy foods, high-fat foods, carbonated drinks, stress, and sleep position. Mayo Clinic lists heartburn triggers as person-specific, so the useful goal is pattern detection rather than universal restriction (Mayo Clinic). Consistency across seven nights gives better signal than one perfect evening.

    What should you avoid when nighttime acidity is active?

    Nighttime acidity usually worsens when the evening routine stacks several pressure triggers together. Large late meals create stomach volume; alcohol relaxes normal esophageal barrier function; high-fat foods can slow gastric emptying; peppermint, chocolate, coffee, and carbonated drinks can bother some people. The evidence is strongest for avoiding late meals and elevating the upper body, while trigger-food evidence is more individualized and should be tested with a log. Avoid lying flat on the right side soon after dinner when acidity is active, because right-side positioning can increase acid exposure in posture studies. Avoid tight shapewear, belts, or waistbands at bedtime because external compression raises abdominal pressure. Avoid panic-scrolling symptom forums at 2 a.m. because stress raises arousal and makes sleep harder. The better rule is boring but useful: reduce volume, reduce compression, stay upright, then sleep left-side elevated.

    When should nighttime acidity get medical attention?

    Nighttime acidity needs medical attention when symptoms are severe, persistent, unusual, or paired with alarm signs. Chest pressure, shortness of breath, pain spreading to the arm or jaw, fainting, black stool, vomiting blood, repeated vomiting, trouble swallowing, painful swallowing, unexplained weight loss, or anemia signs should not be managed as ordinary indigestion. Cleveland Clinic describes indigestion as upper-abdominal discomfort that can overlap with burning, fullness, nausea, and belching, which means symptom labels can be imprecise (Cleveland Clinic). A clinician can separate reflux patterns, medication effects, food intolerance, ulcer-related patterns, gallbladder issues, cardiac causes, and other possibilities. Occasional acidity after a heavy meal is different from repeated sleep disruption. A written log helps the visit because timing, triggers, stool changes, medications, and sleep position give the clinician concrete data. Bringing the log prevents vague recall from steering the conversation.

    What questions do people ask about sleeping with acidity from indigestion?

    Is it better to sleep on the left side or the right side?

    Left-side sleep is the better first experiment. PubMed posture research links right-side lying with higher acid exposure after meals.

    Should I stack pillows to sleep higher?

    Stacked pillows often bend the neck. A wedge pillow or bed risers lift the torso more reliably.

    How long should I wait after eating before lying down?

    A 2- to 3-hour gap is the practical target. ACG guidance includes this window for nighttime reflux patterns.

    Is milk helpful before bed?

    Milk may feel soothing briefly. Fat and volume can bother some people later, so water gives cleaner signal.

    Can stress make nighttime acidity feel worse?

    Stress can increase arousal and symptom attention. Stress does not replace triggers like late meals, alcohol, or compression.

    What is the safest plan tonight?

    Stay upright, loosen your waistband, elevate your torso, and sleep left-side. Seek urgent care for chest pressure, black stool, vomiting blood, fainting, or trouble swallowing.

  • CT vs Ultrasound vs Scope: Which Digestive Test Shows What?

    CT vs Ultrasound vs Scope: Which Digestive Test Shows What?

    CT, ultrasound, and endoscopy answer different digestive questions. CT shows cross-sectional abdominal structures, ultrasound is often used for gallbladder and liver questions, and upper endoscopy directly views the esophagus, stomach, and duodenum. The best test depends on symptoms, exam findings, red flags, and clinician suspicion.

    How did we evaluate CT, ultrasound, and endoscopy?

    We evaluated these tests by separating what each tool can see, what it cannot see, and when clinicians commonly choose it. We prioritized radiology references, NIDDK endoscopy guidance, and gastroenterology guidelines over forum anecdotes. We excluded cost rankings because insurance coverage, urgency, facility fees, sedation, and geography change pricing too much for a stable answer. This guide is educational only; a clinician must decide the correct test based on pain location, reflux symptoms, labs, pregnancy status, radiation considerations, alarm symptoms, and prior results.

    What does a CT scan show for digestive symptoms?

    A CT scan uses X-rays and computer processing to create cross-sectional images of the abdomen and pelvis. It can show bowel obstruction, diverticulitis patterns, appendicitis, kidney stones, masses, abscesses, inflammation, free air, fluid collections, and some complications that ultrasound or endoscopy might miss. RadiologyInfo describes abdominal and pelvic CT as a tool that helps evaluate abdominal pain, infection, injury, and many internal organs. CT does not directly measure acid reflux, does not biopsy stomach lining, and does not show subtle mucosal irritation as clearly as endoscopy. CT also uses ionizing radiation, and some exams use IV or oral contrast. That matters for pregnancy, kidney function, allergy history, and repeat imaging. A clinician usually chooses CT when the question is broad, urgent, deep, or structural rather than limited to the esophagus lining.

    What does an ultrasound show for digestive symptoms?

    Ultrasound uses sound waves, not ionizing radiation, to image organs and fluid-filled structures. Abdominal ultrasound is commonly used for gallstones, gallbladder inflammation, bile duct dilation, liver abnormalities, fluid, some kidney findings, and pregnancy-compatible abdominal evaluation. RadiologyInfo describes abdominal ultrasound as a test that evaluates organs such as the liver, gallbladder, spleen, pancreas, kidneys, and blood vessels. Ultrasound has limits: bowel gas can block views, body habitus can reduce image quality, and ultrasound does not inspect the inside lining of the esophagus or stomach. It also cannot rule out every cause of abdominal pain. Ultrasound is often a first-line test when the pain pattern points toward the right upper abdomen, fatty-meal symptoms, gallbladder disease, or a question where avoiding radiation is important. It is less useful for proving GERD or diagnosing microscopic inflammation.

    What does an endoscopy or scope show?

    Upper endoscopy, also called EGD, uses a flexible camera to view the esophagus, stomach, and duodenum directly. The NIDDK explains that clinicians can use upper endoscopy to investigate symptoms, take biopsies, and sometimes treat findings during the same procedure. Endoscopy can identify erosive esophagitis, ulcers, narrowing, bleeding sources, Barrett’s esophagus, gastritis patterns, celiac-related biopsy findings, and some structural problems. It cannot evaluate the entire abdomen, gallbladder, appendix, kidneys, or deep pelvic structures the way imaging can. Endoscopy often requires fasting, sedation planning, a ride home, and procedure-specific risk discussion. For reflux symptoms, endoscopy is most helpful when alarm features exist, symptoms persist despite appropriate care, or a clinician needs to inspect tissue directly. A normal endoscopy does not always exclude reflux because non-erosive reflux can require pH testing.

    How do CT, ultrasound, and scope compare?

    Infographic comparing CT scan, abdominal ultrasound, and upper endoscopy by what each test can evaluate.
    Infographic comparing CT scan, abdominal ultrasound, and upper endoscopy by what each test can evaluate.

    The simplest comparison is anatomical. CT looks broadly across abdominal structures, ultrasound focuses well on selected organs without radiation, and endoscopy inspects the upper digestive lining from inside the tract. The 2022 American College of Gastroenterology GERD guideline distinguishes endoscopy from reflux monitoring because GERD testing depends on the clinical question. A person with right upper abdominal pain after fatty meals may need ultrasound first. A person with severe unexplained abdominal pain, fever, or suspected complication may need CT. A person with trouble swallowing, bleeding, persistent reflux alarm features, or suspected ulcer may need endoscopy. No single test is the universal “best.” The better question is: what problem is the clinician trying to rule in or rule out today?

    Test Best at seeing Weak at seeing Common reason it is chosen
    CT abdomen/pelvis Deep abdominal structures, complications, broad causes Subtle lining irritation and acid exposure Severe, unclear, or urgent abdominal pain
    Abdominal ultrasound Gallbladder, bile ducts, liver, fluid, selected organs Esophagus lining, stomach lining, gas-blocked views Gallbladder-pattern pain or radiation avoidance
    Upper endoscopy Esophagus, stomach, duodenum lining, biopsies Gallbladder, appendix, kidneys, whole abdomen Alarm reflux features, ulcers, bleeding, swallowing symptoms

    What should you ask before agreeing to a test?

    Ask what question the test is meant to answer, what result would change the plan, and what risks or limitations apply. Ask whether bloodwork, stool tests, medication review, pregnancy status, kidney function, contrast allergy, or prior imaging changes the best next step. Ask whether the symptom pattern suggests gallbladder evaluation, reflux evaluation, bowel inflammation, obstruction, infection, ulcer, or another category. Ask whether the test is urgent or can be scheduled routinely. Ask what red flags should trigger emergency care before the appointment. Good questions make testing more precise: “Are we looking for gallstones, reflux damage, bleeding, obstruction, inflammation, or something else?” If the answer is vague, ask for the clinical reason in plain language. A test should answer a specific medical question, not merely satisfy anxiety.

    What questions do people ask about CT, ultrasound, and scope?

    Can a CT scan diagnose GERD?

    CT is not the standard test for GERD. It may show complications or other abdominal problems, but reflux evaluation usually relies on symptoms, endoscopy in selected cases, or reflux monitoring.

    Can ultrasound see acid reflux?

    No. Abdominal ultrasound does not directly see acid reflux in the esophagus. It is more useful for gallbladder, liver, bile duct, kidney, and fluid-related questions.

    Is endoscopy better than CT?

    Endoscopy is better for seeing the upper digestive lining and taking biopsies. CT is better for broad abdominal structures and complications outside the lining.

    Which test is safest?

    Safety depends on the person and the question. Ultrasound avoids radiation, CT uses radiation and sometimes contrast, and endoscopy involves sedation and procedure-specific risks.

    Why would a doctor order ultrasound before endoscopy?

    Doctors may choose ultrasound first when pain location, labs, or meal-triggered symptoms suggest gallbladder or liver involvement. Endoscopy answers a different question about the upper digestive lining.

    What symptoms make testing more urgent?

    Severe pain, chest pain, fainting, persistent vomiting, black stool, blood in stool, fever, dehydration, trouble swallowing, or unexplained weight loss should prompt urgent medical guidance.

    For a detailed comparison of specific products and strains, see Digestive Enzymes vs Probiotics for Meal Bloating: What Each One Does.

    What is the bottom line?

    CT, ultrasound, and endoscopy are not interchangeable. CT gives a broad structural look inside the abdomen, ultrasound is strong for gallbladder and selected organ questions without radiation, and endoscopy directly inspects the upper digestive lining. The best next test is the one that answers the clinician’s actual concern.

    Image prompts:

    • Hero image: Neutral medical education flat lay with an abstract CT image, ultrasound probe silhouette, endoscopy diagram card, clipboard, and stethoscope on a clean desk, no patient, no brand logos. Alt text: Medical desk comparing CT scan, ultrasound, and endoscopy for digestive symptoms.
    • Inline image: Clean comparison infographic with three columns labeled CT scan, abdominal ultrasound, and upper endoscopy, showing what each test sees and does not see, calm clinical colors, readable labels. Alt text: Infographic comparing CT scan, abdominal ultrasound, and upper endoscopy by what each test can evaluate.

  • Gut Issues a Week After IV Antibiotics: What Can Happen Next?

    Gut Issues a Week After IV Antibiotics: What Can Happen Next?

    Gut issues one week after IV antibiotics can happen because antibiotics disrupt intestinal bacteria, bile acid metabolism, stool water balance, and short-chain fatty acid production. Mild changes often improve gradually, but severe diarrhea, fever, blood, dehydration, intense pain, or worsening symptoms after recent antibiotics should prompt medical care.

    How did we evaluate gut issues after IV antibiotics?

    We evaluated this question by prioritizing gastroenterology references on antibiotic-associated diarrhea, Clostridioides difficile risk, microbiome recovery, hydration, and gradual diet reintroduction. Human studies and public-health guidance received more weight than supplement claims or personal anecdotes. We separated common short-term disruption from warning signs because a one-week timeline can still include clinically important complications. This article is educational only; it cannot identify the antibiotic used, the original infection, hospital exposure, immune status, or medication factors that change risk.

    Why can gut issues start a week after IV antibiotics?

    Antibiotics can change the gut ecosystem within days, and symptoms may appear after the hospital visit rather than during it. Broad-spectrum IV antibiotics can reduce susceptible gut bacteria, lower microbial diversity, alter fermentation, and change how bile acids move through the colon. The CDC notes that C. diff can occur after antibiotic exposure because antibiotics can disturb normal intestinal bacteria. That does not mean every post-antibiotic symptom is C. diff, but it explains why timing matters. Loose stool, extra gas, cramping, appetite changes, nausea, and irregular bowel movements can reflect temporary microbiome disruption, diet changes, stress, pain medication, acid reducers, or the original illness. The key distinction is trajectory. Symptoms that slowly improve are different from symptoms that intensify, cause dehydration, include blood, or appear with fever after recent antibiotic treatment.

    What symptoms are common, and what symptoms are red flags?

    Common post-antibiotic symptoms include softer stools, urgency, mild cramping, gas, bloating, appetite changes, and temporary food sensitivity. These symptoms are nonspecific because antibiotics, infection recovery, hospital meals, IV fluids, opioids, NSAIDs, proton pump inhibitors, and stress can all affect gut motility. Red flags deserve a different response: watery diarrhea three or more times per day, fever, blood or black stool, severe abdominal pain, repeated vomiting, dizziness, dehydration, confusion, or symptoms that worsen after initially improving. Mayo Clinic describes antibiotic-associated diarrhea as diarrhea that occurs while taking antibiotics or soon after, and it advises medical review for severe symptoms or possible C. diff features. A recent IV-antibiotic history raises the importance of caution because hospital exposure, strong antibiotics, and underlying infection can change risk.

    What should you do first if symptoms are mild?

    For mild symptoms, the first step is stabilizing hydration, meals, and tracking before adding complicated interventions. Oral fluids, soups, and electrolyte drinks can help replace water and sodium if stool is loose. Bland, tolerable foods such as rice, oats, bananas, potatoes, toast, eggs, yogurt if tolerated, and cooked vegetables can reduce guesswork while the gut settles. The NIDDK recommends replacing fluids and electrolytes during diarrhea, especially when symptoms are prolonged. A simple log should record stool frequency, stool form, fever, pain, meals, medicines, and hydration for several days. Avoid alcohol, very greasy meals, large amounts of sugar alcohols, and abrupt high-fiber loading while symptoms are active. If symptoms escalate instead of settling, stop self-managing and contact the clinician who prescribed or administered the antibiotic.

    How long can the gut take to feel normal again?

    Diagram explaining how antibiotics can affect gut bacteria, stool changes, hydration, and red flags.
    Diagram explaining how antibiotics can affect gut bacteria, stool changes, hydration, and red flags.

    Recovery time varies because antibiotic type, duration, dose, baseline microbiome, diet, infection severity, and hospital exposure all matter. Some people feel steadier within several days after the antibiotic course ends. Others notice irregular stool, gas, or food sensitivity for several weeks. A human microbiome study in Cell found that probiotic response and post-antibiotic microbiome recovery can be highly individualized, which means timelines are not universal. A practical expectation is to watch the direction of change rather than demanding a perfect day immediately. Improving stool frequency, better appetite, less cramping, and stable hydration are reassuring signals. New fever, worsening diarrhea, nighttime symptoms, blood, dehydration, or severe pain are not normal recovery milestones. Recent IV antibiotics should lower the threshold for calling a clinician, especially if the antibiotic name is unknown.

    What should you ask your clinician after IV antibiotics?

    A focused call or message should include the antibiotic name if known, the reason for treatment, the date of the last dose, stool frequency, fever status, pain level, hydration status, and any blood or mucus. Ask whether symptoms fit expected antibiotic-associated diarrhea, whether C. diff testing is appropriate, and whether any current medications could be worsening the gut pattern. Ask before taking anti-diarrheal medication if diarrhea is frequent, severe, bloody, or paired with fever because slowing the bowel can be inappropriate in some infections. Ask whether follow-up is needed if symptoms persist beyond several days. The goal is not to panic after every loose stool. The goal is to give the clinician enough detail to separate ordinary recovery from a complication that needs testing or treatment.

    What questions do people ask about gut issues after antibiotics?

    Can IV antibiotics upset your stomach a week later?

    Yes. Gut symptoms can appear during antibiotics or after the course because the microbiome, bile acids, stool water, diet, and motility can shift after exposure. The timeline matters most when symptoms are severe or worsening.

    Is diarrhea after antibiotics always C. diff?

    No. Antibiotic-associated diarrhea has multiple causes, and many cases are mild. C. diff becomes a bigger concern when diarrhea is frequent, watery, worsening, associated with fever or pain, or follows high-risk antibiotic or hospital exposure.

    Should I take anti-diarrhea medicine?

    Ask a clinician first if diarrhea is severe, bloody, feverish, or connected to recent IV antibiotics. Anti-diarrhea medicine may be inappropriate when an infection or C. diff is possible.

    What foods are easiest during recovery?

    Plain starches, bananas, oats, potatoes, toast, soups, eggs, and cooked vegetables are common low-friction options. Reintroduce higher-fiber foods gradually because sudden fiber increases can worsen gas.

    Can probiotics help after antibiotics?

    Some probiotic evidence is strain-specific, but results are not universal. Ask a clinician first if you are immunocompromised, severely ill, pregnant, buying for a child, or dealing with significant post-antibiotic diarrhea.

    When should I seek urgent care?

    Seek urgent care for severe abdominal pain, repeated vomiting, dehydration, confusion, bloody stool, black stool, high fever, fainting, or rapid worsening. Those symptoms sit outside normal self-care.

    For a detailed comparison of specific products and strains, see Best Probiotics After a Long Course of Antibiotics: Strain and Product Guide.

    What is the bottom line?

    Gut issues a week after IV antibiotics can be a temporary microbiome and motility disruption, but the same timeline can also overlap with antibiotic-associated diarrhea or C. diff risk. Track stool frequency, fever, pain, hydration, and medication timing. Mild symptoms can be supported with fluids and simple meals, while red flags require medical contact.

    Image prompts:

    • Hero image: Calm educational health flat lay with a glass of water, simple soup bowl, medication schedule card with no readable drug names, and a symptom tracking notebook on a neutral kitchen table, no brand logos. Alt text: Water, soup, and a symptom tracking notebook for gut issues after antibiotics.
    • Inline image: Clean editorial diagram showing antibiotic exposure, microbiome disruption, stool changes, hydration, and clinician red flags as connected steps, medical education style, no product imagery. Alt text: Diagram explaining how antibiotics can affect gut bacteria, stool changes, hydration, and red flags.

  • Can Staying Hydrated Help Acid Reflux? What Water Can and Cannot Do

    Can Staying Hydrated Help Acid Reflux? What Water Can and Cannot Do

    Hydration can support normal digestion, saliva flow, stool consistency, and meal tolerance, but water does not neutralize or cure acid reflux. For reflux-prone people, the useful goal is steady fluids across the day, smaller sips with meals, and avoiding patterns that combine large meals, late eating, carbonation, and lying down.

    How did we evaluate hydration and reflux?

    We evaluated hydration and reflux by separating fluid balance, meal timing, and gastroesophageal reflux physiology. We prioritized government medical references, dietary guidance, and nutrition consensus reports over social-media claims that water “flushes acid” or instantly stops reflux. We treated hydration as a support habit because MedlinePlus defines dehydration as a state where the body lacks as much water and fluid as it needs, while GERD involves stomach contents moving into the esophagus. We excluded cure language, alkaline-water claims, and supplement claims because hydration may influence comfort, saliva, constipation, and meal rhythm without proving reflux control. We also separated plain water from carbonated, caffeinated, acidic, and alcoholic drinks because beverage type can matter as much as fluid volume, personal tolerance, and timing.

    Can drinking water help acid reflux?

    Water can help reflux-prone digestion indirectly, but it is not an acid-reflux treatment. Small sips may clear the mouth and esophagus, support saliva, and reduce dry-throat irritation after a reflux episode. Steady hydration may also support stool consistency, which matters because constipation and abdominal pressure can worsen fullness or bloating. The National Institute of Diabetes and Digestive and Kidney Diseases describes GERD as stomach contents flowing back into the esophagus when the lower esophageal sphincter weakens or relaxes when it should not. Water does not fix that barrier. Large volumes of fluid with a heavy meal may expand stomach volume and feel uncomfortable for some people. The practical strategy is boring: sip water consistently, keep meals moderate, stay upright after eating, and track whether carbonation, late fluids, or large servings change symptoms.

    • Best use of water: steady sipping across the day.
    • Weakest claim: water cures reflux.
    • Pattern to track: large drinks plus large meals.

    What hydration pattern is usually gentlest for reflux-prone digestion?

    A gentler hydration pattern spreads fluids across the day instead of forcing most water at dinner or bedtime. Morning fluids can help replace overnight losses. Midday fluids can support normal energy, saliva, and stool consistency. Evening fluids should fit sleep and reflux patterns because some people feel worse when they drink large amounts close to lying down. The NIDDK GERD nutrition guidance says people with nighttime symptoms may improve by eating at least 3 hours before lying down or going to bed. The same timing logic can help with fluids: avoid combining a large late meal, large drink, and flat posture. Plain water is usually easier to assess than flavored drinks because caffeine, citrus, peppermint, carbonation, alcohol, and high-acid beverages can add separate variables.

    How much water do adults usually need?

    Fluid needs vary by body size, activity, heat exposure, pregnancy, lactation, medication use, illness, sweating, and diet. The National Academies’ Dietary Reference Intakes for water and electrolytes set adequate intake values for total water from foods and beverages, not just plain drinking water. Public summaries often cite approximately 3.7 liters per day for men and 2.7 liters per day for women, but those are population-level adequate intakes, not personal prescriptions. Fruits, vegetables, soups, milk, tea, coffee, and other beverages all contribute fluid. The safer self-checks are thirst, urine color, urination frequency, heat exposure, exercise, and dizziness. People with kidney disease, heart failure, liver disease, diuretic use, or fluid restrictions should follow clinician guidance instead of generic water targets. More water is not automatically better.

    What drinks commonly confuse reflux tracking?

    Carbonated water, coffee, alcohol, citrus drinks, peppermint tea, high-sugar drinks, and very cold or very hot beverages can confuse reflux tracking because each drink adds a separate variable. Carbonation can increase belching and stomach pressure for some people. Coffee contains caffeine and other compounds that may affect tolerance differently by person. Citrus adds acidity. Alcohol can affect lower-esophageal-sphincter tone and sleep quality. Peppermint can feel soothing in the mouth but may bother some reflux-prone people. A clean tracking method keeps plain water stable while testing one drink category at a time. If symptoms change, the person can compare timing, serving size, meal size, posture, and sleep position. The goal is not a universal forbidden-drink list. The goal is to identify which beverage pattern repeatedly matches symptoms for one person across at least several similar meals.

    What questions do people ask about hydration and reflux?

    Is cold water bad for acid reflux?

    Cold water is not universally bad for acid reflux. Some people prefer room-temperature water because very cold drinks feel uncomfortable, but personal tolerance matters more than a rule.

    Does alkaline water stop reflux?

    Alkaline water should not be treated as a proven reflux fix. If someone uses it, they should track symptoms and still address meal timing, posture, trigger drinks, and medical red flags.

    Should I drink water with meals or between meals?

    Most people can drink water with meals, but large volumes may feel uncomfortable with large meals. Smaller sips during meals and steadier fluids between meals are easier to test.

    Can dehydration make digestion feel worse?

    Dehydration can contribute to thirst, dry mouth, dizziness, and reduced fluid available for normal body functions. Low fluid intake can also make constipation patterns harder, which may increase bloating or pressure.

    Is sparkling water okay for reflux?

    Sparkling water is a personal-tolerance question. Carbonation may increase belching or pressure for some reflux-prone people, so compare still water and sparkling water at the same meal size.

    What symptoms mean hydration is not the main issue?

    Trouble swallowing, vomiting, black stools, unexplained weight loss, severe chest pain, fever, or persistent symptoms need medical review. Hydration tracking should not delay care for red-flag symptoms.

    Can drinking water before bed trigger reflux?

    A small sip before bed is usually different from drinking a large bottle and lying flat. Nighttime reflux tracking should include dinner timing, fluid volume, pillow elevation, alcohol, caffeine, and late snacks.

    What is the simplest hydration plan for reflux-prone days?

    The simplest plan is to drink plain water steadily from morning through early evening, use smaller sips with meals, and avoid testing multiple beverage changes at once. Keep carbonation, caffeine, citrus, alcohol, and peppermint stable while checking whether timing or volume matters. If nighttime symptoms are the problem, shift most fluids earlier and avoid pairing a large late drink with a large late meal. Hydration supports normal physiology, but reflux patterns still depend on meal size, posture, anatomy, medication context, and individual triggers. A one-week log can clarify whether fluids are helping, hurting, or simply unrelated. The most useful notes are time, drink type, drink volume, meal size, lying-down time, belching, heartburn, throat symptoms, stool pattern, and sleep quality. If the log shows no pattern, hydration probably belongs in the background habit category rather than the main reflux trigger category.