Category: Gut Health

  • Why Is My Lower Belly Bloated? Common Causes and Safer Clues

    Why Is My Lower Belly Bloated? Common Causes and Safer Clues

    Lower belly bloating usually comes from gas distribution, stool burden, slow transit, swallowed air, menstrual-cycle fluid shifts, food fermentation, or abdominal-wall tension. The location feels specific, but the cause is often a whole-digestion pattern. Persistent pain, vomiting, blood in stool, fever, unexplained weight loss, or pregnancy-related symptoms need clinician review.

    How did we evaluate lower belly bloating causes?

    We evaluated lower belly bloating by separating common digestive patterns from red-flag symptoms that need medical assessment. We prioritized gastroenterology reviews, government health references, and consensus-style clinical guidance over anecdotes because bloating has many overlapping causes. We treated lower-abdominal location as a clue, not a diagnosis, because gas, stool, pelvic organs, and abdominal muscles can all create pressure in the same region. We excluded cure claims, supplement-first framing, and single-cause explanations because most bloating patterns require context: meal timing, bowel frequency, menstrual cycle, medication use, stress, and symptom duration.

    Why does bloating show up in the lower belly?

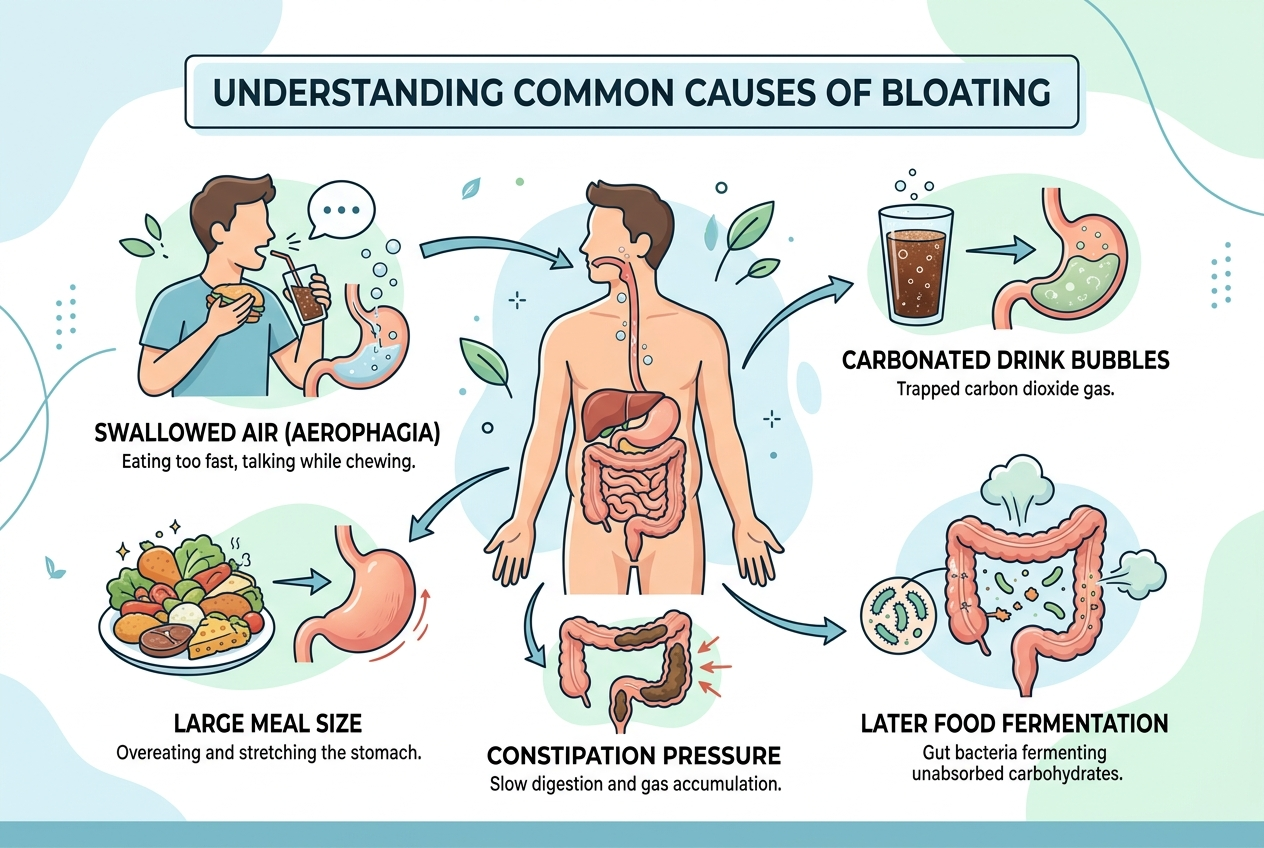
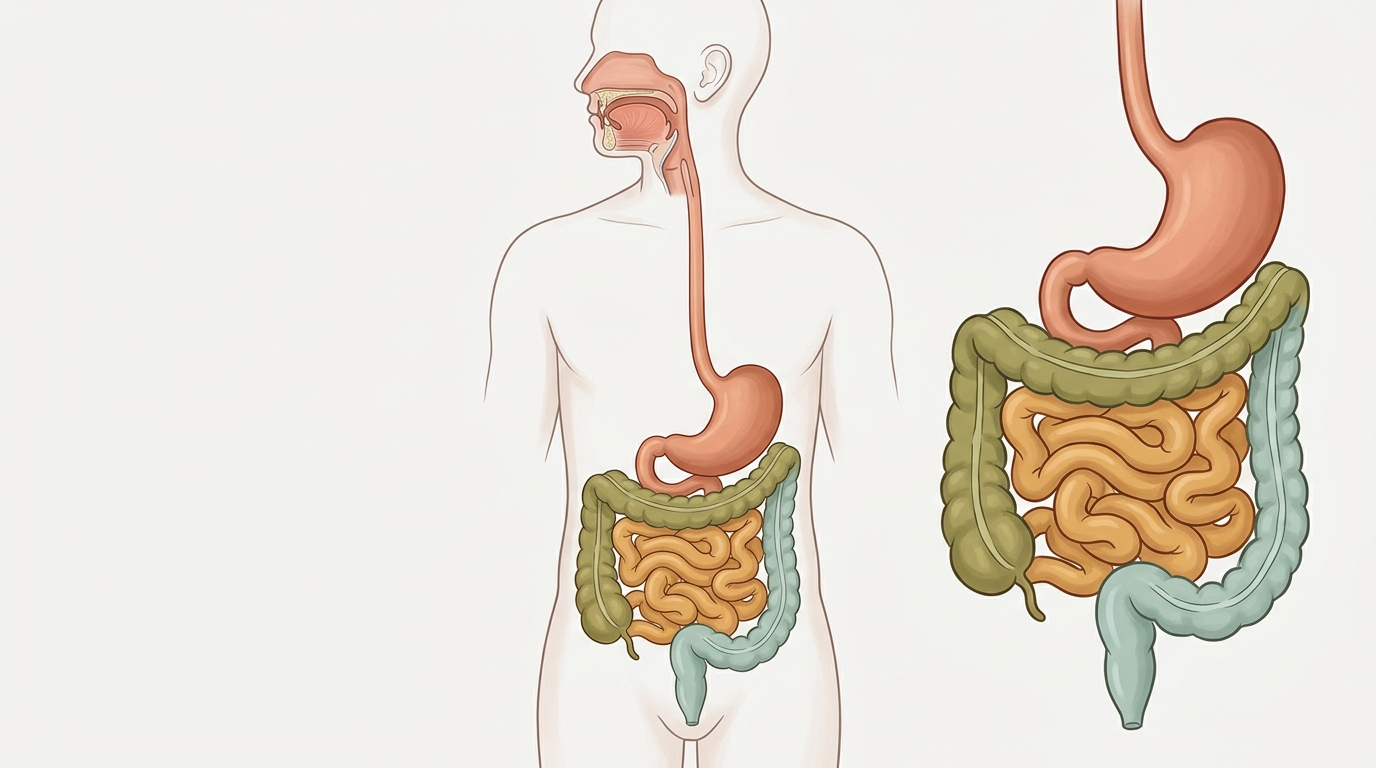
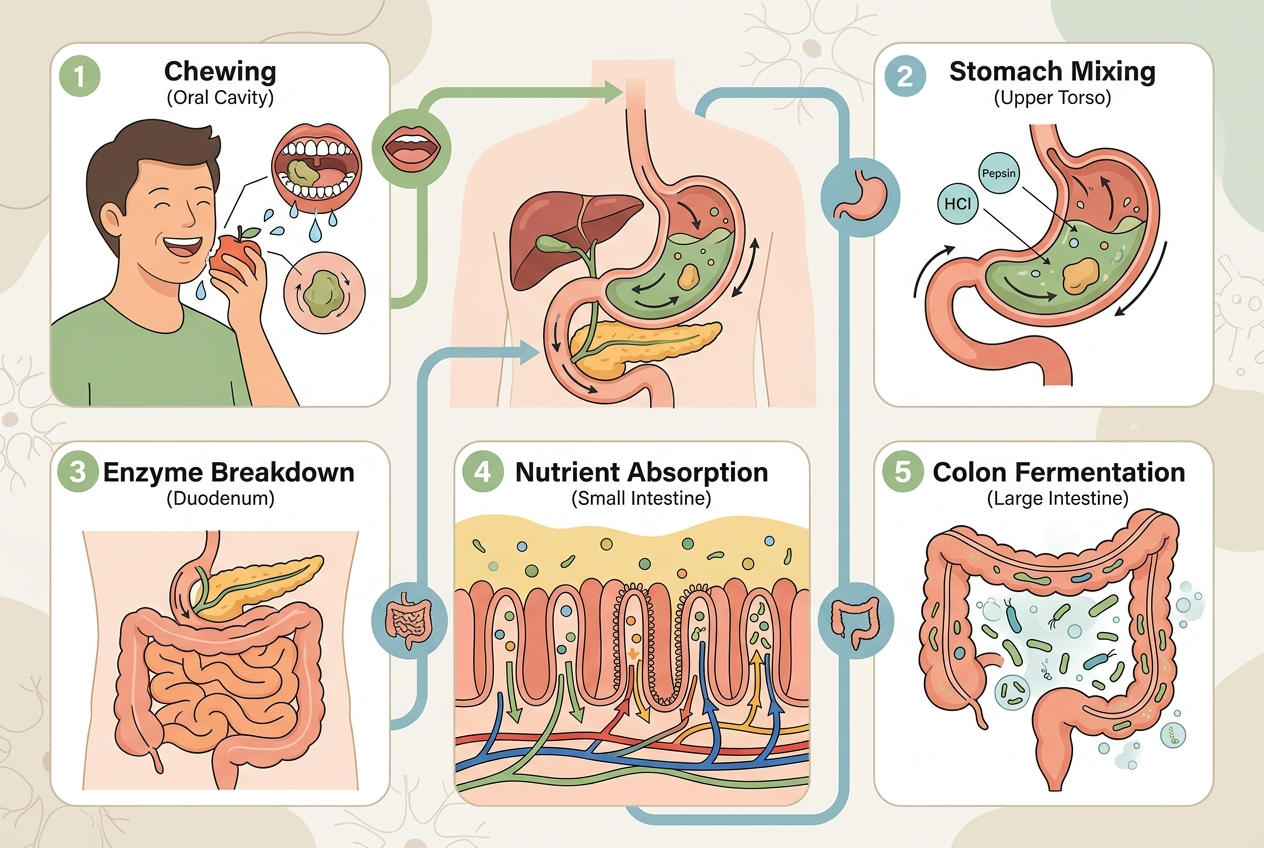
    Lower belly bloating often appears when the colon contains extra gas, stool, fluid, or distension. The lower abdomen includes the sigmoid colon, rectum, bladder, pelvic floor, and reproductive organs, so pressure in this area can come from digestion or non-digestive anatomy. Fermentable carbohydrates can reach the colon and become gas when colonic bacteria metabolize them. Constipation can make the lower abdomen feel firm because stool slows transit and stretches the bowel wall. Swallowed air can move through the intestines and collect as pressure hours after eating. The National Institute of Diabetes and Digestive and Kidney Diseases lists gas, constipation, and food intolerances among common causes of bloating and abdominal fullness. Location helps describe the sensation, but timing, stool pattern, meal triggers, and red flags identify the safer next step.

    • Most common digestive clues: gas, constipation, meal timing, and stool pattern.
    • Most important safety clue: new, severe, persistent, or worsening symptoms.
    • Best first record: food, bowel movement, cycle timing, and symptom duration.

    What digestive patterns commonly cause lower belly bloating?

    Constipation, high-fermentation meals, lactose malabsorption, fructose malabsorption, carbonated drinks, large fat-heavy meals, and irregular bowel timing commonly create lower abdominal bloating. Constipation matters because retained stool can trap gas and slow normal gas movement through the colon. A 2020 review in Gastroenterology and Hepatology describes bloating as a symptom influenced by visceral sensitivity, gas handling, gut motility, and diet. Fermentable oligosaccharides, disaccharides, monosaccharides, and polyols can increase gas in sensitive people, but tolerance differs by dose and food matrix. Lactose intolerance can create bloating, gas, and diarrhea when lactase activity does not match lactose intake. A lower-belly focus can also appear after rapid fiber increases because microbes ferment new substrates before bowel habits adapt.

    Could stress, posture, or breathing change belly shape?

    Stress, posture, and breathing can change how bloating feels and looks because the gut-brain axis, diaphragm, abdominal wall, and pelvic floor coordinate pressure. Some people experience visible distension when the diaphragm moves downward and the abdominal wall relaxes forward, even when measured intestinal gas is not dramatically higher. A clinical review in Clinical Gastroenterology and Hepatology describes abdominophrenic dyssynergia as one mechanism behind visible distension in functional bloating. Stress can also heighten visceral sensitivity, so a normal amount of gas feels larger or sharper. Slumped sitting can compress the abdomen and make post-meal fullness feel lower. This does not mean symptoms are imaginary; it means nerve sensitivity, muscle coordination, and digestion can amplify each other.

    When should lower belly bloating be checked by a clinician?

    Food and bowel habit tracking tools for identifying lower belly bloating patterns.
    Food and bowel habit tracking tools for identifying lower belly bloating patterns.

    Lower belly bloating should be checked urgently when it comes with severe or worsening pain, persistent vomiting, fever, black stool, blood in stool, fainting, chest pain, pregnancy concerns, inability to pass stool or gas, or rapid abdominal swelling. A non-urgent appointment is also reasonable when bloating is new after age 50, lasts more than a few weeks, follows unexplained weight loss, or disrupts eating and sleep. The Mayo Clinic advises medical evaluation for persistent bloating with concerning symptoms such as weight loss, diarrhea, vomiting, fever, or blood in stool. Menstrual-cycle bloating can be common, but pelvic pain, abnormal bleeding, or a sudden change from baseline deserves professional review. A symptom diary helps a clinician see whether the pattern points toward constipation, food intolerance, medication effects, pelvic conditions, or another cause.

    What can you track before changing your diet?

    Track timing, location, stool pattern, meal composition, carbonated drinks, gum chewing, menstrual-cycle day, medication changes, stress level, sleep, and whether passing gas or stool improves pressure. The Bristol Stool Form Scale can describe stool consistency more clearly than labels like normal or weird. Record serving sizes because bloating often reflects dose, not a food being universally bad. A low-FODMAP trial may help some people with IBS, but it works best as a structured elimination and reintroduction plan rather than permanent restriction. The American College of Gastroenterology’s IBS guideline discusses limited, supervised low-FODMAP use for global IBS symptoms. Tracking first prevents random food removal, which can reduce fiber diversity and make constipation worse. A useful diary covers three to seven days before major changes.

    What gentle steps are reasonable for common bloating?

    Gentle first steps include walking after meals, eating more slowly, reducing carbonated drinks, checking constipation, spacing large meals, and increasing fiber gradually instead of suddenly. Water, regular meals, and consistent bathroom timing can support stool movement when constipation is part of the pattern. Peppermint oil, simethicone, lactase, or targeted dietary trials may fit some situations, but they should match the suspected cause rather than being stacked randomly. People with reflux, pregnancy, gallbladder disease, medication interactions, or chronic conditions should ask a clinician before using concentrated oils or new supplements. The safest approach tests one variable at a time for one to two weeks. If bloating improves after stool regularity improves, constipation was likely a major driver.

    For a detailed comparison of specific products and strains, see Why Do Probiotics Make Me Hungry? Bloating Causes and Alternatives.

    What do people often misunderstand about lower belly bloating?

    People often assume lower belly bloating means fat gain, one bad food, or one missing supplement. Fat gain changes gradually, while bloating can change within hours after meals, bowel movements, gas movement, or cycle shifts. A food can be nutritious and still cause symptoms at a certain dose, especially beans, onions, wheat, apples, dairy, sugar alcohols, cruciferous vegetables, and large raw salads. Another mistake is cutting every fermentable food at once, which makes it difficult to identify the true trigger. Bloating can also coexist with normal digestion, especially after a large meal. The more useful question is whether the pattern is new, severe, persistent, linked to constipation, linked to a specific food dose, or paired with red flags.

    Is lower belly bloating usually gas?

    Lower belly bloating is often related to gas, but gas is not the only cause. Stool burden, fluid shifts, pelvic-floor tension, menstrual-cycle changes, and abdominal-wall coordination can create a similar pressure sensation.

    Can constipation cause lower abdominal bloating?

    Constipation can cause lower abdominal bloating because stool slows transit and can trap gas in the colon. Infrequent bowel movements, hard stool, straining, or incomplete evacuation make constipation more likely.

    Can bloating happen without visible swelling?

    Bloating can happen without visible swelling because the symptom is a sensation of pressure or fullness. Distension describes a visible or measurable increase in abdominal size, and the two can overlap without being identical.

    Can periods cause lower belly bloating?

    Menstrual-cycle hormone shifts can change fluid balance, bowel motility, and pelvic sensitivity. New severe pelvic pain, abnormal bleeding, or symptoms that are very different from baseline should be discussed with a clinician.

    Should you cut out all high-FODMAP foods?

    Do not cut out all high-FODMAP foods indefinitely without a plan. A structured low-FODMAP trial uses short elimination, careful reintroduction, and personalization so the diet does not become unnecessarily restrictive.

    Can drinking water fix bloating?

    Water can help when constipation or dehydration contributes to bloating, but water does not neutralize every cause. Meal size, carbonated drinks, fiber dose, stool pattern, and food intolerance may matter more.

    When is bloating not normal?

    Bloating is not normal when it is severe, worsening, persistent, or paired with vomiting, fever, blood in stool, black stool, unexplained weight loss, fainting, or inability to pass stool or gas. Those symptoms deserve medical attention.

    Sources:

  • Which Vegetables Build Gut Microbiome Diversity Best?

    Which Vegetables Build Gut Microbiome Diversity Best?

    Eating a wider variety of vegetables can support gut microbiome diversity because different plant fibers, resistant starches, and polyphenols feed different microbial groups. A practical target is not one magic vegetable; it is a rotating mix of leafy greens, cruciferous vegetables, legumes, alliums, roots, mushrooms, and colorful plant foods across the week.

    How did we evaluate vegetables for microbiome diversity?

    We evaluated vegetables by looking at fermentable fiber type, polyphenol content, resistant starch potential, culinary repeatability, and evidence from human microbiome research. We prioritized population studies, clinical nutrition reviews, and consensus definitions for prebiotic substrates over single-food claims. The strongest evidence supports overall plant variety and fiber adequacy, while evidence for one vegetable outperforming every other vegetable is weaker. We also considered grocery accessibility, preparation flexibility, and serving-size tolerance because a vegetable only helps if someone can eat it repeatedly. We excluded disease-treatment claims and ranked vegetables as daily dietary tools that can support microbial variety within a broader pattern of meals, sleep, movement, and tolerance. This method favors rotation, category coverage, gradual change, and ordinary grocery-store foods over dramatic short-term protocols, unsupported superfood rankings, or overly narrow food lists.

    Which vegetables build microbiome diversity best?

    The best vegetables for microbiome diversity are the ones that supply different substrates to different gut microbes. Leafy greens such as spinach, kale, arugula, and romaine provide insoluble fiber, magnesium, folate, and plant nitrates. Cruciferous vegetables such as broccoli, cabbage, cauliflower, and Brussels sprouts provide glucosinolates, soluble fiber, and sulfur-containing compounds. Alliums such as onion, garlic, leek, and scallion provide fructans that Bifidobacterium and other saccharolytic bacteria can ferment. Legumes such as lentils, chickpeas, black beans, and split peas provide resistant starch, galactooligosaccharides, and protein-bound fiber. The American Gut Project reported that people eating more than 30 plant types per week had greater microbiome diversity than people eating 10 or fewer, according to a 2018 mSystems paper indexed by PubMed. Meaningful variety matters because the microbiome responds to substrate range, not just vegetable volume.

    • Best weekly target: 20 to 30 different plant foods.
    • Best daily base: greens, alliums, legumes, and colorful vegetables.
    • Best tolerance strategy: increase fiber gradually.

    What vegetable list gives the widest range of gut substrates?

    A useful microbiome-diversity list includes leafy greens, crucifers, alliums, legumes, roots, mushrooms, sea vegetables, and colorful fruiting vegetables. Spinach, kale, and chard supply leafy-green fiber and micronutrients. Broccoli, cabbage, bok choy, radish, and Brussels sprouts supply cruciferous compounds and roughage. Onion, garlic, leek, asparagus, and artichoke supply fructans, inulin-type fibers, and other fermentable carbohydrates. Lentils, chickpeas, peas, and black beans supply resistant starch and galactooligosaccharides. Sweet potato, cooled potato, carrot, beet, and parsnip supply root vegetable fibers and, when cooked then cooled, more resistant starch. Mushrooms supply beta-glucans and chitin-like fibers. Red pepper, eggplant, tomato, purple cabbage, and herbs add polyphenols. The International Scientific Association for Probiotics and Prebiotics defines a prebiotic as a substrate selectively used by host microorganisms for a health benefit in a 2017 consensus statement, so the best list emphasizes substrate diversity.

    How many vegetables do you need each week?

    A realistic target is 15 to 30 different plant foods per week, with vegetables making up the largest share. The 30-plant benchmark comes from observational microbiome data, not a universal clinical prescription, so it should be treated as a practical variety target rather than a medical rule. Someone who eats five vegetables per week can start by adding two new categories: one allium and one legume. Someone already eating 15 plant foods can improve range by rotating colors, fiber types, and preparation methods. The Dietary Guidelines for Americans recommend adults eat vegetables from dark-green, red-orange, legume, starchy, and other vegetable subgroups across the week, and that subgroup framework is useful for microbiome variety. A rotation beats a single “superfood” because gut microbes receive a broader set of fermentable carbohydrates, phenolic compounds, and mineral cofactors.

    Which vegetables are best for beginners with sensitive digestion?

    Seven vegetable categories that provide different fibers and polyphenols for gut microbes
    Seven vegetable categories that provide different fibers and polyphenols for gut microbes

    Beginners with sensitive digestion often do better with cooked, peeled, smaller servings before raw, large, high-FODMAP servings. Carrots, zucchini, peeled cucumber, spinach, lettuce, potato, sweet potato, and squash tend to be easier starting points for many people because cooking softens fiber structure. Lentils, chickpeas, onion, garlic, artichoke, asparagus, and large broccoli servings can be more fermentable, so they may cause gas when the dose rises quickly. This does not make those vegetables bad; it means fermentation speed can exceed tolerance. A careful approach starts with one new vegetable, one half-cup serving, and three to four repeat exposures before adding another variable. A 2020 review in Nutrients describes dietary fiber as a microbiota-accessible carbohydrate category with effects that depend on fiber structure, dose, and host context, so tolerance should guide speed. Symptom tracking should record serving size, preparation, timing, stool pattern, and gas instead of blaming an entire vegetable category.

    What cooking methods preserve microbiome value?

    Cooking methods change texture, water content, resistant starch, and polyphenol availability, but they do not erase microbiome value. Steaming broccoli, sauteing greens, roasting carrots, pressure-cooking beans, and simmering lentils can make fiber easier to chew and tolerate. Cooking and cooling potatoes, rice, or some root vegetables can increase resistant starch, which reaches the colon and becomes a fermentation substrate for short-chain-fatty-acid-producing bacteria. Fermentation adds another layer: sauerkraut, kimchi, and lacto-fermented vegetables can supply organic acids and live microbes when products remain unpasteurized, though microbial counts vary by process and storage. Blending vegetables into soup can improve consistency because soup supports larger portions without requiring a raw salad every day. The most useful rule is practical: choose preparation methods that help you repeat the vegetable. A perfectly raw crucifer serving that causes discomfort is less valuable than a smaller cooked serving that fits the week.

    What do people get wrong about vegetables and the microbiome?

    The biggest mistake is reducing microbiome diversity to one food. No single vegetable feeds every useful microbial group, and no food can guarantee a specific microbiome result. The second mistake is chasing raw volume without tolerance; a sudden jump from low fiber to high fiber can increase bloating, gas, and stool changes. The third mistake is ignoring legumes, herbs, mushrooms, and alliums because they do not look like typical salad vegetables. These foods expand substrate diversity and help a weekly plant count rise naturally. The fourth mistake is judging a vegetable only by calories. Microbes interact with fiber structure, resistant starch, polyphenols, sulfur compounds, and food matrix. The fifth mistake is removing vegetables after one uncomfortable meal without checking portion size, cooking method, or total daily fiber. The most durable approach uses a rotating grocery list, small repeatable portions, and symptom-aware pacing rather than a one-week overload.

    For a detailed comparison of specific products and strains, see Best Options for Rebuilding Your Gut Microbiome: Probiotics, Prebiotics, and Routines Compared.

    For a detailed comparison of specific products and strains, see Gut Microbiome Test: Ombre, Viome, Thorne, and No-Test Routines Compared.

    What is a simple weekly vegetable plan?

    A simple weekly plan uses seven categories: greens, crucifers, alliums, legumes, roots, mushrooms, and colorful vegetables. Monday can use spinach, onion, lentils, and carrots. Tuesday can use romaine, cabbage, chickpeas, and red pepper. Wednesday can use kale, garlic, sweet potato, and mushrooms. Thursday can use arugula, broccoli, black beans, and tomato. Friday can use chard, leek, peas, and beet. Saturday can use bok choy, radish, cooled potato, and herbs. Sunday can use lettuce, cauliflower, asparagus, and eggplant. This pattern creates 25 or more plant exposures without requiring exotic ingredients. The plan works because it distributes fermentable carbohydrates, insoluble fiber, resistant starch, and polyphenols across meals. People with IBS, inflammatory bowel disease, severe constipation, or food-triggered symptoms should personalize the list with a registered dietitian or clinician.

    Do vegetables increase gut microbiome diversity?

    Vegetables can support gut microbiome diversity when they increase overall plant variety, fiber intake, and polyphenol exposure. The strongest practical evidence points to diverse plant intake across the week rather than one specific vegetable.

    What is the best vegetable for gut bacteria?

    There is no single best vegetable for all gut bacteria. Garlic, onion, asparagus, artichoke, legumes, leafy greens, broccoli, and mushrooms each supply different substrates, so a rotating mix is more useful than a single winner.

    Are raw vegetables better than cooked vegetables?

    Raw vegetables are not automatically better than cooked vegetables. Cooking can reduce some heat-sensitive compounds, but it can also improve tolerance, soften fibers, and make a vegetable easier to eat consistently.

    Do legumes count as vegetables for gut diversity?

    Legumes count as plant foods and they are especially useful for microbiome diversity. Lentils, chickpeas, black beans, and peas provide resistant starch, galactooligosaccharides, and fermentable fibers.

    How fast should you add more vegetables?

    Add vegetables gradually if your baseline fiber intake is low. One new vegetable or one extra half-cup serving every few days gives gut microbes and bowel habits time to adapt.

    Can vegetables cause bloating?

    Vegetables can cause bloating when fermentable carbohydrates increase faster than tolerance. Onion, garlic, beans, broccoli, and asparagus are nutritious, but they may need smaller servings or cooked preparation for sensitive digestion.

    What is the easiest way to reach 30 plant foods?

    The easiest way is to count herbs, legumes, seeds, whole grains, mushrooms, fruits, and vegetables together. A soup, salad, grain bowl, or stir-fry can add six to ten plant exposures in one meal.

    Sources:

  • What Is the Estrobolome, and Why Does It Matter in Your 40s?

    What Is the Estrobolome, and Why Does It Matter in Your 40s?

    The estrobolome is the gut-microbial gene network that helps process estrogens after the liver packages them for elimination. It matters most in midlife because estrogen levels, gut transit, fiber intake, bile flow, and microbial beta-glucuronidase activity can shift during perimenopause and menopause.

    How did we evaluate the estrobolome?

    We evaluated the estrobolome by prioritizing peer-reviewed reviews on gut microbial beta-glucuronidase, estrogen recirculation, menopause-related microbiome shifts, and dietary-fiber fermentation. We weighted human observational data and mechanistic reviews above social-media hormone claims, because estrobolome science is still developing. We excluded claims that promise hormone balancing, detoxification, disease prevention, or cycle correction from a single food, probiotic, or cleanse. The strongest evidence supports a bidirectional relationship between gut microbes and estrogen metabolism; the weaker evidence involves predicting individual symptoms from one microbiome marker. This article uses cautious language because beta-glucuronidase activity, stool patterns, bile acids, body composition, medications, and menopause stage interact. The goal is to explain the mechanism, not diagnose hormone problems from digestive symptoms. We also separated routine digestive support from medical care because midlife symptoms can have several causes.

    What is the estrobolome and how does it work?

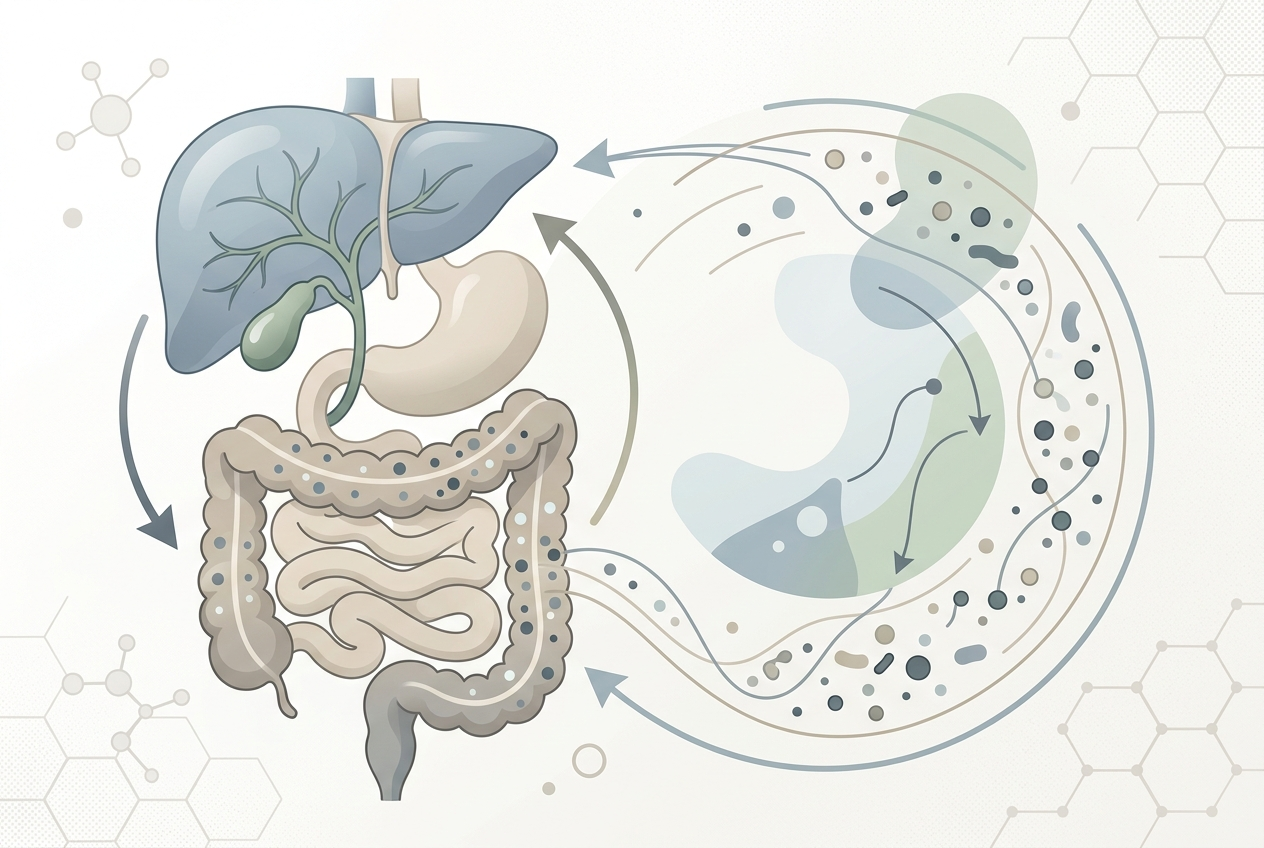
    The estrobolome describes gut microbial genes that influence estrogen metabolism, especially genes that encode beta-glucuronidase enzymes. The liver conjugates estrogens through glucuronidation, then bile carries those conjugated estrogens into the intestine. Some gut bacteria produce beta-glucuronidase, which can deconjugate estrogen metabolites and make them available for reabsorption through enterohepatic circulation. A 2023 review in Gut Microbes describes microbial beta-glucuronidase as a regulator of female estrogen metabolism, but the authors also emphasize complex host-microbe interactions rather than a single on-off switch. The practical interpretation is that gut microbes can affect estrogen handling, while estrogen levels can also affect gut microbial ecology. The estrobolome is therefore a feedback system. It includes microbial enzymes, bile movement, stool transit, fiber fermentation, and liver processing, not just one probiotic strain or one hormone pathway. Diet and medications can shift several of those inputs.

    Why might the estrobolome matter more for women in their 40s?

    The estrobolome may matter more in the 40s because perimenopause changes estrogen rhythm before menopause fully lowers ovarian estrogen production. Hormonal fluctuation can coincide with slower gut transit, sleep disruption, stress changes, altered eating patterns, and body-composition shifts, all of which can influence the microbiome. A 2025 review on diet, the gut microbiome, and estrogen physiology describes perimenopause as a window where microbial metabolism and dietary factors may interact with health span. That does not mean bloating proves hormone imbalance or that microbiome testing can explain every symptom. It means midlife is a reasonable time to support fundamentals that affect both digestion and microbial metabolism. Regular bowel movements help eliminate conjugated metabolites. Fiber intake supplies substrates for short-chain fatty acid production. Resistance training, adequate protein, sleep consistency, and medical follow-up provide context that a stool-test dashboard cannot replace.

    What daily habits support estrogen metabolism through the gut?

    Abstract diagram of liver, intestine, bile flow, and gut microbes involved in estrogen metabolism.
    Abstract diagram of liver, intestine, bile flow, and gut microbes involved in estrogen metabolism.

    Daily habits support estrogen metabolism through the gut by improving stool regularity, microbial diversity, and bile-acid movement. Dietary fiber is the most practical lever because gut bacteria ferment fibers into short-chain fatty acids such as acetate, propionate, and butyrate. A 2022 systematic review in Nutrients found that dietary fibers can affect short-chain fatty acids and gut microbiota composition in healthy adults, although responses vary by fiber type and person. Cruciferous vegetables, legumes, oats, berries, ground flaxseed, chia, and resistant starch provide different fermentable substrates. Hydration and walking support motility, which matters because prolonged constipation can change contact time between intestinal contents and microbial enzymes. Alcohol moderation matters because liver metabolism and gut permeability interact with hormone processing. The strongest routine is boring but measurable: fiber target, bowel pattern, sleep, movement, and medication review, repeated for weeks rather than days.

    What do people get wrong about the estrobolome?

    People often get the estrobolome wrong by turning a real mechanism into a one-step hormone hack. Beta-glucuronidase is not automatically bad; microbial beta-glucuronidase enzymes participate in normal metabolism, and different bacterial enzymes behave differently. Another mistake is assuming more probiotics always means better estrogen clearance. The research does not support choosing a random probiotic solely to “fix” estrogen recirculation. A third mistake is using detox language when the actual physiology involves liver conjugation, bile flow, microbial enzymes, stool transit, and reabsorption. A fourth mistake is ignoring red flags such as abnormal bleeding, severe pelvic pain, unexplained weight loss, black stools, or persistent diarrhea. Those signs require medical evaluation, not microbiome optimization. The useful question is narrower: which daily inputs make bowel regularity and microbial fermentation more stable, and which symptoms need clinical attention?

    Should you test your microbiome for estrobolome activity?

    Microbiome testing can be interesting, but most commercial stool tests cannot yet translate estrobolome markers into a reliable personal hormone plan. Some research assays measure microbial beta-glucuronidase genes, microbial taxa, metabolites, or inferred enzyme activity, but clinical interpretation remains limited. A PubMed-indexed review on the estrogen-gut microbiome axis describes physiological and clinical implications, yet review-level evidence does not equal a validated consumer diagnostic tool. If someone has heavy bleeding, irregular cycles, hot flashes, pelvic pain, or new digestive symptoms, standard medical evaluation should come first. A stool test may provide discussion material, but it should not override symptoms, medication history, colon-cancer screening age, thyroid status, iron status, or gynecologic assessment. For most people, tracking fiber intake, bowel frequency, alcohol, sleep, and symptom timing gives more actionable information than a single microbiome snapshot, especially during fluctuating perimenopause.

    What questions do people ask about the estrobolome?

    People ask whether the estrobolome controls estrogen, whether gut health affects perimenopause, whether constipation changes hormone symptoms, and whether specific foods can improve estrogen metabolism. The best short answer is balanced: the gut microbiome participates in estrogen recirculation, but it does not independently control hormones. Gut-supportive habits may improve the background system that processes metabolites, especially when bowel regularity and fiber intake are inconsistent. Individual symptoms still need context from age, cycle pattern, medications, stress, sleep, thyroid status, and gynecologic history. A practical plan starts with food diversity, bowel regularity, alcohol moderation, and medical care for red flags. Strong claims about detoxing estrogen or reversing menopause exceed the evidence. The useful middle ground is tracking digestive patterns while treating hormone symptoms as medical context, not internet guesswork.

    Is the estrobolome a real scientific term?

    Yes, researchers use estrobolome to describe gut microbial genes involved in estrogen metabolism. The term is real, but consumer claims often oversimplify what the science can predict.

    Can constipation affect estrogen recirculation?

    Constipation can increase intestinal transit time, which may influence microbial metabolism and reabsorption conditions. It should be treated as one factor, not as proof of excess estrogen.

    Do probiotics balance estrogen?

    No specific over-the-counter probiotic has been proven to balance estrogen in the broad way marketing claims imply. Probiotic effects are strain-specific, dose-specific, and outcome-specific.

    Which foods support the estrobolome?

    Fiber-rich plant foods are the best-supported starting point. Legumes, oats, berries, flaxseed, chia, vegetables, and resistant starch feed microbial fermentation in different ways.

    Does perimenopause change the gut microbiome?

    Research suggests menopause-related hormonal shifts can coincide with microbiome changes. The direction and size of those changes vary by diet, body composition, medications, and study design.

    Can a stool test diagnose hormone imbalance?

    A stool test cannot diagnose hormone imbalance by itself. Blood tests, symptom history, cycle history, medications, and clinician evaluation provide more reliable context.

    When should symptoms be checked medically?

    Abnormal bleeding, severe pelvic pain, black stools, persistent diarrhea, unintentional weight loss, or new symptoms after age 45 should be checked medically. Digestive and hormonal symptoms can overlap with conditions that need standard evaluation.

    Sources:

  • Why Do I Feel Bloated After a Bowel Movement?

    Why Do I Feel Bloated After a Bowel Movement?

    Mild stomach discomfort and bloating after a bowel movement can happen when stool movement, gas movement, rectal sensitivity, constipation, or pelvic-floor coordination changes how the gut feels after emptying. It is usually a pattern to track, not a diagnosis. Severe, new, persistent, or worsening symptoms need medical evaluation.

    How did we evaluate bloating after a bowel movement?

    We evaluated post-bowel-movement bloating by matching symptom timing to common digestive mechanisms: stool retention, gas transit, visceral sensitivity, pelvic-floor coordination, and bowel-habit changes. We prioritized NIDDK, MedlinePlus, NCBI Bookshelf, PubMed-indexed Rome IV discussions, and peer-reviewed reviews over anecdotal forum explanations, product-first claims, and social-media diagnosis language. We excluded product-first explanations because this question asks what the pattern may mean before anyone compares remedies, and we weighted tracking steps higher than one-size-fits-all advice. The main limitation is that symptom timing cannot identify one cause by itself; discomfort after a bowel movement can overlap with constipation, diarrhea, IBS-pattern symptoms, diet changes, medication effects, anxiety physiology, hemorrhoids, fissures, pelvic-floor tension, or unrelated abdominal problems. We also separated mild recurring patterns from red-flag patterns because those two groups need different next steps and different clinical urgency levels overall.

    Why can bloating happen after you poop?

    Bloating after a bowel movement can happen because the bowel movement changes pressure, gas position, and sensory signaling inside the colon and rectum. A person may empty some stool but still retain gas or stool higher in the colon. The rectum may also feel irritated after straining, urgency, diarrhea, or repeated wiping. In functional bowel disorders, normal stretch can feel stronger than expected because the gut-brain axis processes internal signals more intensely. A review in PMC describes visceral hypersensitivity as an important mechanism in irritable bowel syndrome, especially for pain and bloating perception (PMC). That does not mean every post-poop symptom is IBS. It means timing, stool form, straining, urgency, food pattern, bathroom duration, medication changes, and red flags matter more than one isolated episode. A single mild episode often tells less than a repeated pattern across similar meals and bowel movements.

    What does constipation have to do with after-poop bloating?

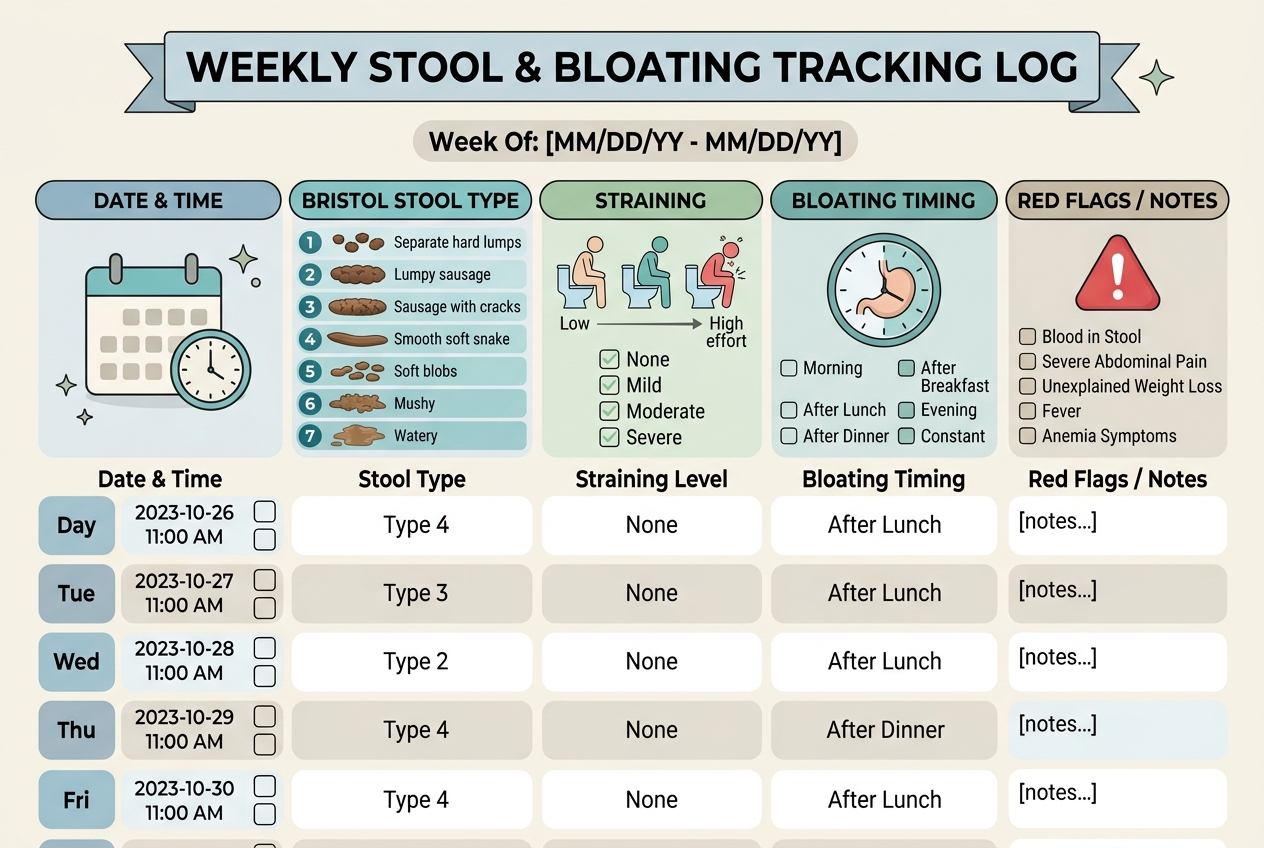
    Constipation can cause bloating after a bowel movement when stool remains in the colon or evacuation feels incomplete. MedlinePlus describes constipation as fewer than three bowel movements per week, hard or dry stool, or painful passage in many cases (MedlinePlus). NIDDK advises medical care when constipation persists despite self-care or appears with rectal bleeding, blood in stool, continual abdominal pain, or other concerning signs (NIDDK). A person can poop daily and still strain, pass small hard pieces, or feel unfinished. That pattern can leave gas trapped behind stool, make the abdomen feel distended, and create discomfort after the bathroom. Tracking Bristol stool type, straining, time on the toilet, urgency, and the sense of complete emptying gives more useful information than tracking frequency alone. The key question is not just “Did I go?” but “Was emptying easy and complete?”

    Could pelvic-floor coordination be involved?

    Pelvic-floor coordination can matter when the muscles that should relax during a bowel movement tighten, do not fully relax, or require straining to empty. NCBI Bookshelf notes that pelvic-floor dysfunction can involve incomplete evacuation, prolonged straining, or pressure during defecation (NCBI Bookshelf). This pattern can make someone feel bloated or uncomfortable after going because the rectum and lower bowel remain irritated or not fully emptied. Clues include long bathroom sessions, repeated trips, narrow stool, needing to change position, breath-holding, or feeling like more stool remains. This is not something to self-diagnose from one symptom. A clinician, gastroenterologist, or pelvic-floor physical therapist can evaluate coordination problems when the pattern is persistent, especially when ordinary fiber, water, walking, and routine changes do not help. The practical clue is effort: easy bowel movements usually point away from coordination trouble.

    How can you track the pattern before guessing?

    Digestive tracking log with Bristol stool type, straining, bloating timing, and red flag columns.
    Digestive tracking log with Bristol stool type, straining, bloating timing, and red flag columns.

    Track the pattern for one to two weeks with four data points: stool form, straining, timing of bloating, and food or drink triggers. The Bristol Stool Form Scale can help describe stool texture more precisely than “normal” or “weird.” Note whether bloating begins before the bowel movement, immediately after, or one to three hours later. Also note carbonated drinks, large meals, dairy, beans, onions, wheat, sugar alcohols, high-fat meals, caffeine, stress, new medications, and menstrual-cycle timing when relevant. Rome IV discussions define IBS around recurrent abdominal pain related to defecation and bowel-habit changes, but clinical interpretation belongs with a healthcare professional (Rome IV review). A log helps separate occasional gas movement from constipation, diarrhea, urgency, incomplete evacuation, or escalating symptoms. It also gives a clinician concrete details if the pattern continues beyond basic routine changes.

    When should after-poop bloating be checked?

    After-poop bloating should be checked promptly when it is severe, progressive, new after age 50, associated with fever, vomiting, blood, black stool, unexplained weight loss, anemia, persistent diarrhea, nighttime symptoms, or ongoing abdominal pain. It should also be checked when constipation does not improve with basic self-care or when bowel habits change suddenly and stay changed. These red flags do not prove a serious condition, but they move the question out of self-tracking territory. Mild discomfort that comes and goes with stool form, meal size, or straining can often be logged first. Persistent patterns deserve a clinician because stool retention, pelvic-floor dysfunction, IBS, medication effects, infections, inflammatory conditions, and structural problems can overlap. The goal is not alarm; the goal is not missing the pattern that needs care. New symptoms after antibiotics, surgery, travel, or major medication changes deserve extra caution.

    What questions do people ask about bloating after bowel movements?

    Is it normal to feel bloated after pooping?

    Occasional bloating after a bowel movement can happen, especially with gas, constipation, straining, or large meals. It is worth tracking when it repeats, worsens, or appears with pain or bowel-habit changes.

    Can incomplete emptying cause bloating?

    Yes, incomplete evacuation can leave stool or gas behind and create pressure after the bathroom. Clues include straining, multiple trips, hard stool, or feeling unfinished.

    Can IBS cause discomfort after bowel movements?

    IBS-pattern symptoms can include abdominal pain related to defecation and altered bowel habits. Only a clinician can interpret whether a recurring pattern fits IBS or another condition.

    Does diarrhea cause after-poop bloating?

    Diarrhea can irritate the rectum and change gas movement, so bloating or discomfort can appear afterward. Persistent diarrhea, dehydration, fever, blood, or nighttime symptoms should be checked.

    Should I take fiber for this pattern?

    Fiber may help constipation-leaning patterns, but sudden increases can worsen gas and bloating. Increase fiber gradually and track stool form, water intake, and symptoms.

    What should I write down for a doctor?

    Write down stool frequency, Bristol stool type, straining, pain location, bloating timing, blood, weight change, medications, supplements, and food patterns. A clear log is more useful than a vague “my digestion is off.”

    What is the practical next step?

    For mild recurring bloating after a bowel movement, track stool form, straining, timing, and incomplete-emptying sensations for one to two weeks. Improve basics first: steady fluids, regular bathroom time, gradual fiber, gentle walking, and less straining. Avoid changing several variables at once because that makes the pattern harder to interpret. If stool is hard, start with constipation basics. If stool is loose or urgent, track food timing, caffeine, stress, and recent illness. If emptying feels incomplete despite regular bowel movements, ask about pelvic-floor coordination rather than assuming the issue is only diet. Seek medical care sooner if symptoms are severe, new, persistent, worsening, or paired with red flags. A clear symptom log makes that visit faster and more useful because it shows timing, severity, and stool pattern instead of relying on memory alone later.

  • Fat or Bloating? How to Tell What Is Changing Your Belly Size

    Fat or Bloating? How to Tell What Is Changing Your Belly Size

    Sudden belly size changes are usually bloating, gas, stool, fluid, posture, or meal volume, while body fat changes more slowly over weeks. A 21-year-old man at 6’1″ and 195 lb can have either pattern, so track timing, waist change, bowel pattern, and red-flag symptoms before assuming fat gain.

    How we evaluated fat versus bloating?

    We evaluated this question by separating visible abdominal distension from longer-term body composition change, then checking which clues a reader can observe without pretending to diagnose themselves. NIDDK digestive references received priority for gas, constipation, and bloating mechanisms, while medical triage references shaped the red-flag section because symptom safety matters more than a mirror guess. We excluded supplement-first explanations because a cold-stage question needs anatomy, timing, stool pattern, meal context, hydration, posture, and symptom pattern before product categories or internet hacks enter the conversation. The main limitation is that a photo, body weight, and height cannot identify the cause of abdominal size without a clinical history, abdominal exam, timeline, medication review, repeated measurements, stool history, food pattern, and sometimes basic testing.

    What is the practical difference between belly fat and bloating?

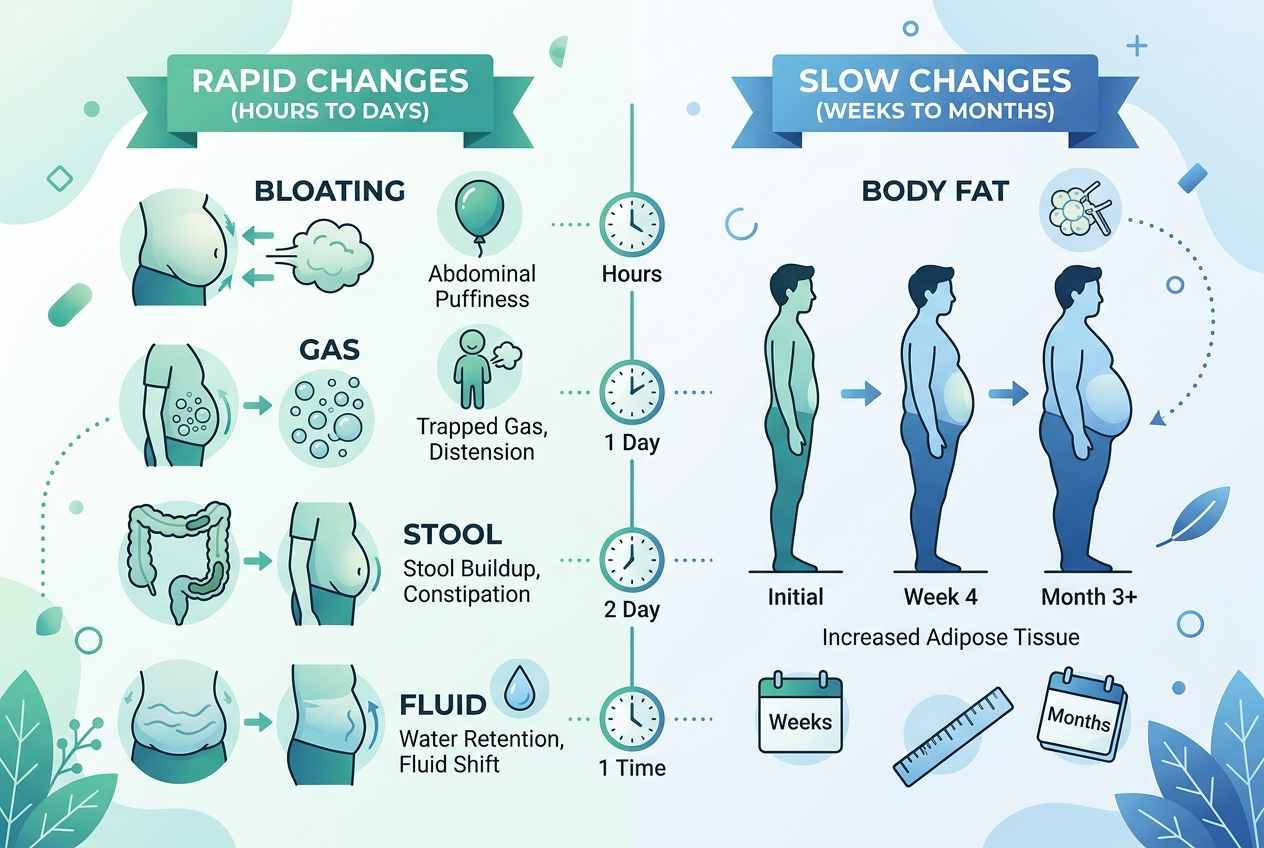
    Belly fat is stored adipose tissue, while bloating is a sensation of pressure, fullness, or visible distension in the abdomen. Body fat changes when energy intake, activity, sleep, alcohol, and training patterns create a sustained surplus over time. Bloating can change across one day because swallowed air, intestinal gas, meal volume, constipation, sodium, and fluid shifts change abdominal shape faster than fat tissue can. NIDDK lists belching, bloating, distension, and passing gas as common gas-related symptoms in its gas in the digestive tract guide. A useful home check compares morning waist, evening waist, bowel movement timing, and symptom triggers for seven days. If the abdomen is flatter in the morning and larger after meals, bloating is more likely. If waist circumference rises steadily across weeks, body fat or broader weight gain becomes more plausible.

    How can timing show whether the change is bloating?

    Timing is the strongest nonmedical clue because bloating follows meals, bowel rhythm, and gas movement more closely than fat gain. A stomach that feels normal on waking and tight after lunch often reflects meal volume, fermentable carbohydrate intake, swallowed air, constipation, or delayed gas transit. A stomach that looks similar every morning for several weeks may reflect fat gain, posture, muscle tone, fluid retention, or an underlying medical pattern. NIDDK explains that gut microbes in the large intestine help digest carbohydrates and can produce gas during that process. The most useful log records wake-up waist, bedtime waist, meals, carbonated drinks, gum, alcohol, stool form, and pain location. A seven-day pattern beats one mirror check. Fast day-to-day swings point toward bloating, stool, or fluid. Slow month-to-month changes point toward body composition, training, or energy balance.

    What warning signs mean this needs medical attention?

    Most bloating is not an emergency, but abdominal change deserves medical attention when it comes with persistent pain, vomiting, fever, black stool, blood in stool, unexplained weight loss, trouble swallowing, chest pressure, or a rigid abdomen. Mayo Clinic advises scheduling care when abdominal pain worries you or lasts more than a few days in its abdominal pain triage guide. New severe constipation, diarrhea, or rapid belly swelling also belongs in a clinician conversation. For a 21-year-old lifter or student, the practical threshold is change plus persistence. A one-day post-meal belly is usually a pattern to observe. A two-week change with pain, appetite loss, vomiting, bleeding, or unexplained scale movement is not a fitness puzzle. A clinician can check medications, hernia signs, bowel patterns, food intolerance clues, and basic labs when the history points beyond routine bloating.

    What does constipation have to do with looking bloated?

    Infographic comparing short-term bloating patterns with slower body fat changes over time.
    Infographic comparing short-term bloating patterns with slower body fat changes over time.

    Constipation can make the abdomen look and feel larger because stool retention slows transit and increases pressure in the colon. NIDDK describes constipation as a pattern that can include difficult, infrequent, hard, or incomplete bowel movements in its constipation resource. The pattern matters more than a single missed day. Straining, pellet-like stool, incomplete evacuation, low fluid intake, low fiber intake, travel, stress, opioid medications, and abrupt diet changes can all change abdominal comfort. A high-protein cutting diet can also reduce fiber if vegetables, oats, legumes, fruit, and whole grains disappear. Constipation-related distension often improves after a bowel movement, hydration, walking, and a steady fiber routine. However, sudden constipation with severe pain, vomiting, blood, or major weight change needs medical evaluation. Stool pattern belongs in the same log as waist timing and meals.

    How should someone track the pattern for one week?

    A one-week log should measure timing, not anxiety. Measure waist at the navel after waking, before bed, and during the worst bloating window. Record meals, fiber-heavy foods, dairy, carbonated drinks, alcohol, gum, large protein shakes, creatine loading, sodium-heavy meals, bowel movements, stool form, pain score, and training sessions. Use the same tape position and relaxed posture each time because flexing or slouching changes the result. The goal is a pattern such as “two-inch increase after carbonated drinks,” “distension improves after bowel movement,” or “waist is unchanged but posture changes after lifting.” A steady morning waist with large evening swings points toward bloating or meal volume. A rising morning waist across several weeks points toward weight gain or fluid. The log should end with a simple next step: adjust one variable, seek care for red flags, or continue monitoring.

    What questions do people ask about fat versus bloating?

    Can bloating make you look heavier than you are?

    Yes. Bloating can push the abdomen outward without adding body fat. The change can be most visible after large meals, carbonated drinks, constipation, or high-fermentation foods.

    Can body fat appear overnight?

    No. Body fat does not appear as a large abdominal change overnight. Fast changes are more often food volume, stool, gas, water, posture, or inflammation.

    Is BMI enough to answer this?

    No. BMI uses height and weight, so it cannot distinguish muscle, fat distribution, bloating, stool, or posture. Waist timing and symptom pattern add more useful information.

    Should I cut out every food that causes bloating?

    No. Removing too many foods at once makes the pattern harder to interpret. Test one variable at a time unless a clinician gives a specific medical diet.

    Can stress make bloating feel worse?

    Yes. Stress can change gut sensation, eating speed, breathing pattern, and bowel rhythm. The mechanism is not “all in your head”; the gut and nervous system communicate continuously.

    When should I stop self-tracking?

    Stop self-tracking and seek care if pain is severe, symptoms persist, bleeding appears, vomiting continues, or weight changes without explanation. Tracking is useful only when symptoms are mild and stable.

    What is the bottom line?

    Fat gain and bloating can both change the abdomen, but they move on different timelines. Bloating shifts across hours with meals, gas, stool, fluid, and posture. Fat gain usually shifts across weeks with sustained energy balance. A seven-day waist, meal, stool, and symptom log gives a better answer than a single mirror check. If the pattern includes severe pain, vomiting, blood, fever, unexplained weight loss, or persistent change, medical evaluation is the right next step. If the pattern is mild and meal-linked, start with slower eating, fewer carbonated drinks, consistent fiber, hydration, walking, and regular sleep before making dramatic diet changes. The practical answer is not “fat” or “bloating” from one photo; the answer is the timeline, the pattern, and whether red flags are present. Repeatable measurements beat one anxious snapshot overall.

  • What Is the Gut Microbiome, and Why Does It Matter?

    What Is the Gut Microbiome, and Why Does It Matter?

    The gut microbiome is the community of bacteria, archaea, fungi, viruses, and microbial genes living mostly in the large intestine. It helps ferment fiber, produce short-chain fatty acids, train immune signaling, and interact with digestion. A healthy microbiome is not one perfect profile; it is a resilient ecosystem that changes with diet, medication, sleep, stress, and age.

    How did we evaluate the gut microbiome?

    We evaluated the gut microbiome through large human mapping projects, peer-reviewed diet-and-fiber studies, and consensus terminology from microbiology organizations. Population studies received more weight than single-person microbiome tests because stool profiles vary by sampling method, database, and recent meals. We prioritized evidence on microbial diversity, fermentation, short-chain fatty acids, and body-site specificity, while excluding commercial claims that promise a single “ideal” score. The main limitation is that microbiome science describes patterns well but does not yet translate every stool-test result into a precise personal action plan.

    What is the gut microbiome in plain English?

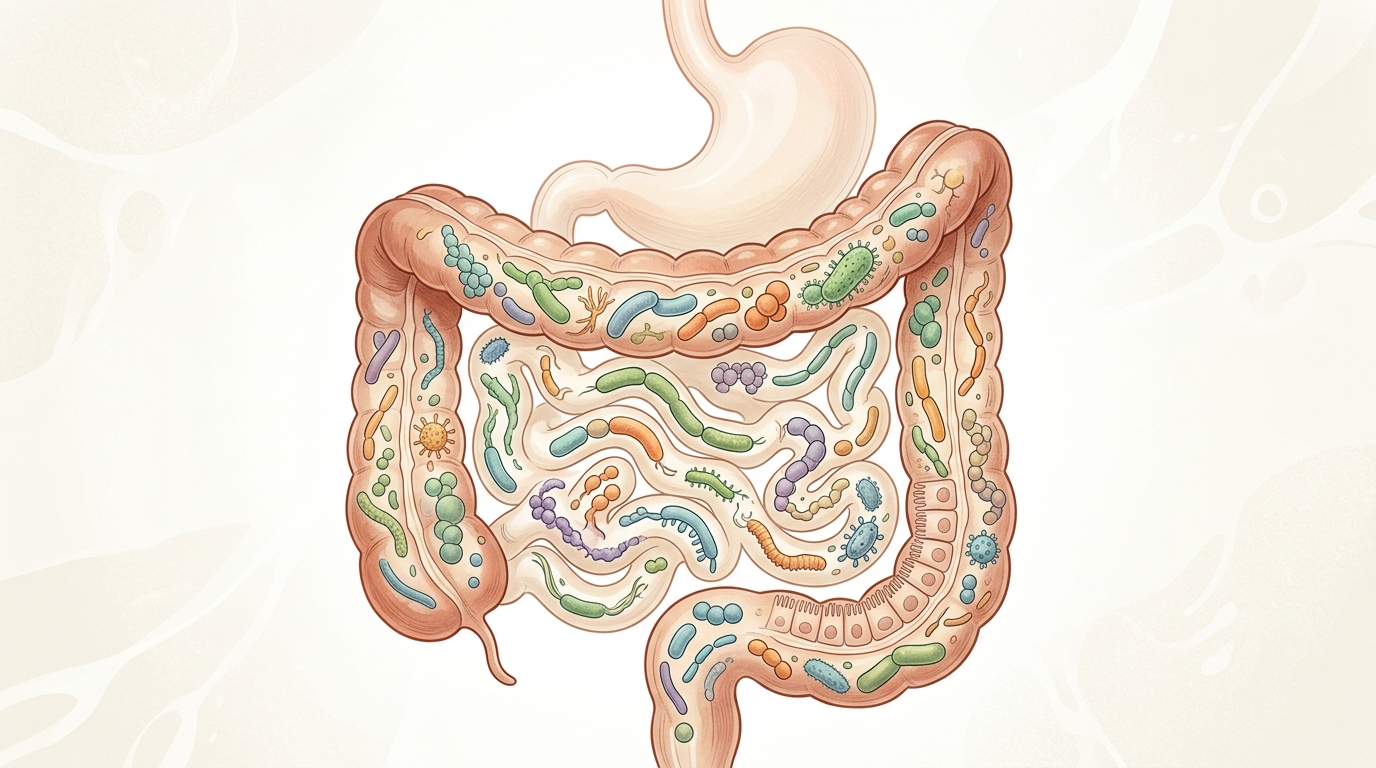
    The gut microbiome is a living ecosystem inside the digestive tract, especially the colon. Bacteria such as Bifidobacterium, Faecalibacterium, Roseburia, and Lactobacillus coexist with fungi, archaea, viruses, and microbial genes. The NIH Human Microbiome Project helped show that microbial communities differ across body sites, so the gut microbiome is not the same as the skin, mouth, or nasal microbiome. Gut microbes ferment nondigestible carbohydrates, release metabolites, interact with bile acids, and communicate with intestinal immune cells. The word “healthy” does not mean one universal species list. It usually means the community has functional resilience: it can process dietary fiber, recover after disruption, and maintain balanced interactions with the intestinal lining. Modern sequencing can identify microbial DNA, but DNA detection does not prove that a microbe is active, beneficial, or harmful in every person.

    • Core idea: the microbiome is an ecosystem, not a single organ
    • Key location: the large intestine
    • Practical lever: repeatable diet pattern

    How does food shape the gut microbiome?

    Food shapes the gut microbiome because microbes eat what human enzymes do not fully digest. Dietary fiber, resistant starch, polyphenols, and some prebiotic carbohydrates reach the colon and become substrates for fermentation. A 2022 systematic review in Nutrients evaluated 42 randomized controlled trials and found that different fibers can change short-chain fatty acid profiles and gut microbiota composition, though results vary by fiber type and person. Inulin, psyllium, beta-glucan, legumes, oats, vegetables, berries, and cooled starches can feed different microbial groups. High-consistency diets often create more measurable patterns than one-time “gut reset” meals. Ultra-low-fiber eating can reduce the amount of fermentable material available to beneficial fiber-associated microbes. The best-supported food strategy is not exotic; it is diverse plant intake repeated long enough for microbial metabolism to adapt.

    • Best studied input: dietary fiber
    • Important output: short-chain fatty acids
    • Biggest caveat: individual response varies

    What do short-chain fatty acids actually do?

    Short-chain fatty acids are microbial metabolites produced when gut bacteria ferment carbohydrates that humans cannot digest directly. Acetate, propionate, and butyrate are the main short-chain fatty acids discussed in human microbiome research. Butyrate serves as an energy source for colonocytes, while acetate and propionate participate in broader metabolic signaling. A review in Gut Microbes describes dietary fiber and prebiotics as substrates that gastrointestinal microbes can metabolize through fermentation. These compounds are one reason fiber quality matters: the same gram count from wheat bran, inulin, oats, beans, or resistant starch may produce different microbial effects. Short-chain fatty acids are not magic chemicals, and higher is not always better in every context. They are useful markers of microbial activity because they connect food choice, bacterial metabolism, intestinal transit, stool chemistry, and intestinal physiology in a measurable chain.

    Can a stool test tell you whether your microbiome is healthy?

    Fiber-rich foods linked to short-chain fatty acid production in the gut microbiome.
    Fiber-rich foods linked to short-chain fatty acid production in the gut microbiome.

    A stool test can describe part of the microbial DNA found in one sample, but it cannot fully define gut health by itself. The Integrative Human Microbiome Project in Nature showed that microbiome research uses multi-omic data, longitudinal sampling, and clinical context to interpret host-microbe patterns. Consumer stool tests usually provide a narrower one-time snapshot. A “low” or “high” organism score may reflect recent diet, antibiotics, bowel transit time, laboratory methods, or reference databases. Useful interpretation asks whether symptoms, food tolerance, medication history, and diet pattern line up with the report. Stool testing can be helpful for research and sometimes for clinician-guided care, but it should not turn every microbe into a villain. The microbiome is dynamic, so trend, context, repeat sampling, clinician interpretation, and repeatable habits matter more than a single dramatic chart.

    What habits support microbiome resilience?

    Microbiome resilience usually improves through repeatable, boring habits rather than extreme resets. A practical pattern includes 25-38 grams of daily fiber when tolerated, gradual fiber increases, regular meals, fermented foods that are clearly live-culture when tolerated, adequate sleep, and careful antibiotic use under medical guidance. Plant diversity matters because beans, oats, berries, greens, nuts, seeds, lentils, and resistant starches feed different microbial pathways. Hydration and movement support bowel regularity, which changes how long microbes interact with stool contents. Sudden high-dose fiber can increase gas, so gradual increases are smarter than aggressive overnight changes. Antibiotics, gastrointestinal infections, major diet shifts, and chronic stress can disrupt microbial patterns, but resilient ecosystems often recover with time and consistent inputs. The best microbiome routine is the one a person can repeat for weeks without triggering avoidable digestive discomfort.

    What questions do people ask about the gut microbiome?

    Is the gut microbiome the same as gut bacteria?

    Gut bacteria are part of the gut microbiome, but the microbiome also includes microbial genes, viruses, archaea, fungi, and their metabolites. Bacteria receive most attention because sequencing and fermentation research often focuses on bacterial taxa.

    How fast can the gut microbiome change?

    The gut microbiome can shift within days after diet or medication changes, but durable patterns usually require repeated inputs. A single high-fiber meal may change fermentation temporarily, while a consistent fiber pattern is more likely to shape community activity.

    Are probiotics the same as the microbiome?

    Probiotics are live microorganisms that meet a defined benefit standard when taken in adequate amounts, according to ISAPP consensus terminology. The microbiome is the broader resident ecosystem already living in and on the body.

    Does everyone need fermented foods?

    Not everyone tolerates fermented foods, and fermented foods are not identical to probiotics. Some fermented foods contain live microbes, while heat-treated or shelf-stable products may not contain meaningful live cultures.

    What hurts the gut microbiome most?

    Repeated low-fiber eating, unnecessary antibiotic exposure, major sleep disruption, and highly restrictive diets can reduce microbial inputs or resilience. The effect depends on baseline diet, medication history, and the individual microbial ecosystem.

    Can you permanently fix the microbiome?

    The microbiome is not a broken machine with a one-time permanent fix. It is an adaptive ecosystem that responds to food, medication, illness, stress, sleep, and aging across time.

    For a detailed comparison of specific products and strains, see Best Options for Rebuilding Your Gut Microbiome: Probiotics, Prebiotics, and Routines Compared.

    For a detailed comparison of specific products and strains, see What’s the Best Fiber Supplement for Gut Health? An Evidence-Based Comparison.

    For a detailed comparison of specific products and strains, see Best Supplements to Help Your Gut: Probiotics, Fiber, Enzymes, and Botanicals Compared.

    For a detailed comparison of specific products and strains, see Looking for a Reliable Gut Health Supplement? How to Compare Probiotics, Fiber, Enzymes, and DGL.

    For a detailed comparison of specific products and strains, see Gut Health Supplements That Made a Difference: Probiotics, Fiber, Enzymes, and Peppermint Compared.

    For a detailed comparison of specific products and strains, see Gut Health Supplements That Actually Make a Difference: Probiotics, Fiber, and Enzymes Compared.

    What is the simplest takeaway about the microbiome?

    The gut microbiome is best understood as a responsive ecosystem. It changes when food inputs, bowel transit, medication exposure, sleep timing, stress load, and daily routines change. The most evidence-aligned first step is a gradual, tolerable increase in plant diversity and fiber, not a dramatic cleanse or a single stool-test score. Start with repeatable meals that include oats, beans, lentils, vegetables, berries, nuts, seeds, or resistant starch, then adjust based on comfort and bowel regularity. People with severe symptoms, blood in stool, unexplained weight loss, persistent diarrhea, or ongoing pain should seek medical evaluation because microbiome habits cannot replace diagnosis. For most healthy adults, the realistic goal is resilience, not a perfect microbiome report. That means supporting regular microbial inputs, avoiding unnecessary disruption, and watching how digestion responds over time instead of chasing every new trend.

  • Why Can Lactose-Free Milk Still Cause Bloating, Nausea, or Reflux?

    Why Can Lactose-Free Milk Still Cause Bloating, Nausea, or Reflux?

    Lactose-free milk can still cause digestive symptoms because it removes or breaks down lactose, but it does not remove milk proteins, fat, additives, serving size effects, or reflux triggers. If lactose-free milk still causes bloating, nausea, diarrhea, or reflux, the pattern may involve something besides lactose alone.

    How did we evaluate why lactose-free milk can still cause symptoms?

    We evaluated lactose-free milk symptoms by separating lactose malabsorption, milk protein reactions, fat tolerance, reflux mechanics, serving size, and food-additive tolerance. NIDDK and MedlinePlus references received more weight than anecdotal reports because they define lactose intolerance, symptom timing, and differences from milk allergy. We excluded claims that assume one home reaction proves one cause, because digestive symptom patterns overlap. We also prioritized practical tracking steps over supplement or product recommendations because this is a cold educational question. Repeated timing, portion size, and symptom type received more weight than one isolated episode. We treated brand switches, fat changes, coffee use, and bedtime drinking as confounders because each can change the result. The main limitation is that a home food log can identify patterns, but it cannot confirm allergy, malabsorption, reflux, IBS, or another digestive condition by itself.

    Why can lactose-free milk still bother your stomach?

    Lactose-free milk changes lactose, not the entire milk matrix. Lactase-treated milk breaks lactose into glucose and galactose, but the drink still contains dairy proteins, fat, minerals, and the same liquid volume. NIDDK explains that lactose intolerance symptoms occur when undigested lactose reaches the colon and bacteria create gas and fluid, causing bloating, diarrhea, gas, nausea, abdominal pain, and rumbling within a few hours through its lactose intolerance overview. If lactose-free milk causes the same symptoms, the issue may be residual lactose sensitivity, milk protein sensitivity, high serving volume, high-fat dairy, reflux overlap, sweetener tolerance, or an unrelated flare. Coffee, cereal, protein powder, and bedtime timing can also confuse the pattern. The clue is repeatability: the same amount, same brand, same timing, and same symptom window tell more than one bad glass.

    How is lactose intolerance different from milk allergy or reflux?

    Lactose intolerance involves difficulty digesting lactose, while milk allergy involves the immune system reacting to milk proteins. NIDDK states that lactose intolerance and milk allergy have different causes, and a serious milk allergy reaction can be life threatening. Reflux is a separate pattern in which stomach contents move upward, often shaped by meal volume, fat content, timing, and body position. That means one person can react to regular milk from lactose, another can react to lactose-free milk from dairy protein, and another can feel reflux after any large evening drink. Symptom type helps sorting. Lower-abdominal gas, rumbling, diarrhea, and cramps after dairy fit lactose malabsorption more closely. Burning, regurgitation, throat irritation, or symptoms after lying down fit reflux mechanics more closely. Skin, breathing, mouth, or throat symptoms point away from simple lactose intolerance. Hives, swelling, wheezing, or rapid systemic symptoms need urgent medical attention.

    What should you track before assuming lactose-free milk is the problem?

    Track the brand, serving size, fat level, temperature, timing, added ingredients, and what else was eaten within four hours. A small lactose-free milk serving with a meal is a different test than a large cold glass before bed. NIDDK notes that clinicians may use medical history, family history, diet history, and tests when diagnosing lactose intolerance through its diagnosis guidance. A useful home log records symptom onset, symptom type, severity, bowel changes, reflux sensations, and repeat exposures. Compare lactose-free cow’s milk against regular milk, A2 milk, yogurt, hard cheese, soy milk, oat milk, and water with similar meal timing. If every dairy form causes symptoms, dairy protein or fat may be relevant. If only milk causes symptoms, serving size, speed, or liquid volume may matter.

    What milk alternatives are worth comparing?

    Milk alternatives should be compared by protein, fat, fiber, fortification, sweeteners, and tolerance rather than by marketing category. Unsweetened soy milk usually provides more protein than almond, oat, or rice beverages. Oat milk can contain more carbohydrate and gums, which may matter for people sensitive to fermentable carbohydrates or thickeners. Almond milk is often lower in protein unless fortified or blended. Lactose-free cow’s milk keeps dairy protein and nutrients but changes lactose. Calcium and vitamin D fortification matter if dairy is being removed long term. Coconut milk can be higher in saturated fat, which may matter for reflux-prone drink timing. A practical comparison uses one unsweetened option at a time for several days while keeping breakfast, coffee, and bedtime timing similar. Switching five variables at once makes the result impossible to read. The best alternative is the one that gives consistent tolerance and fits the person’s nutrition needs.

    When should lactose-free milk symptoms be checked?

    Symptoms should be checked when they are persistent, severe, escalating, or paired with red flags such as weight loss, blood in stool, repeated vomiting, trouble swallowing, dehydration, fever, anemia, or nighttime symptoms that wake you. Lactose-free milk reactions can be simple intolerance patterns, but they can also overlap with reflux, IBS, food allergy, celiac disease, inflammatory bowel disease, gallbladder issues, or medication effects. Mayo Clinic notes that lactose intolerance can occur when the small intestine produces too little lactase, and secondary lactose intolerance can follow illness, injury, or small-intestine conditions in its lactose intolerance overview. A clinician can decide whether history, elimination and re-challenge, breath testing, allergy evaluation, or reflux evaluation fits the pattern. The safest rule is simple: repeated symptoms deserve pattern tracking, and red flags deserve medical care.

    What questions do people ask about lactose-free milk symptoms?

    Does lactose-free milk still have lactose?

    It can contain very small residual amounts depending on product and processing. Most people with lactose intolerance tolerate lactose-reduced products better, but individual sensitivity and serving size still matter.

    Can milk protein cause symptoms if lactose is removed?

    Yes. Lactose-free milk still contains dairy proteins, including casein and whey. Milk protein reactions are different from lactose malabsorption and should be evaluated carefully if symptoms suggest allergy.

    Can lactose-free milk trigger reflux?

    It can contribute to reflux-like symptoms if volume, fat content, timing, or lying down after drinking are the main drivers. Removing lactose does not change those reflux mechanics.

    Is oat milk always easier to digest?

    No. Oat milk removes dairy proteins and lactose, but it may contain gums, oils, added sugars, or fermentable carbohydrates that bother some people.

    Should I avoid all dairy if lactose-free milk bothers me?

    Not automatically. Some people tolerate yogurt, kefir, hard cheese, or smaller portions better than milk because the food matrix, lactose amount, and serving size differ.

    What is the cleanest home test?

    Use one variable at a time. Try the same serving size, same timing, and same meal context for regular milk, lactose-free milk, and one unsweetened non-dairy alternative.

    For a detailed comparison of specific products and strains, see Do You Need Lactase With Lactose-Free Milk?.

    For a detailed comparison of specific products and strains, see Why a “Mild” Probiotic Can Still Cause Side Effects.

    What is the practical next step?

    If lactose-free milk still causes symptoms, stop treating lactose as the only possible variable. Write down the brand, portion, fat level, timing, meal context, and exact symptom pattern for one to two weeks. Compare lactose-free cow’s milk with one non-dairy alternative and one lower-fat or smaller-serving dairy option if tolerated. Keep coffee, cereal, protein powder, bedtime, and meal size as consistent as possible during each comparison. Note whether symptoms are lower-gut, upper-gut, skin-related, breathing-related, or whole-body, because those patterns point in different clinical symptom directions. If symptoms repeat despite careful testing, or if red flags appear, bring the log to a clinician. The goal is not to prove that lactose-free milk is “bad.” The goal is to identify whether lactose, dairy protein, fat, volume, reflux timing, additives, or another digestive pattern explains the reaction.

  • Why Bloating Gets Worse in Your 40s Even When Your Diet Hasn’t Changed

    Why Bloating Gets Worse in Your 40s Even When Your Diet Hasn’t Changed

    Bloating can get worse in your 40s even when diet looks unchanged because digestion, hormones, stool pattern, activity, medications, and food tolerance can change. The food may be the same, but gut motility, gas handling, constipation risk, and sensitivity to fermentable carbohydrates may not be the same.

    How did we evaluate bloating changes in your 40s?

    We evaluated age-related bloating by separating common physiology from red-flag symptoms. We prioritized NIDDK, Mayo Clinic, peer-reviewed microbiome reviews, and clinical nutrition references over anecdotal supplement claims or single-cause explanations. We excluded product recommendations because this is a cold-stage educational question and the user does not yet need a buying guide. We treated “diet has not changed” as a useful observation, not proof that digestion has stayed identical. We looked for repeatable patterns that a reader can track without restricting foods unnecessarily. We also separated symptom education from diagnosis because abdominal distension has many overlapping causes in clinical digestive practice today. The main limitation is that bloating can reflect constipation, lactose intolerance, FODMAP intake, perimenopause, stress physiology, medication effects, pelvic floor changes, or medical conditions, so persistent or severe symptoms need individualized medical evaluation.

    Why can the same diet cause more bloating after 40?

    The same diet can cause more bloating after 40 because the digestive context around the diet can change. The NIDDK explains that gas in the digestive tract can come from swallowed air and bacterial fermentation of carbohydrates. If stool moves more slowly, gas can feel more trapped even when meals look familiar. If activity drops, hydration changes, or fiber intake stays high without enough fluid, constipation-linked bloating can increase. If lactose tolerance changes, the same milk, yogurt, or whey-containing food can create more gas. If onions, garlic, wheat, beans, or certain sweeteners appear often, fermentable carbohydrates can exceed a new tolerance threshold. The important point is that “same diet” does not mean “same digestion.” The body processes the same inputs under different motility, hormone, stress, medication, sleep, and activity conditions. That context changes the result of familiar meals.

    How do hormones affect bloating in your 40s?

    Hormonal transition can affect bloating in the 40s because estrogen and progesterone influence fluid balance, bowel motility, and visceral sensitivity. Mayo Clinic notes that perimenopause can begin years before menopause and may include cycle changes, sleep disruption, and body changes (Mayo Clinic). Those shifts do not mean every bloating episode is hormonal, but they can change the background conditions around digestion. Progesterone can slow gastrointestinal movement for some people, and slower movement can make stool and gas feel more uncomfortable. Sleep disruption can also change meal timing, caffeine use, stress reactivity, and constipation risk. A useful pattern check compares bloating timing with menstrual cycle phase, sleep quality, bowel movements, and high-fermentation meals. Hormones can be part of the pattern without being the only cause, especially when symptoms cluster around predictable cycle windows. A cycle-aware log can make that pattern visible.

    What non-diet factors commonly increase bloating?

    Non-diet factors commonly increase bloating by changing motility, pressure, or gas perception. Reduced walking, strength training, or daily movement can slow bowel habits. New medications, including some acid reducers, iron, calcium, pain relievers, and antidepressants, can change constipation risk or upper-gut comfort. Stress can alter gut-brain signaling and make normal gas feel more intense. Eating speed can increase swallowed air. Carbonated drinks can add gas volume. Constipation can make the abdomen feel tight even when calories and food choices are unchanged. Pelvic floor coordination can also affect evacuation, which changes pressure after meals. A practical review should list the last three months of medication changes, sleep changes, exercise changes, travel, stress spikes, bowel frequency, and meal timing. That list often explains why a familiar diet suddenly feels unfamiliar after meals. The pattern may be behavioral, not dietary.

    When should bloating in your 40s be checked?

    Infographic showing motility, hormones, constipation, medications, stress, sleep, and movement as bloating factors after 40.
    Infographic showing motility, hormones, constipation, medications, stress, sleep, and movement as bloating factors after 40.

    Bloating in your 40s should be checked when it is new, persistent, severe, worsening, or paired with warning signs. The NIDDK lists symptoms such as blood in stool, vomiting, diarrhea, constipation, unexplained weight loss, and persistent abdominal pain as reasons to seek care for gas-related concerns (NIDDK). Sudden appetite loss, fever, anemia, black stools, repeated vomiting, trouble swallowing, or pain that wakes someone at night also deserves medical attention. Most bloating is not an emergency, but age should lower the threshold for a careful review when symptoms change without an obvious reason. A clinician can decide whether constipation care, food intolerance testing, medication review, pelvic floor evaluation, imaging, bloodwork, or endoscopy is appropriate. Self-tracking helps, but red flags need diagnosis, not guessing or online reassurance. Timely review protects against missed causes and delayed evaluation.

    What can you track before changing your diet?

    Track bowel pattern, meal timing, and symptom timing before changing the whole diet. Record stool frequency, stool form, bloating severity, gas, abdominal pressure, menstrual cycle phase, sleep, movement, and medication timing for two weeks. Note high-fermentation meals that contain beans, onions, garlic, wheat, apples, stone fruit, dairy, sugar alcohols, or carbonated drinks. The goal is not to create a perfect food diary; the goal is to spot repeated triggers. If bloating is worse on low-movement days, motility may matter. If bloating is worse around certain cycle phases, hormones may matter. If bloating is worse after dairy, lactose may matter. If bloating is worse when stool frequency drops, constipation may matter. A clean log prevents unnecessary restriction and gives a clinician better information than memory alone. It also makes small experiments safer and more specific.

    What questions do people ask about bloating after 40?

    Can bloating increase during perimenopause?

    Yes, bloating can increase during perimenopause for some people. Hormonal shifts can interact with fluid balance, constipation tendency, sleep, and gut sensitivity.

    Can constipation cause a pregnant-looking belly?

    Yes, constipation can create abdominal pressure, trapped gas, and visible distension. Persistent or painful distension should be checked, especially when it is new.

    Can lactose intolerance appear later in life?

    Yes, lactose tolerance can change over time. A two-week dairy pattern check can help identify whether milk, ice cream, whey, or soft cheeses repeatedly match symptoms.

    Should I cut out all high-FODMAP foods?

    Not without a plan. Broad restriction can reduce diet quality, so a clinician or dietitian-guided approach is better for persistent symptoms.

    Are probiotics the first step for bloating after 40?

    Not always. Stool pattern, food triggers, medications, activity, and red flags should be reviewed before assuming a probiotic is the right first move.

    When is bloating urgent?

    Bloating is more urgent when it comes with severe pain, vomiting, blood in stool, black stools, fever, unexplained weight loss, anemia, or progressive worsening. Those symptoms need medical care.

    What is the practical next step?

    Start with a two-week pattern log instead of changing everything at once. Track stool frequency, bloating timing, cycle phase, activity, sleep, medications, dairy, carbonated drinks, and high-fermentation foods. If the log points to constipation, lactose, eating speed, or low movement, address that pattern first. If symptoms are severe, persistent, new, or paired with red flags, book a medical evaluation. The useful answer is usually not that the diet secretly changed; it is that the digestive context around the diet changed. That framing helps narrow the next step without turning a familiar diet into an unnecessary restriction project. Bring the log to a clinician if symptoms persist. It can shorten the conversation, reduce guesswork, and show whether the problem is stool pattern, food tolerance, medication timing, cycle timing, or something that needs testing soon safely.

  • What Is the Problem With Artificial Sweeteners If You Eat Well?

    What Is the Problem With Artificial Sweeteners If You Eat Well?

    Artificial sweeteners are not automatically harmful, but they are not nutritionally neutral for everyone. The main concerns are taste conditioning, digestive tolerance, sugar-alcohol gas, uncertain long-term weight-control benefit, and possible person-specific microbiome effects. A good diet can still include them, but intake pattern and sweetener type matter.

    How we evaluated artificial sweeteners?

    We evaluated artificial sweeteners by separating regulatory safety from nutrition strategy, because “allowed in food” and “useful for long-term diet quality” answer different questions. We prioritized FDA safety pages, WHO nutrition guidance, human trials, and peer-reviewed microbiome reviews over animal-only studies, influencer claims, or single anecdotes. We treated aspartame, sucralose, saccharin, acesulfame potassium, stevia glycosides, and sugar alcohols as different ingredients rather than one identical category. The limitation is that individual tolerance varies, so this article explains plausible mechanisms and evidence strength instead of predicting one person’s response. We also separated high-intensity sweeteners from polyols because sorbitol, maltitol, xylitol, and erythritol have different digestive behavior than aspartame or sucralose. That distinction matters when someone eats well but still notices gas, cravings, diarrhea, cramping, urgency, stool changes, or bloating after sugar-free products and drinks daily.

    What are artificial sweeteners and why are they used?

    Artificial sweeteners and other non-sugar sweeteners provide sweetness with little or no digestible sugar. Aspartame, sucralose, saccharin, acesulfame potassium, neotame, and advantame are high-intensity sweeteners that the FDA permits for specific food uses after safety review (FDA). Stevia-derived sweeteners and monk fruit extracts are often marketed as natural, but they still function as concentrated sweeteners. Sugar alcohols such as sorbitol, xylitol, erythritol, and maltitol are different because they contain calories and can reach the colon partly undigested. Food companies use these ingredients to lower sugar, reduce calories, support diabetic-friendly labeling, and preserve sweet taste. The tradeoff is that sweetness can remain high even when sugar drops, so a “good diet” can still train the palate toward very sweet foods and drinks over time repeatedly.

    Why might sweeteners bother digestion even when calories are low?

    Digestive effects depend on the ingredient. Sugar alcohols are the most common digestive culprit because sorbitol, mannitol, maltitol, and xylitol can pull water into the intestine and feed colonic fermentation. That process can produce gas, bloating, cramping, and loose stool, especially when someone eats multiple “sugar-free” candies, protein bars, gums, or drinks in one day. High-intensity sweeteners such as sucralose and aspartame are used in much smaller amounts, so they usually do not create the same osmotic load. However, products rarely contain only one sweetener; a diet soda, flavored yogurt, protein powder, and gum can create a repeated exposure pattern. The practical question is not whether the sweetener has calories. The useful question is whether that exact product, dose, and timing predict symptoms in a 7-day food and symptom log after meals consistently enough.

    What does research say about microbiome effects?

    Microbiome research shows caution, not a settled verdict. A 2022 randomized controlled trial in Cell reported that saccharin and sucralose changed glycemic responses in some participants, with microbiome patterns suggesting person-specific effects (Cell). The study used short-term exposure, healthy adults, and controlled sachets, so it should not be translated into a universal claim that every diet soda harms glucose control. A 2022 review in Frontiers in Nutrition concluded that non-nutritive sweeteners can interact with gut microbes, but human evidence remains mixed by sweetener, dose, host biology, and study design (PMC). The strongest statement is narrow: some sweeteners may affect some people differently. The weakest statement is broad: all artificial sweeteners ruin the microbiome. Evidence does not support that sweeping claim.

    Are artificial sweeteners useful for weight control?

    Food log beside sweetened foods and drinks for tracking artificial sweetener tolerance.
    Food log beside sweetened foods and drinks for tracking artificial sweetener tolerance.

    Artificial sweeteners can reduce sugar calories when they replace sugar-sweetened drinks or desserts without compensation elsewhere. The problem is that replacement does not guarantee long-term behavior change. In 2023, the World Health Organization advised against using non-sugar sweeteners as a weight-control strategy for the general population, based on evidence that long-term benefit was uncertain and observational studies linked higher intake with some cardiometabolic outcomes (WHO guideline). WHO also stated that the recommendation was not a toxicology safety update, which means it did not replace acceptable daily intake limits set by food-safety authorities. The practical interpretation is balanced: a diet soda may be a useful step away from regular soda, but a high-sweetness diet should not be the entire plan. Water, unsweetened tea, fruit, and less-sweet staples still matter.

    How can a good diet still include them wisely?

    A good diet can include artificial sweeteners when they solve a specific problem and do not crowd out minimally sweet foods. The best use case is targeted substitution: replacing a sugar-heavy drink, reducing added sugar in coffee, or choosing a lower-sugar yogurt while keeping protein, fiber, and whole-food intake stable. The weakest use case is constant sweetness exposure from morning coffee syrup, diet soda, flavored protein powder, sugar-free candy, chewing gum, and dessert substitutes. That pattern can preserve cravings even when calories drop. A simple audit helps: list every sweetened item for three days, mark the sweetener type, and note timing. If symptoms or cravings cluster around sugar alcohols, large servings, or constant sweet taste, reduce frequency before declaring all sweeteners bad. The dose pattern usually explains more than the label category itself does.

    FAQ?

    Are artificial sweeteners toxic?

    FDA-approved high-intensity sweeteners have acceptable daily intake limits and safety reviews for permitted food uses. Toxicity claims should be separated from questions about appetite, gut tolerance, and long-term nutrition strategy.

    Is stevia different from artificial sweeteners?

    Stevia-derived sweeteners come from plant compounds, but they still deliver intense sweetness without meaningful nutrition. The body may treat “natural” and synthetic sweet taste differently by compound, dose, and product context.

    Why do sugar-free foods cause gas?

    Sugar alcohols such as sorbitol, maltitol, and xylitol can reach the colon and be fermented by bacteria. That fermentation can produce gas and bloating, especially at higher servings.

    Should I stop diet soda if I eat well?

    Not automatically. If diet soda helps you avoid sugar-sweetened soda and causes no symptoms, it may be a reasonable bridge. If it maintains constant sweet cravings or replaces water all day, reduce frequency.

    Do artificial sweeteners harm the microbiome?

    Some human studies show sweetener-specific and person-specific microbiome changes, but the evidence is not uniform. The most accurate answer is that effects may vary by sweetener, dose, baseline microbiome, and diet pattern.

    What is the simplest test?

    Remove sugar alcohol-heavy foods and drinks for seven days while keeping the rest of the diet stable. If gas, bloating, or cravings improve, reintroduce one product at a time to identify the trigger.

    What is the bottom line?

    Artificial sweeteners are a tool, not a free pass or a poison category. A person eating a good diet should judge them by purpose, dose, tolerance, and frequency. Occasional use to reduce added sugar is different from constant sweet-taste exposure all day. If digestion feels worse, start with sugar alcohols and product stacking before blaming every non-sugar sweetener. If weight control is the goal, use sweeteners as a transition while building less-sweet default drinks and foods. If blood sugar, pregnancy, migraine, phenylketonuria, or gastrointestinal symptoms affect the decision, a clinician or registered dietitian can personalize the advice. The most defensible strategy is simple: reduce added sugar, keep total sweetness moderate, prioritize whole foods, and track your own response across real meals, not isolated headlines or fear-based posts online about one ingredient alone today either.


  • Why Do I Get Bloating and Gas While I’m Still Eating?

    Why Do I Get Bloating and Gas While I’m Still Eating?

    Bloating and gas while you are still eating can happen when swallowed air, fast eating, carbonated drinks, high-fermentation foods, delayed stomach emptying, constipation, or gut-brain sensitivity create pressure before the meal is finished. Pattern tracking matters because the trigger is not the same for everyone.

    How did we evaluate bloating and gas while eating?

    We evaluated this question by separating common physiology from red-flag symptoms and supplement marketing. NIDDK, Mayo Clinic, and Cleveland Clinic references received more weight than anecdotal forum explanations because they distinguish swallowed air, fermentation, constipation, motility, and medical evaluation. We excluded claims that one food, one test, or one supplement explains every bloating pattern. The main limitation is that bloating is a symptom description, not a diagnosis, so the safest answer focuses on timing, meal context, stool pattern, and clinician review when symptoms are severe, new, or persistent.

    Why can bloating start before a meal is finished?

    Bloating can start during a meal because the digestive tract responds before food reaches the colon. Swallowed air enters the stomach when a person eats quickly, talks while chewing, drinks through a straw, chews gum, or uses carbonated drinks. The NIDDK explains that gas comes from swallowed air and bacterial breakdown of carbohydrates. Stomach stretching can also create pressure signals during a large meal, especially when fat, alcohol, or stress slows normal movement. Some people feel pressure earlier because visceral hypersensitivity makes ordinary gas or stretching feel more intense. Fermentable carbohydrates usually create more gas later, but meal timing can overlap when breakfast, lunch, snacks, and constipation keep the gut already loaded. The key clue is timing: immediate pressure points toward air, stomach distension, or sensitivity, while delayed gas points more toward fermentation.

    What meal patterns make immediate bloating more likely?

    Immediate bloating becomes more likely when meal speed, volume, beverage choice, and food texture increase stomach pressure. Large meals stretch the stomach more than smaller meals, and carbonated beverages add gas directly before digestion begins. High-fat meals can slow gastric emptying, so pressure can linger longer after the first bites. Wheat, onions, beans, apples, milk, sugar alcohols, and some protein bars can add fermentable carbohydrate load, although fermentation usually shows up later. The NIDDK IBS diet guidance notes that certain carbohydrates can trigger gas and bloating in sensitive people. Constipation also matters because stool retention can reduce room in the colon and make normal meal-related reflexes feel stronger. A useful pattern log records meal size, eating speed, carbonation, dairy, wheat, onions, beans, stool frequency, and symptom timing.

    How can you tell swallowed air from food fermentation?

    Swallowed air usually creates upper-abdominal fullness, burping, pressure, or discomfort during the meal or shortly afterward. Food fermentation usually creates lower-abdominal gas, rumbling, flatus, or distension several hours later, although overlapping meals can blur that timeline. Mayo Clinic describes gas and gas pains as common and often related to swallowed air or food breakdown, but persistent or severe symptoms deserve evaluation (Mayo Clinic). The practical test is not perfect, but it is useful: slow the meal, skip carbonation, avoid straws, and eat smaller portions for several days. If immediate pressure drops, swallowed air or stomach distension was probably part of the pattern. If symptoms remain tied to specific carbohydrates hours later, fermentation or intolerance becomes more plausible. If stool frequency is low, constipation can amplify both patterns.

    What should you track before changing your diet?

    Infographic showing swallowed air, carbonation, meal size, constipation, and fermentation as bloating timing factors.
    Infographic showing swallowed air, carbonation, meal size, constipation, and fermentation as bloating timing factors.

    Track timing, location, stool pattern, meal details, and repeatability before removing broad food groups. A simple two-week log should record the first symptom minute, upper versus lower pressure, burping, flatus, stool frequency, stool form, carbonation, meal speed, dairy, wheat, onions, beans, garlic, fruit, protein powders, and sugar alcohols. Cleveland Clinic notes that bloating can reflect gas, digestive contents, or visceral sensitivity, and evaluation depends on the pattern (Cleveland Clinic). The goal is to find a reproducible signal, not to create a fear list. Change one variable at a time: meal pace, carbonation, portion size, lactose, or high-FODMAP foods. A broad elimination diet can hide the actual trigger and make eating more stressful. A log also helps a clinician decide whether testing for lactose intolerance, celiac disease, constipation, reflux, or other causes is reasonable.

    When is bloating while eating worth medical attention?

    Bloating while eating is worth medical attention when it is new, worsening, severe, persistent, or paired with warning signs. Red flags include vomiting, blood in stool, black stool, fever, unexplained weight loss, progressive trouble swallowing, persistent diarrhea, severe pain, anemia, or symptoms that wake someone at night. People with pregnancy, immune compromise, recent abdominal surgery, inflammatory bowel disease history, or major medication changes should also use a lower threshold for care. Most meal-related gas is not an emergency, but repeated early fullness can sometimes point to motility issues, constipation, reflux patterns, or other conditions that need evaluation. A clinician can review diet logs, stool patterns, medications, and basic tests without guessing from one symptom. The safest rule is simple: mild and pattern-based symptoms can be tracked; intense or escalating symptoms should be assessed.

    What practical steps can reduce bloating during meals?

    Start with low-risk changes that reduce air, pressure, and overload. Eat more slowly, chew fully, avoid straws, pause carbonated drinks, and reduce very large meals for one week. Keep posture upright during and after meals, and avoid stacking heavy snacks close together if symptoms appear before dinner. If constipation is present, address stool regularity with hydration, fiber tolerance, movement, and clinician guidance rather than only removing foods. If lactose seems likely, compare lactose-containing and lactose-free meals without changing five other variables. If high-FODMAP foods seem likely, use a structured approach rather than permanent restriction. These steps do not diagnose the cause, but they make the pattern easier to read. If the pattern points toward supplement comparison later, a separate buying guide can compare digestive support options without replacing medical evaluation.

    What questions do people ask about bloating while eating?

    Can gas happen before food reaches the colon?

    Yes. Swallowed air can create gas pressure in the stomach during the meal. Fermentation usually happens later, but overlapping meals and constipation can make timing confusing.

    Does immediate bloating mean a food intolerance?

    Not automatically. Immediate bloating can reflect air swallowing, carbonation, meal size, stomach stretching, stress physiology, or sensitivity. A repeatable pattern is stronger evidence than one uncomfortable meal.

    Can eating too fast cause bloating?

    Yes. Fast eating can increase swallowed air and make large portions easier to overeat. Slower meals are a low-risk first test.

    Should I cut out gluten first?

    Not without a reasoned pattern or clinician guidance. Gluten, wheat fructans, meal size, carbonation, lactose, and constipation can create similar symptoms, so broad restriction can confuse the signal.

    Can constipation make meals feel bloating sooner?

    Yes. Constipation can increase baseline pressure and make normal meal reflexes feel stronger. Stool frequency and stool form belong in the symptom log.

    What if bloating happens with severe pain?

    Severe pain, vomiting, blood, fever, weight loss, or worsening symptoms should be evaluated. A self-tracking plan is not enough for red-flag patterns.

    For a detailed comparison of specific products and strains, see Constipation, Bloating, and Gas: What Is the Simplest Plan?.

    What is the bottom line?

    Bloating and gas while eating usually needs pattern analysis, not panic. Start by reducing swallowed air, carbonation, large meals, and rushed eating while tracking stool pattern and symptom timing. If the pattern persists, worsens, or includes red flags, bring a two-week log to a clinician instead of guessing from one meal.

  • Why Was I Prescribed an Antidepressant for GERD?

    Why Was I Prescribed an Antidepressant for GERD?

    Antidepressants are sometimes prescribed for GERD-like symptoms because low-dose neuromodulators can reduce esophageal pain sensitivity, reflux hypersensitivity, functional heartburn, or gut-brain signaling when acid suppression alone does not explain symptoms. The prescription does not necessarily mean the clinician thinks the reflux is “all in your head.”

    How did we evaluate antidepressants for GERD-like symptoms?

    We evaluated this topic through gastroenterology guidelines, esophageal testing references, and clinical trials on functional heartburn and reflux hypersensitivity. We prioritized American College of Gastroenterology guidance, PubMed-indexed trials, and physiology-based explanations over forum anecdotes or medication marketing. We excluded personal dosing advice because antidepressants, proton pump inhibitors, H2 blockers, and anxiety medications require individualized prescribing. The key distinction is clinical: classic GERD involves abnormal reflux burden, while reflux hypersensitivity and functional heartburn involve symptom perception, nerve signaling, or symptom association with normal acid exposure.

    Why would a GERD clinician prescribe an antidepressant?

    A clinician may prescribe a low-dose antidepressant for GERD-like symptoms when reflux testing, endoscopy, PPI response, and symptom pattern suggest esophageal hypersensitivity or functional heartburn. The 2022 American College of Gastroenterology GERD guideline says ambulatory reflux monitoring can help establish or refute GERD and correlate symptoms with reflux episodes (ACG GERD guideline). When acid exposure is normal but symptoms remain intense, the treatment target may shift from acid quantity to nerve sensitivity. Tricyclic antidepressants, selective serotonin reuptake inhibitors, serotonin-norepinephrine reuptake inhibitors, or related neuromodulators can be used at doses different from depression treatment. The goal is symptom modulation, not personality change. That is why a prescription can appear surprising: the drug class name describes one use, while the digestive use targets visceral pain pathways and brain-gut signaling.

    What is reflux hypersensitivity?

    Reflux hypersensitivity means normal or near-normal reflux events create symptoms because the esophagus reacts strongly to stimuli that would not bother another person. ACG physiologic testing guidance says endoscopy, reflux monitoring, and manometry can help separate GERD, structural disorders, motor disorders, behavioral syndromes, and functional esophageal disorders (ACG esophageal testing guideline). Reflux hypersensitivity is not imaginary. The esophagus contains sensory nerves, smooth muscle, immune cells, and epithelial barriers that can change symptom perception. A person can feel burning, chest discomfort, throat sensation, or regurgitation-like distress even when acid exposure does not meet classic GERD thresholds. The practical difference matters because more acid suppression may not solve a sensitivity-driven pattern. A clinician may choose a neuromodulator when the symptom generator looks more like sensory amplification than ongoing corrosive acid exposure.

    How is functional heartburn different from GERD?

    Functional heartburn describes heartburn symptoms without abnormal acid exposure, without clear symptom-reflux association, and without visible esophageal injury on standard evaluation. Classic GERD usually shows erosive esophagitis, abnormal acid exposure, or symptom improvement that tracks acid suppression. Functional heartburn belongs to disorders of gut-brain interaction, where pain processing, hypervigilance, stress physiology, and esophageal sensitivity can maintain symptoms. A randomized placebo-controlled trial of imipramine in esophageal hypersensitivity and functional heartburn tested whether a tricyclic antidepressant could reduce symptoms through pain modulation rather than acid reduction (Limsrivilai et al., American Journal of Gastroenterology). The evidence is mixed and not a universal answer. The important point is classification. If symptoms persist despite appropriate GERD therapy, a clinician may investigate whether acid, motility, anatomy, or nerve sensitivity is driving the pattern.

    What should you ask before taking it?

    In-article illustration for 2026 05 28 antidepressant for gerd cold
    In-article illustration for 2026 05 28 antidepressant for gerd cold

    Ask the prescriber what diagnosis the medication is targeting, what test results support that diagnosis, what dose is being used, and what outcome should change first. Ask whether the goal is reflux hypersensitivity, functional heartburn, functional dyspepsia, anxiety-associated symptom amplification, sleep support, or another reason. Ask how long the trial should last, how side effects will be handled, and whether the medication interacts with PPIs, H2 blockers, antacids, SSRIs, sleep aids, alcohol, or other prescriptions. Ask what symptoms require urgent care, such as trouble swallowing, vomiting blood, black stool, severe chest pain, unexplained weight loss, anemia, or persistent vomiting. These questions do not challenge the clinician; they clarify the treatment target. A good explanation should connect the prescription to a specific symptom mechanism, not leave the patient guessing.

    What are the common options doctors compare?

    Doctors may compare acid suppression, lifestyle measures, reflux testing, motility evaluation, behavioral therapy, and neuromodulators depending on the pattern. Proton pump inhibitors reduce stomach acid and fit confirmed acid-mediated GERD. H2 blockers reduce acid through a different mechanism and may fit milder or nighttime patterns. Neuromodulators target pain signaling and fit selected cases of reflux hypersensitivity, functional heartburn, or overlapping gut-brain disorders. Behavioral approaches can reduce rumination, supragastric belching, hypervigilance, and stress-linked symptom loops when those mechanisms are present. Procedures are usually reserved for carefully documented reflux or anatomy problems because sensitivity-driven symptoms may not improve after anti-reflux surgery. The ACG GERD guideline emphasizes objective evaluation before invasive therapy in unclear cases (ACG full guideline). The best option depends on evidence, not symptom intensity alone.

    What questions do people ask about antidepressants for GERD?

    Does this mean my GERD is caused by anxiety?

    No. A neuromodulator prescription can mean the clinician suspects nerve sensitivity, reflux hypersensitivity, or functional heartburn. Anxiety may amplify symptoms in some people, but it is not the only reason these medicines are used.

    Are low-dose antidepressants the same as depression treatment?

    Not always. Gastroenterologists often use lower doses for pain modulation than psychiatrists use for major depression. The prescriber should explain the dose, expected timeline, and side effect plan.

    Should I stop my PPI if I start a neuromodulator?

    Do not stop prescribed medicine without the clinician’s plan. Some people use acid suppression and neuromodulation together while diagnostic clarity improves.

    What tests clarify the diagnosis?

    Endoscopy, ambulatory pH monitoring, impedance-pH monitoring, and esophageal manometry can clarify acid exposure, symptom association, motility, and functional patterns. The exact test depends on symptoms and prior results.

    When should symptoms be urgent?

    Chest pain, trouble swallowing, vomiting blood, black stool, fainting, severe abdominal pain, anemia, or unintended weight loss deserves prompt medical attention. Those signs should not be managed as routine reflux.

    Can supplements replace this treatment?

    No supplement should replace a prescribed neuromodulator, PPI, or diagnostic plan. Supplements may support general routines, but they do not diagnose reflux hypersensitivity or functional heartburn.

    What is the practical next step?

    The practical next step is to ask for the working diagnosis in plain language: GERD, reflux hypersensitivity, functional heartburn, functional dyspepsia, anxiety-linked symptom amplification, or another condition. Then ask what evidence supports that label and what improvement should appear during the medication trial. A prescription makes more sense when the mechanism is named.

  • How Does Digestion Actually Work After You Eat?

    How Does Digestion Actually Work After You Eat?

    Digestion works as a coordinated sequence: the mouth breaks food apart, the stomach mixes it with acid, the small intestine absorbs most nutrients, and the colon handles water, fiber fermentation, and stool formation. Timing varies by meal size, fat, protein, fiber, hormones, nerves, gut bacteria, and individual motility patterns.

    How did we evaluate how digestion works?

    We evaluated digestion through anatomy, physiology, motility, absorption, and microbiome roles rather than through one fixed “digestion time” rule. Government medical references received priority because NIDDK explains digestive organs and common gas patterns in patient-facing language. Peer-reviewed physiology concepts shaped the sequence, but we avoided claims that require testing, diagnosis, or individualized treatment. This article explains normal digestive coordination; persistent pain, vomiting, bleeding, unintended weight loss, or major bowel changes deserve clinician evaluation.

    What happens first when food enters the digestive system?

    Digestion starts before food reaches the stomach. Chewing increases surface area, saliva moistens food, and salivary amylase begins starch breakdown in the mouth. The esophagus moves swallowed food by peristalsis, which means coordinated muscle contractions push the bolus toward the stomach. The lower esophageal sphincter opens briefly, then closes to reduce backward movement of stomach contents. According to NIDDK, digestion uses organs, nerves, hormones, bacteria, and blood flow to turn food and liquid into usable nutrients (NIDDK). This process does not run like a simple timer. A high-fat meal, large meal, alcohol, stress, and some medications can slow gastric emptying, while liquids usually move faster. The practical takeaway is simple: the digestive tract processes mixed meals dynamically, not in separate isolated batches.

    How does the stomach decide when food moves forward?

    The stomach stores food, churns it with acid and pepsin, and releases partially digested chyme through the pyloric sphincter in controlled pulses. Gastric emptying depends on meal volume, particle size, fat content, calorie load, and feedback from the small intestine. The duodenum slows stomach release when chyme is too acidic, too fatty, or too concentrated because pancreatic enzymes and bile need time to work. Hormones such as cholecystokinin, secretin, and gastrin help coordinate that traffic. A snack eaten after lunch does not “restart” digestion from zero; it adds new material to an active system. The stomach can hold, mix, and release at the same time. That is why fullness, belching, or bloating can change over several hours after one meal. The stomach functions like a regulated mixing chamber, not a waiting room with one departure schedule.

    Where are nutrients actually absorbed?

    Infographic showing chewing, stomach mixing, enzyme breakdown, nutrient absorption, and colon fermentation.
    Infographic showing chewing, stomach mixing, enzyme breakdown, nutrient absorption, and colon fermentation.

    The small intestine handles most nutrient absorption. The pancreas releases enzymes that help break down carbohydrates, proteins, and fats, while bile from the liver and gallbladder helps emulsify fat. The intestinal lining uses villi and microvilli to increase surface area, so amino acids, sugars, fatty acids, vitamins, minerals, and electrolytes can move into blood or lymph. NIDDK describes digestion as the process that makes nutrients available for energy, growth, and cell repair (NIDDK). Fiber behaves differently because human enzymes do not digest many fiber types fully. Soluble fiber can hold water and later become fermentation substrate for colon bacteria. Insoluble fiber can increase stool bulk and support transit regularity. Nutrient absorption is therefore mostly a small-intestine job, while fiber effects are shared between the small intestine, colon, and microbiome.

    What role do gut bacteria and gas play?

    Gut bacteria mainly act in the colon, where they ferment undigested carbohydrates, resistant starches, and some fibers. Fermentation can produce short-chain fatty acids, carbon dioxide, hydrogen, methane, and other compounds. Gas is not automatically a sign that digestion is broken. NIDDK reports that gas normally leaves through belching or flatulence and that bloating is a common fullness or swelling sensation (NIDDK gas guide). The important distinction is pattern. Occasional gas after beans, onions, wheat, dairy, sugar alcohols, or large fiber increases is expected for many people. Severe pain, vomiting, blood, fever, unintended weight loss, or persistent diarrhea changes the risk profile. Bacteria help finish parts of digestion that human enzymes cannot complete, but bacterial fermentation can also create symptoms when substrate load, sensitivity, or motility changes.

    For a detailed comparison of specific products and strains, see Do Digestive Enzymes Actually Work for Bloating? What Consistent Results Depend On.

    For a detailed comparison of specific products and strains, see Digestive Enzymes Saved My Life? What Actually Determines Whether They Work.

    What questions do people ask about digestion?

    How long does digestion take? A mixed meal can leave the stomach over several hours, while full gastrointestinal transit can take much longer. Timing varies by meal composition, hydration, motility, and individual physiology.

    Does drinking water dilute stomach acid? Normal water intake does not “turn off” digestion. The stomach regulates acidity continuously through acid secretion, buffering, and emptying.

    Does food digest in the order you ate it? Not exactly. The stomach mixes food, then releases chyme in regulated pulses based on texture, calories, fat, and small-intestine feedback.

    Why do high-fiber foods cause gas? Some fibers reach the colon, where bacteria ferment them. Fermentation can produce gas and short-chain fatty acids.

    Is bloating always poor digestion? No. Bloating can reflect gas, fluid shifts, stool burden, sensitivity, meal size, or motility changes.

    When should digestive symptoms be checked? Symptoms with blood, fever, vomiting, unintended weight loss, severe pain, or persistent bowel changes deserve medical evaluation.

    Digestion is a coordinated system, not a single stomach timer. The useful model is mouth preparation, stomach mixing, small-intestine absorption, colon water handling, and microbiome fermentation.